
Pharmacy App Development in 2026: The Executive Playbook

Updated: September 2026
"I don't want to spend $300,000 on a pharmacy app that'll be obsolete in two years." A healthcare CIO told us that, and he had reason to worry: plenty of traditional online pharmacy app development solutions end in bloated budgets and technical debt that lingers for years.
His number matches the top of the full-featured tier. Pharmacy app development from scratch starts at $40,000 for an MVP.
The counter went digital a while ago: Surescripts reports that 98.3% of the pharmacies on its network were enabled for controlled-substance e-prescribing (Surescripts Annual Impact Report 2025).
The rules kept moving too. FDA closed the compounded GLP-1 supply line in spring 2025, and DSCSA's electronic tracing requirements are in force with a carve-out for qualifying small dispensers until November 27, 2027.
AI builders, meanwhile, now compete with agencies for the build itself.
What does pharmacy app development involve in 2026?
Online pharmacy app development is building the software a licensed pharmacy uses to take prescriptions, check insurance, let a pharmacist review and dispense, and take payment. In the US it answers to HIPAA for patient data, DSCSA for tracing prescription drugs and DEA's rules once controlled substances are involved. A from-scratch MVP costs $40,000 to $80,000 over 3 to 5 months and a full-featured product $150,000 to $300,000 or more over 9 to 12+ months, while on Specode a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build.
Key takeaways
- Integrations set your tier: E-prescribing, the pharmacy management system, insurance eligibility and multi-location inventory push a build into the full-featured tier.
- The pharmacy carries most of the compliance load: It's a HIPAA covered entity once it bills insurance electronically, the dispenser under DSCSA, and generally needs a nonresident license in each state it mails into. No app can be HIPAA certified.
- GLP-1s mean branded supply and a cold-chain clock: FDA's enforcement discretion for compounded tirzepatide and semaglutide ended in spring 2025, and a Wegovy pen's 28-day room-temperature allowance calls for a per-package record.
- Roll out small and staff the change: To develop an online pharmacy app your staff actually use, start in 2 or 3 pharmacies.
- Keep the code whichever way you build: On Specode you own 100% of the code, which is what let AlgoRX bring development in-house as it grew.
Online pharmacy app development: a growing market on thin margins
Pharmacy app development is a bet on where patients will fill prescriptions next. Size your pharma app development budget on the operating realities below.
The epharmacy market is forecast to grow 19.4% a year
The global epharmacy market was worth $150.7 billion in 2025 and is projected to reach $733.38 billion by 2034, growing at a 19.4% CAGR (Fortune Business Insights, 2026).
For e-pharmacy app development, that's the demand side. The pharmacy market itself still runs on thin margins and payer rules, and your product has to work inside both.
The manufacturers' side of the shift is in our piece on digital health in pharma.
Four forces push pharmacies toward digital
- Patient expectations: People who track every parcel to the door expect the same from a prescription: order status, multiple payment options and a coverage check before they pay.
- Overhead: A customized pharma app can take over the inventory and refill work your staff still does by hand.
- Regulations: DSCSA, the Drug Supply Chain Security Act, put serialized product tracing on every link of the prescription supply chain and, outside the small dispenser carve-out, requires tracing data to move electronically and interoperably (FDA, 2026).
- Access: Online pharmacies reach rural and underserved patients far from a counter who need their medications.
Adding pharmacist or prescriber consults makes telepharmacy a feature set of its own, and our guide to Telemedicine App Development covers that build.
Both pharmacy business models wait on prior authorization
Prior authorization is the delay neither model escapes: of branded prescriptions rejected for it at the counter, 35% clear in a single day.
The rest wait a median of 6 days, with the middle half landing between 3 and 12, and only 54% are ever approved (JAMA Health Forum, 2026, on 2024 IQVIA pharmacy claims).
Your app controls one thing in that queue: whether the patient can see where they are in it.
Delaying digital adoption keeps costing you
Every month you put off a custom pharma app, physical pharmacies keep paying for real estate and staffing, and legacy systems get harder and pricier to connect.
Don't trust a savings percentage for the online model; we haven't found a published figure that holds up.
Build small, then measure against your KPIs
- Build your own pharmacy app: Specode builds it by chat on a HIPAA-ready foundation, and you own the code. Its HIPAA Compliance Agent finds issues, but our docs are explicit that it doesn't guarantee full HIPAA compliance alone.
- Start with an MVP: Launch the core ordering and health insurance flows, then scale as the ROI shows up.
Tie each release to numbers your leadership already tracks: patient satisfaction, Net Promoter Score, retention and audit findings.
GLP-1s at the pharmacy counter run on branded supply
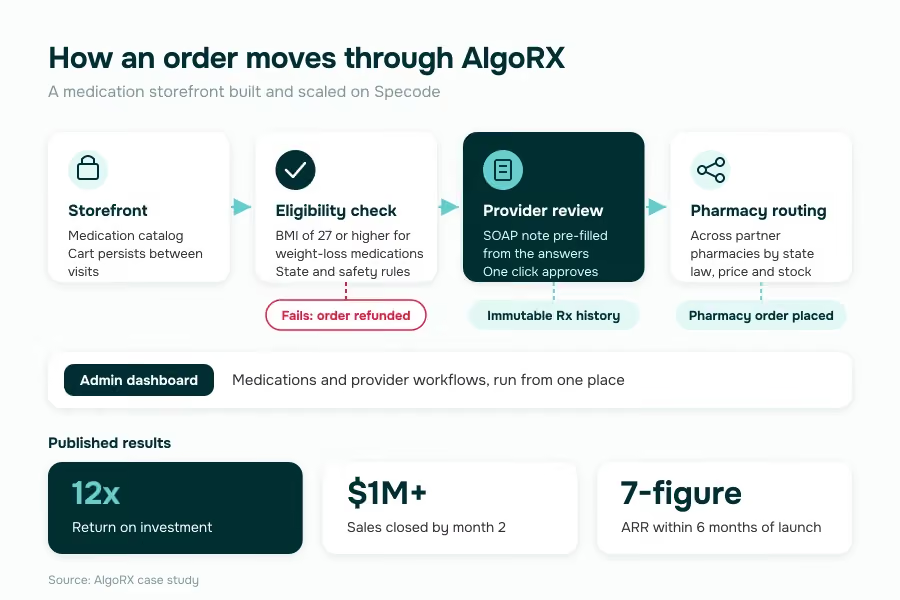
On AlgoRX, weight-loss medications sit behind an eligibility questionnaire that gates on a BMI of 27 or higher, and branching logic then checks state-specific rules, contraindications and pre-existing conditions.
At the counter, GLP-1 medications are a supply and storage question; the clinic side has its own guide: building a GLP-1 virtual clinic.
Compounded supply is a closed channel
FDA declared the tirzepatide shortage resolved in December 2024 and the semaglutide shortage in February 2025, and two injunction bids by compounders failed. Enforcement discretion ended on these dates (FDA, 2026):
- 503A pharmacies: March 5, 2025 for tirzepatide, April 24, 2025 for semaglutide
- 503B outsourcing facilities: March 19, 2025 for tirzepatide, May 22, 2025 for semaglutide
On April 30, 2026 FDA proposed excluding semaglutide, tirzepatide and liraglutide from the 503B bulks list, finding no clinical need to compound them from bulk.
If it's finalized, outsourcing facilities could in most cases compound them from bulk only while the drug is on FDA's shortage list. Comments closed on July 30, 2026, after one extension, and no final determination had issued as of September 2026.
One narrow path survives at the counter
A 503A pharmacy can still compound for an individual patient against a prescription. The limit is on copies: 503A rules out compounding essentially a copy of a commercially available drug regularly or in inordinate amounts.
FDA says it doesn't intend to act on that condition against a pharmacy that fills 4 or fewer prescriptions of such a copy in a calendar month (FDA, 2026). Every other 503A condition still applies.
An app that lets a pharmacy compound GLP-1 copies at volume routes it outside 503A.
Cold chain runs on a clock
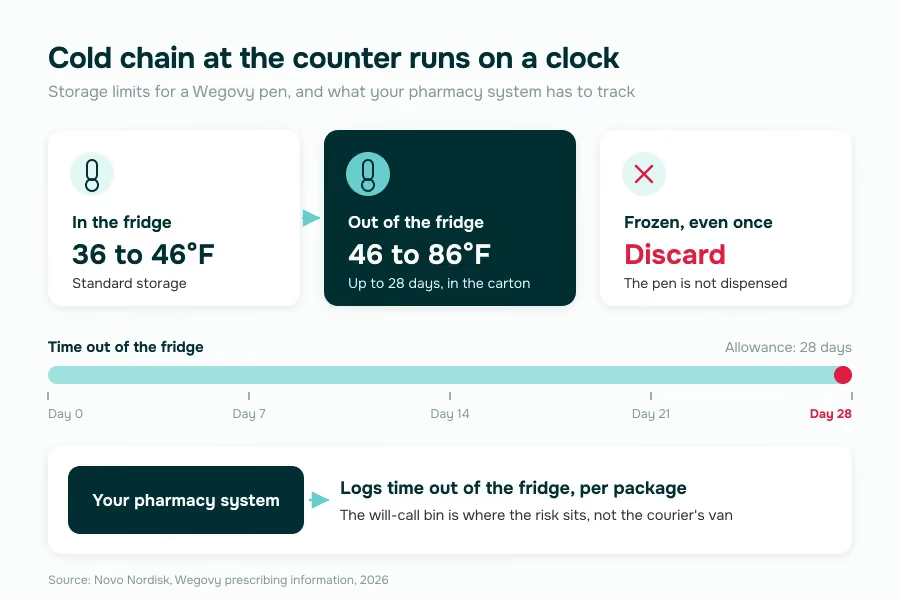
Cold-chain delivery to the door is the courier's job. At the counter, the risk sits in the will-call bin.
A Wegovy pen is stored at 36 to 46°F, may spend up to 28 days at 46 to 86°F in its original carton, and is discarded if it ever freezes (Novo Nordisk, Wegovy prescribing information, 2026). So your pharmacy system needs a per-package record of time out of the fridge.
How to build a pharmacy app: the parts retail apps skip
A pharmacy app reads like any retail app until a prescription, an insurance card or a pharmacist enters the flow. That's where pharmacy app development slows down.
So the short answer to how to build a pharmacy app: get the general healthcare app development basics right, then put your pharma application development effort into the parts only a pharmacy has.
Patient features built around the refill
The refill is the order your customer base repeats, so every patient feature should make the next one easier.
Registration and profiles
Sign-up with multi-factor authentication is the floor for data security. The profile holds medical history and health insurance details, so checkout already has the member ID.
Let patients manage profiles, medicine reminders and refill prescription settings in one place. Put lab tests and diagnostic bookings next to the refills and the app starts to work like a medical store in their pocket.
Repeat prescriptions are where customer loyalty gets earned, and our guide to Medication Reminder App Development covers the reminders behind them.
Prescription management
Patients photograph paper prescriptions, and auto-refill and reminder notifications keep medication adherence on track.
Order tracking and notifications
Order management tied to real-time inventory keeps a patient from paying for something that's out of stock, and order tracking runs on push notifications and SMS.
Twilio sends SMS and Mailgun sends email, each on a HIPAA-grade account with a signed BAA before real patient messages go out.
If you also run the pharmacy delivery leg, add a live delivery status and contactless delivery options. Courier logistics is a separate build.
Payments
Pick the processor before you design checkout. Cards and HSA or FSA cards need a processor that takes prescription businesses, and the choice shapes refunds and partner pharmacy payouts.
Teleconsultation with pharmacists
Pharmacist video or chat runs on CometChat. Budget for its HIPAA-compliant tier, since the standard account can't carry patient conversations.
E-prescribing and insurance eligibility
- E-prescribing: New prescriptions reach the pharmacy as NCPDP SCRIPT messages over Surescripts.
- Insurance eligibility: Check coverage before the patient pays, so a rejected claim surfaces at checkout instead of at pickup.
Advanced features
AI drug interaction checks and personalized recommendations build on drug information your pharmacists keep current, so ship them after the refill loop works.
Provider features your pharmacists live in
Your pharmacists live in the back office. Give them:
- Pharmacist panel: One queue for prescriptions awaiting review, dispensing records, inventory and patient assistance notes.
- Content management: A content management system that lets staff update drug information and health tips across every location.
- Pharmacy network integration: Shared stock and patient records across locations, so buying medicines at a store that's out of stock doesn't dead-end.
Every prescription waits in the pharmacist panel, so test it with working pharmacists before the patient app gets its polish.
Integrations decide which network you're on
Surescripts reports 2.64 billion e-prescriptions filled in 2025 (Surescripts Annual Impact Report 2025). An app that can't talk to that network is invisible to the prescribers who feed it.
Past e-prescribing, plan connections to EHR and EMR systems, lab systems, insurance verification services and the pharmacy networks you fill through.
Ship the MVP before the advanced features
Start with prescription management, checkout and order tracking; everything else waits.
On Specode, you add those connections with your vendors' credentials, EHR and EMR systems such as Epic and Cerner included (Specode docs, 2026).
Creating a pharmacy app runs on two clocks
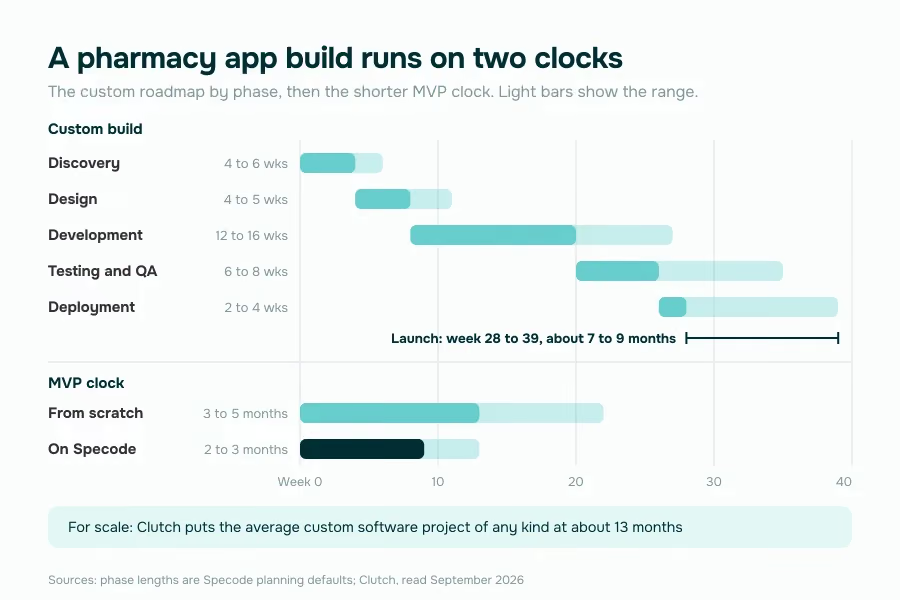
Pharmacy app development keeps two schedules. The custom one follows the five-phase roadmap below, and its phase lengths, our own planning defaults, add up to roughly 7 to 9 months.
That's deliberately faster than the market: Clutch puts the average custom software project of any kind at about 13 months (Clutch, read September 2026). Treat the gap as something your team has to earn.
The MVP clock is shorter, 3 to 5 months from scratch. On Specode a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build.
Five phases, 7 to 9 months
Discovery and planning (4 to 6 weeks)
Define the scope and the must-have features. Test integration feasibility with the EHR and the payment processor before you commit to dates, since those two gate the second milestone. The phase ends with:
- a requirements document
- initial wireframes
- a tech stack selection
Design and prototyping (4 to 5 weeks)
Design responsive, phone-first screens, then prototype the flows that carry the business: prescription upload and checkout. Test them with real patients and against accessibility standards before a developer builds them.
Development (12 to 16 weeks)
- Back end: Secure databases and APIs for orders and inventory in real time.
- Front end: Responsive interfaces for mobile and web apps.
- Integrations: E-prescribing, insurance eligibility, the payment processor and notification services.
Specode builds responsive web apps; native iOS or Android apps are a separate build that can reuse the same backend (Specode docs, 2026).
Testing and quality assurance (6 to 8 weeks)
Test four ways before launch:
- functional
- security, against your HIPAA safeguards
- performance under peak load, such as a promotional campaign
- accessibility on the phones your patients carry
Deployment and launch (2 to 4 weeks)
Deploy to production and connect the app to the pharmacy's internal systems. Native iOS or Android apps go through app store review here.
Monitor performance and patient feedback, and soft-launch before you open wide.
A custom build needs five or six roles
An example development team for the roadmap:
- Product manager: Owns scope and the business goals.
- Designer: Screens for patients and pharmacists.
- Backend developers: Databases, APIs and integrations.
- Mobile app developers: Build the pharmaceutical mobile apps for iOS and Android, when native is in scope.
- QA engineers: A test plan for every phase.
- DevOps engineer: Deployment and monitoring.
A pharmacy Android app alongside the iOS one is its own line in the team and test plans.
Four milestones set the launch date
Miss one and everything behind it moves.
- Final user requirements and compliance checks.
- Working API integrations with the EHR and the payment processor.
- Load and data security testing.
- Passing launch review: your own security testing, and app store approval if you ship native apps.
Risk mitigation starts in sprint one
Two habits catch schedule slips and budget overruns early:
- Build in iterations: Collect feedback every sprint, and hold AI drug interaction checks for a later phase.
- Check compliance every phase: Run security checks as you build, while a problem is still cheap to fix.
Online pharmacy application costs and ROI you can defend
Two decisions set pharmacy app development cost: how much of the pharmacy side goes into version one, and who writes the code.
Three cost tiers for a pharmacy product
Built from scratch, mobile app development for pharmacy lands in one of three tiers. Courier and live tracking belong to a delivery build, so these rows leave them out.
GoodFirms' 2026 healthcare benchmark puts a mid-complexity app at $80,000 to $150,000. The scope splits are our editorial read of a pharmacy build.
Price HIPAA by control and upkeep by ratio
Push back on any quote that adds HIPAA as a percentage of the build. HIPAA cost depends on how many screens and services touch PHI, and which controls each needs:
- access control
- audit logging
- encryption
- a signed BAA behind every vendor that handles patient data
Our breakdown of pharmacy app development cost prices those controls one at a time.
The same GoodFirms guide (April 2026) puts annual maintenance at 15 to 25% of the initial build: $12,000 to $20,000 a year on an $80,000 app, and $22,500 to $37,500 on a $150,000 one.
Build the ROI model on numbers you own
Only you have the return side: your order volume and your margin. The cost side you can pin down before anyone writes code, from the build tier and maintenance line to HIPAA-grade vendor accounts.
Keep savings percentages and AlgoRX's one-company results out of your inputs. A payback date built on an untraceable number is a guess with a spreadsheet around it.
Building on Specode starts at $1,000 a month
A working prototype fits inside one month of Pro. The line items:
- Pro: $1,000 a month with 2,200 credits, one published project, production deployment, hosting setup and a custom domain.
- Credit top-ups: 50 credits for $20, 300 for $100 or 800 for $260 if a build runs long. Credits don't roll over.
- Custom: From $5,000 a month (Specode docs, 2026), adding unlimited published projects, managed services and coding by Specode's engineers, custom AI agents, advanced integrations and a dedicated team.
- Your own accounts: Production runs in your GitHub and Convex accounts, and third-party services such as messaging, video, eRx or analytics bill separately, with their own BAAs where they handle PHI.
Billing is monthly and you can cancel whenever you like. Export the code first, because the production app goes offline when the subscription ends.
Compliance: the pharmacy carries most of the load
Pharmacy app development answers to HHS, DSCSA, DEA and CMS rules, plus a board of pharmacy in every state you ship into. IBM's Cost of a Data Breach Report 2026 puts healthcare breaches at $6.64 million an incident against a $4.99 million global average, the costliest sector for the thirteenth year running.
HIPAA compliance means decisions you can document
A pharmacy that bills insurance electronically is a covered entity (45 CFR 160.103); a cash-only pharmacy may fall outside HIPAA, so check with counsel.
No app can be HIPAA certified: HHS issues no certificate and recognizes no private ones. The Security Rule asks for a risk analysis, risk management and periodic evaluation (45 CFR 164.308), and an auditor looks for these decisions in writing:
- Encryption: The Security Rule marks it addressable: implement it or document an equivalent. Implement it at rest and in transit to the NIST standards in HHS's breach guidance, and a stolen backup stays out of breach notification.
- Audit controls: 45 CFR 164.312(b) makes recording and examining activity in systems holding ePHI a flat requirement.
- Vendors: Under 45 CFR 164.308(b)(1), a vendor touches ePHI only after written assurances, in practice a signed BAA. Logs count: Datadog allows PHI only in its HIPAA-eligible services, and Sentry's business associate amendment starts at Business-tier plans.
Specode's production release path stacks the checks
On Specode, the layers add up:
- Synthetic data: Preview URLs aren't HIPAA-compliant, so you build and test on synthetic data.
- Your own infrastructure: Production runs in your own GitHub repository and Convex account, under Convex's self-serve BAA, and Specode keeps a deploy-only key.
- Team review: Specode reviews security and HIPAA compliance before you publish, usually within 1 to 2 business days.
- Independent assessment: A third-party security assessment comes before any real PHI.
- Rollback: Every release is tagged with a rollback path.
- Optional pen test: $3,000 in-house, when procurement or an enterprise customer asks for the report.
Underneath, the HIPAA Compliance Agent scans your code across 11 categories, fixes what it finds and rescans in about 3 to 4 minutes for roughly 1 credit. The proposed 2027 requirements, mandatory MFA among them, show up as recommendations you can adopt early or suppress.
Only encryption in transit and at rest is handled for you. Role-based access control, MFA and HIPAA audit logging get built when you ask, and the compliance call stays with you and your counsel.

Payments: Stripe needs approval for a pharmacy
Stripe's Restricted Businesses policy lists online pharmacies and prescription pharmaceuticals as restricted, so Stripe has to approve you first, and it doesn't sign a BAA. We work with Stripe to get restricted healthcare customers approved case by case, so talk to us before you switch.
Selling, dispensing or facilitating prescription drugs is one of six situations Specode's payment guide flags for a BAA-signing processor. PaymentCloud, Corepay, Payment Nerds and Seamless Chex sign BAAs and take Rx and pharmacy merchants; Square signs a BAA for permitted clinical billing, but its terms prohibit online pharmacy.
Visa and Mastercard set certification and monitoring requirements for card-not-present pharmacy merchants and recognize LegitScript Healthcare Certification and NABP Healthcare Merchant Accreditation. LegitScript charges $975 to apply plus $2,150 a year, per website (LegitScript, 2026).
Keep diagnoses, CPT codes and drug names off statements, metadata, receipts and refund notes, because a drug name on a card statement is a disclosure.
DSCSA puts the tracing duties on the pharmacy
Under DSCSA the pharmacy is the dispenser, and dispensing to a patient isn't a DSCSA transaction (21 U.S.C. 360eee). Your app carries the tracing data without becoming a trading partner.
The enhanced electronic requirements are in force, but on August 6, 2026 FDA extended the small dispenser exemption to November 27, 2027 for pharmacies whose owner has 25 or fewer full-time licensed pharmacists or qualified pharmacy technicians, and, where applicable, their trading partners.
The extension covers electronic tracing only. A dispenser still checks supplier licenses, keeps tracing information for six years and quarantines suspect product (FDA, 2024), and a small partner pharmacy needs the electronic path by November 27, 2027.
E-prescribing runs on SCRIPT, and EPCS regulates the software
E-prescriptions travel as NCPDP SCRIPT messages over the Surescripts network. For Medicare Part D, CMS requires SCRIPT 2023011 alone from January 1, 2028 (CMS-4205-F2). Our guide to e-prescription app development covers the stack.
Under the EPCS controlled substances rules in 21 CFR part 1311, DEA compliance starts with an application that has passed a third-party audit or DEA-approved certification, repeated when that function changes or every two years, whichever comes first (21 CFR 1311.300). HIPAA never asks that of software development.
Each prescriber is identity-proofed to Assurance Level 3 or above (21 CFR 1311.105) and signs with two of three factors, any hard token separate from the computer (21 CFR 1311.115). CMS requires prescribers to send at least 70% of qualifying Schedule II to V Part D prescriptions electronically (CMS EPCS Program, 2026), and states can go further.
DEA's telemedicine rules for prescribing controlled substances sit with the prescriber, and our guide to on-demand medicine delivery app development covers them with the courier and tracking layer of a medicine delivery app.
Your launch map is a licensing map
There's no national pharmacy license, so mailing into a state generally takes its nonresident license. Since July 1, 2026, California requires a nonresident pharmacy to name a California-licensed pharmacist-in-charge over its California operations.
Build geography in as a compliance setting, and switch a state on only when its license exists.
Pharmacy app architecture calls are expensive to reverse
Make these calls early in creating a pharmacy app, while changing course is still cheap.
Microservices or monolith: match your release pace
Microservices
Each service runs on its own, so user authentication and inventory management scale separately and a failure stays contained, at the cost of more complexity and up-front spend. That suits clinic pharmacy apps development, where updates ship often and the app talks to EHRs and the pharmacy management system.
Monolithic
One codebase handles everything: simpler and cheaper to build first, harder to scale or change later. If you're one pharmacy with one storefront, start here and split services out as they need to scale.
Scope API integration partner by partner
A pharmacy app is mostly connections to systems you don't own: third-party APIs to EHRs and payment gateways, and custom APIs for the logic you want to control. EHR integration deserves its own scoping pass before anyone commits to a timeline.
On AlgoRX, DoseSpot and Precision Pharmacy's APIs run the prescribing and fulfillment legs, CometChat carries patient and provider messaging, and NMI handles payments for PCI-DSS.
Database design follows the shape of the data
Keep structured data such as patient records and order history in relational (SQL) storage, and unstructured data such as chat logs and real-time analytics in NoSQL. At high transaction volumes, distributed databases like MongoDB carry the load, and field-level encryption protects sensitive information inside the database.
If you build on Specode, the generated React, Tailwind, Shadcn and Convex code is a standard stack with no vendor lock-in, so any development team can pick it up (Specode docs, 2026).
Speed work that pays off early
- CDNs: Cut latency for distant users.
- Caching: Takes load off the server for frequently read data.
- Cross-platform frameworks: If you ship native iOS and Android apps, Flutter or React Native keeps one codebase behind both.
Implementing your pharmacy app: people set the pace
Launch day is where pharmacy app development turns into an operations project.
Change management decides the rollout
Prosci's benchmarking research found that 88% of initiatives with excellent change management met or exceeded their objectives, against 13% with poor change management, and the excellent group was nearly 5 times more likely to finish on or ahead of schedule (Prosci, 12th edition, 2023). Success factors in a pharmacy rollout:
- Start in 2 or 3 pharmacies and widen after the pilot's feedback is closed out.
- Name a champion in each functional area.
- Give staff an escalation path for mid-shift problems.
Train staff by role and patients by first refill
Make the technicians who learned the app fastest in the pilot everyone's first call, then train by role: dispensing staff on processing prescription drugs and managing inventory, customer support on the admin panel.
Patients should finish setup able to complete one refill or transfer, with a visible way to reach a pharmacist. Gartner predicts that by 2029 agentic AI will resolve 80% of common customer service issues without a human (Gartner, 2025). Treat it as a forecast: a bot can say where an order is, and drug interaction counseling stays with a pharmacist.
Budget for technical debt and gate every release
Technical debt was the top frustration in Stack Overflow's 2024 Developer Survey, named by 62.4% of professional developers, roughly double the next answer (Stack Overflow, 2024). We reserve about a fifth of every sprint for paying it down.
The release pipeline is the other half of application development for pharma: automated tests on refill, dispense and payment as a release gate, feature flags that reach one pharmacy first, and separate staging.
In pharmacy application development, prescription processing time and error rates decide what the next sprint fixes.
Pharmacy app development approaches: weigh time against ownership
There are 3 ways to get a pharmacy product built, and the pharmacy app development choice hinges on how long you can wait and who owns the code afterwards.
Custom builds buy control with time
Building from scratch is the classic route in pharmaceutical app development: you control every screen and integration, and your team carries the maintenance.
Past the full-featured tier, GoodFirms puts enterprise apps defined by advanced security and compliance work, HIPAA included, at 12 to 18+ months and $250,000 to $500,000+ (GoodFirms, August 2026). Custom earns that bill when the product itself is the unusual part, and our Custom Healthcare Software Development guide covers that route.
Low-code is fast until ownership comes up
Low-code and no-code platforms can get an online medicine storefront working in weeks. Inside the vendor's platform, though, an acquirer or compliance review asking who owns the code gets an uncomfortable answer, so ask before you sign whether you can export the full codebase and run it without the vendor.
AI builders are where we'd start a pharmacy app
Specode is an AI builder made for healthcare. You describe your pharmacy flow in plain English, from prescription upload through eligibility and provider review to billing, and Maestro's 3 agents scope the MVP, set the design system and write the code.
You approve the roadmap and design before any code exists, test in a live preview on sample data, and connect e-prescribing and pharmacy routing through your vendors' APIs.
- Speed: Specode's healthcare skills cover intake, scheduling, provider profiles and search, admin UX, MFA and Twilio SMS, so the build time goes to prescription handling.
- Ownership: You own 100% of the code (terms, Section 8.2), and a 60-day export window applies if you leave.
- Platform: Specode builds responsive web apps for the phone browser; native iOS and Android are out of scope. If your plan says pharmacy mobile app, decide early whether that means the browser or the app stores.
Apps already on Replit, Lovable, Base44, Emergent or Supabase come across through Specode's migration agent (in beta), which rewrites what isn't safe for patient data and hands it to the HIPAA agent.
Our take for a pharmacy: start on HIPAA-ready infrastructure and spend the schedule on prescription intake, eligibility and pharmacy routing.
A real pharmacy app built on Specode
AlgoRX built and scaled their platform on Specode. It's a medication storefront, and its case study publishes 3 results:
- 12x ROI
- more than $1M in sales closed by month 2
- a 7-figure ARR within 6 months of launching
Three workflows run behind the storefront
On AlgoRX, each prescription routes across partner pharmacies by state law, price and stock. The cart persists between visits, and orders that fail eligibility get refunded.
Providers on AlgoRX work from a SOAP note pre-filled from the patient's questionnaire answers. One click approves the prescription and triggers the pharmacy order, and the prescription history is immutable.
Admins run medications and provider workflows from one dashboard.
The ownership clause, exercised
AlgoRX then brought development in-house as the company grew: the Section 8.2 ownership promise, put to use by a pharmacy business with revenue on the line.
Your starting template arrives within a week
Book a demo and we'll scope the app with you. Within a week of signing up you get a custom starting template built for your product, with a walkthrough video, and support runs 24/7 at support@specode.ai.
Whichever pharmacy app development company you shortlist, ask it for the same 2 things AlgoRX's story shows: a live pharmacy product with results you can check, and a codebase you could take with you.
Frequently asked questions
From scratch, $40,000 to $80,000 for an MVP, $80,000 to $150,000 for mid-complexity and $150,000 to $300,000 or more for full-featured, plus 15 to 25% of the build a year in maintenance. On Specode, Pro is $1,000 a month plus your vendors' fees.
From scratch, 3 to 5 months for an MVP, 5 to 9 for mid-complexity and 9 to 12 or more for full-featured. On Specode, a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build.
Yes, once the pharmacy bills insurance electronically and becomes a covered entity, and an app company handling that patient data needs a signed BAA. A cash-only pharmacy may fall outside HIPAA, so check with counsel. No app can be certified, because HHS issues no HIPAA certificate.
The duties sit with the pharmacy; the app carries the data. A dispenser accepts prescription drugs only with tracing information, keeps it for six years, checks supplier licenses and quarantines suspect product. Qualifying small dispensers have until November 27, 2027 to trace electronically.
The shorter path is a pharmacy management system that already has a Surescripts link; the longer one is a vendor building and qualifying its own. Messages travel as NCPDP SCRIPT, and CMS requires version 2023011 alone for Medicare Part D from January 1, 2028.
The software itself becomes regulated. An application that creates, signs, transmits or processes controlled-substance prescriptions needs a third-party audit or DEA-approved certification before use, then again when that function changes or every two years, whichever comes first.


