
How to Build a Telemedicine App in 2026: A Step-by-Step Guide

Updated October 2026
Telemedicine app development in 2026 comes down to seven decisions: one care workflow, the rules that apply to it, an MVP scope, a build route, a tech stack, the integrations, and a pilot.
A traditional build of that MVP runs $150,000 to $300,000 and four to six months; an AI builder gets a first working version up in about 10 minutes and a basic telehealth app in one to two weeks.
If you're a founder or part of a product team, you need to balance telehealth app development speed with HIPAA, licensure, and prescribing rules.
How do you build a telemedicine app in 2026?
Pick one care workflow and business model, check which regulations apply to it, scope a small MVP (video visits, scheduling, intake, charting, e-prescribing and payments on a HIPAA-ready backend), then choose how to build it. Traditional development runs four to twelve months and $150,000 to over $1 million by tier; the AI route reaches a first working version in about 10 minutes and a basic telehealth app in one to two weeks.
Key takeaways:
- Start from one care workflow. How to build a telemedicine app is really four questions: which workflow, for which buyer, with which revenue model, under which rules. Settle all four before any code.
- Regulations set the timeline. The DEA telemedicine prescribing flexibilities expire December 31, 2026, and Medicare's extension runs through December 31, 2027. Check both before scoping the MVP.
- The MVP is video, scheduling, intake, charting, eRx and payments on a HIPAA-ready backend. Everything else waits for v2.
- The build route decides cost. Custom teams quote $150,000 to $400,000 and four to twelve months for development, depending on scope; an AI builder produces a first working version in about 10 minutes and a basic telehealth app in one to two weeks. For the broader build-versus-buy decision, our custom healthcare software development guide covers cost, process and partner choice.
What is telemedicine app development?
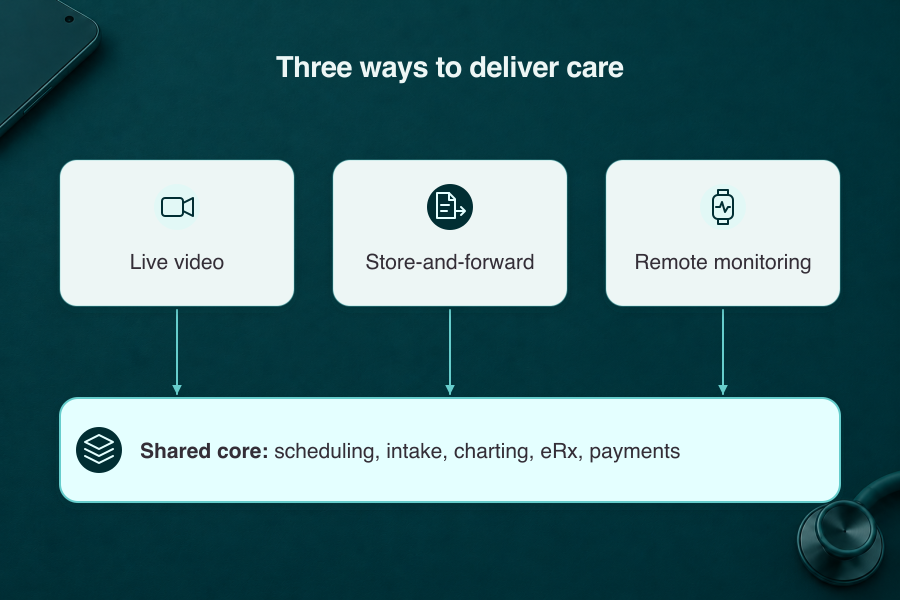
Telemedicine app development means building the software that delivers care remotely: live video visits, store-and-forward consults, and remote patient monitoring, supported by the scheduling, intake, charting, e-prescribing and payments that make a visit work end to end, on a HIPAA-ready backend.
For telemedicine platform development, connect video calls with the rest of the visit workflow: scheduling, records, prescribing and billing. Staff shouldn't need to transfer information manually.
The three core telehealth modalities
- Live video: A scheduled or on-demand video consultation between patient and provider, with a waiting room and pre-call checks. The default mode for urgent care, primary care and follow-ups.
- Store-and-forward: The patient sends data or images, the provider reviews them later. Dermatology photos, intake forms, lab results. Asynchronous visits like these don't require a scheduled appointment.
- Remote patient monitoring: Devices stream vitals and trends over days or weeks, keeping patient care continuous between visits for chronic conditions and post-surgical recovery.
The telemedicine market in 2026
Grand View Research puts the US telehealth market at $28.3 billion in 2025 and an estimated $31.6 billion in 2026, heading to $51.4 billion by 2031.
Investment continued: Rock Health counts $14.2 billion across 482 US digital health deals in 2025, the highest total since 2022.
Usage has settled into routine: across 411 million US primary care visits from July 2022 to October 2025, telehealth held around 6 to 7 percent of visits, just under 6 percent by late 2025, per Epic Research.
In 2026, virtual care is routine across the healthcare industry. Healthcare organizations need to make online and in-person visits work together for patients and doctors.
A narrowly focused service with clear reimbursement has an advantage over generic urgent care by video. New entrants can focus on a specific patient journey, integrate with the systems it uses, and improve a metric payers track.
How to build a telemedicine app in 7 steps
Start with one workflow when you're deciding how to develop a telemedicine app. Check its rules, scope the MVP, choose a build route and stack, connect integrations, then pilot.
Your plan for how to build a telemedicine app should record one decision and one deliverable for each step.
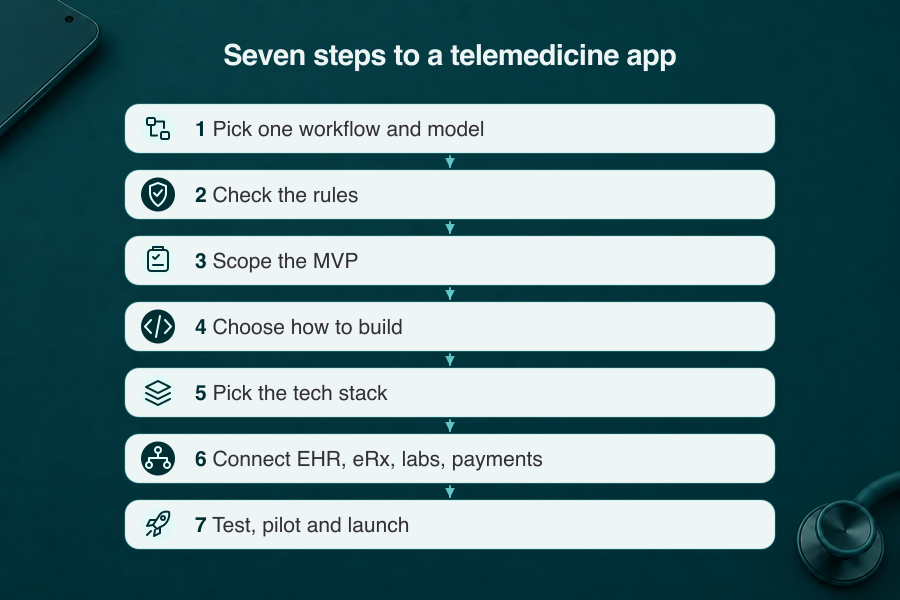
- Pick one care workflow and business model before writing requirements.
- Check which rules apply to your care model: HIPAA, state licensure, controlled-substance prescribing, Medicare billing.
- Scope an MVP you can ship in months, and write down what waits for v2.
- Choose how to build it: a custom team, a white-label platform, a no-code tool, or an AI builder.
- Pick a tech stack from the table in the architecture section.
- Connect the EHR, e-prescribing, labs and payments your workflow actually uses.
- Test, pilot and launch, starting with one clinic in one region.
Step 1: Pick one care workflow and business model
Start by deciding who pays and how. If you're deciding how to create a telemedicine app for patients versus how to create a telehealth app for clinics, the software is the same; the naming changes with the audience. Choose the buyer and revenue model first.
Doctor consultation app development is the simplest DTC entry: appointment booking plus video, with a pharmacy connection for the eRx.
A web-first DTC product usually starts from telehealth website development patterns, and our doctor appointment app development guide covers the booking flow. B2B procurement takes longer: security review, BAA paperwork, and a pilot before any contract, because healthcare providers and payers buy cautiously.
Step 2: Check which rules apply to your care model
Four rule sets decide what you may build:
- HIPAA, when you're a covered entity or a business associate handling patient data, with a BAA behind every PHI-touching vendor
- state licensure, since clinicians must be licensed where the patient sits, so the scheduling engine routes by jurisdiction
- DEA telemedicine rules for controlled substances, which expire December 31, 2026, with state PDMP checks and hard-stop rules inside the prescribing flow
- Medicare billing under flexibilities extended through December 31, 2027, set in billing config rather than code
The compliance section walks through each one with the dates checked.
Step 3: Scope the MVP
Your minimum viable product tests the core workflow for one segment: follow-up visits for one specialty in one region, say. Ship it compliant and safe, and write down what waits.
Each feature added to v1 delays feedback that informs v2. Check whether a real clinic can run its core workflow with the MVP.
Step 4: Choose how to build it
How to build a telemedicine platform depends on who writes the code. Four routes, different risk profiles:
A white-label telehealth platform limits differentiation; our healthcare app builder comparison covers how far generic no-code HIPAA coverage actually goes. The AI builder route is the newest option: a HIPAA-ready foundation you shape by describing the workflow, with the code yours to export.
Step 5: Choose the tech stack
Pick from the stack table in the architecture section. The short version: a web frontend for providers and staff, a mobile-first patient experience, a modular monolith backend, Postgres with FHIR-like data models, and a cloud with a signed BAA.
Step 6: Connect EHR, eRx, labs and payments
Your workflow decides which integrations are mandatory. Most telehealth products need an EHR connection, a Surescripts e-prescribing link, lab orders and results, real-time insurance eligibility, and payments. The integrations section lists the patterns for each, so return there after the MVP is scoped.
Step 7: Test, pilot and launch
Run short sprints of two to three weeks with clinicians in every review, and use a repeatable deployment process: infrastructure as code, CI that runs security scans, feature flags for staged rollouts.
Before anyone outside the team touches the product, run end-to-end clinical flow tests and scenario tests (failed payments, dropped calls, double bookings, clinician no-shows). Then pilot on one tightly defined slice for six to twelve weeks, with three to five success metrics up front: share of visits that went virtual, no-show delta, clinician satisfaction, time-to-note.
Partnerships with EHR marketplaces or specialty groups only pay off with a clear value exchange on both sides, and international expansion waits until one market runs profitably.
Reserve a real launch budget for positioning and outreach, and cut the channels that never produce encounters. Instrument the funnel from the first pilot: activation, conversion, drop-offs, NPS, clinical and operational KPIs.
Must-have telemedicine app features
The essential telemedicine app features in 2026 cover each stage of a visit. In telehealth app development, complete the core workflow before adding optional features.

Video consultations and virtual waiting room
The video layer runs on WebRTC through a HIPAA-covered provider. Route the right patient to the right provider, show their context before the call connects, and maintain reliable calls on weak Wi-Fi.
The virtual waiting room is where intake finishes: consent signed, insurance checked, so the clinician starts the visit instead of collecting paperwork. Run device checks, encrypt video traffic, and use regional media servers for video calls.
Appointment scheduling
Scheduling must account for availability, time zones, visit types and licensing jurisdictions. Patient and provider profiles drive the matching, and an admin panel lets staff override rules and clean up double bookings without filing an engineering ticket.
Intake, e-consent and patient profiles
Intake collects what the visit needs: demographics, history, questionnaires, insurance.
E-consent records what the patient agreed to and when, with the signed document stored against the profile. Patient profiles carry the record across visits, so users don't need to re-enter medication lists. Keep the forms short, plain-language, and readable on a phone.
Charting and EHR access
Keep electronic health records access scoped: decide how much of the chart you need in-product and how much stays in the source system, then design APIs around access control, audit trails and encryption. Record every view and edit in the audit trail, including who did what and when.
The integration mechanics (FHIR, HL7v2, sync engines) live in the integrations section; here the rule is scope discipline.
E-prescribing
When a clinician writes prescriptions, the flow needs structured medication search, a live eRx connection, role-based approval flows, and clean refills and prior authorizations. The compliance section covers the DEA rules that govern controlled substances; the pharmacy delivery app guide covers the fulfillment workflow if it's yours to build.
Payments and insurance eligibility
Stripe is available by default for non-clinical apps; for telehealth and prescribing, the category is restricted and the Specode team helps customers through approval, with BAA-signing processors available where that fits better.
Keep PHI out of payment records either way. Real-time eligibility checks turn into one status per visit: clear, unclear, or needs manual.
Secure messaging and notifications
Secure messaging is where follow-up happens between visits, and notifications send timely reminders. Adding adherence reminders turns the medication reminder development guide pattern into a retention feature.
Admin analytics
Trim analytics to what operations and leadership actually use: time-to-visit, no-show rate, utilization by provider, cost and revenue over time. Clinicians get panel-level trends. Patients remember the user experience of the visit flow; the dashboard is for the ops team.
AI features worth building in 2026
Four AI features have practical uses in production:
- symptom triage with a deterministic rules layer
- ambient documentation (the AI medical scribe / ambient documentation pattern) that drafts the note, with clinician sign-off
- no-show prediction that triggers outreach before a likely missed visit
- patient chatbots that hand off the moment anything turns clinical
Computer vision for diagnostics is real but emerging; most teams should watch it rather than build it. Require every output to include reasoning, a version stamp, and an override, so AI supports accurate diagnoses while clinicians retain the decision.
Telemedicine app tech stack and architecture
Telemedicine software stacks include web and mobile frontends, a backend, databases, video, cloud hosting and observability. For telemedicine platform development, use this table to assess each layer and its audit requirements.
Web and mobile frontend
Telemedicine mobile app development splits two ways: one codebase across iOS and Android (React Native or Flutter), or native when you need deep OS integration and a native video stack. Most 2026 products use a hybrid approach: web-first for providers and staff, mobile-first for patients, one design system.
Use role-based interfaces driven by feature flags so one codebase serves patients, providers and staff. Specode builds responsive web apps that work in mobile browsers; native mobile app generation isn't in scope, so a native telemedicine mobile application means a mobile team on that layer.
Backend: start with a modular monolith
To build a telemedicine platform in-house, start with a modular monolith and clear domain boundaries (auth, scheduling, encounters, billing). Split into microservices when a domain like video needs to scale independently or teams need to work separately.
Keep APIs versioned, data owned per service, and observability in place before the first split. Event-driven processing (appointment booked, reminders scheduled, video room created) provides replay and auditability that cron jobs don't.
Database design for healthcare data
Postgres is a practical default, with row-level security for multi-tenant platforms and FHIR-like structures (conditions, observations, medications, care plans) even if you never ship full FHIR. Add object storage for imaging and signed consent, a search index for chart and message search, and a time-series store for RPM data.
Every health data table needs clear ownership, audit logging, soft deletes, and an export path for audits and payer disputes.
Cloud hosting with a BAA
AWS, Google Cloud and Azure all offer HIPAA-eligible services and BAAs in the US. Beyond eligibility, compare managed services, data residency, and the scope of attestations (SOC 2, HITRUST).
If you create a telemedicine platform with Specode, use a customer-owned Convex Pro account with Convex's BAA signed, plus a security and HIPAA review before launch.
Telemedicine compliance: HIPAA, licensure and prescribing rules
How to build a telemedicine app depends on six compliance areas: HIPAA, state licensure, prescribing, Medicare reimbursement, international rules and security. Check the current dates that apply to your care model.

When HIPAA applies to a telemedicine app
HIPAA binds covered entities (most clinicians and health systems) and their business associates. A telemedicine app built for them signs a Business Associate Agreement (BAA) with every PHI-touching vendor: cloud, video, messaging, eRx.
Apps outside HIPAA still answer to other rules: the FTC Health Breach Notification Rule (16 CFR Part 318) covers health apps and personal health records with breach duties, and Washington's My Health My Data Act gives consumers health-data rights with a private right of action.
Our backend-only vs. full-platform HIPAA article explains the distinction between a backend-only HIPAA layer and a full platform.
State licensure and cross-state care
Clinicians must hold a license in the state where the patient is located at the time of the encounter.
Interstate licensure / Interstate Medical Licensure Compact (IMLCC) offers an expedited pathway to multi-state licensure rather than a license itself, with 46 jurisdictions (44 member states plus DC and Guam) participating as of September 30, 2026. For the product, that means the scheduling engine routes providers by jurisdiction and blocks mismatches before booking.
Prescribing controlled substances via telemedicine
The Ryan Haight Act / DEA telemedicine rules include an in-person requirement: the 2008 statute generally requires an in-person medical evaluation before a practitioner prescribes a controlled substance via telemedicine.
As of October 20, 2026, the DEA/HHS fourth temporary extension (90 FR 61301) still lets DEA-registered practitioners prescribe Schedule II-V substances without a prior in-person visit, but it expires December 31, 2026. The final special registration rule sat under White House review as of this date, so re-check before year end.
Medicare telehealth reimbursement through 2027
The Consolidated Appropriations Act, 2026 (H.R. 7148, enacted February 3, 2026) extended Medicare telehealth flexibilities through December 31, 2027: the patient's home as an originating site, no geographic restrictions, and audio-only telehealth for certain services.
GDPR and international rules
Outside the US, GDPR and UK GDPR add a legal basis, DPIAs and regional hosting; local health-data rules also apply (France's HDS, Germany's S3). Cross-border transfers add standard contractual clauses and explicit data mapping. Design jurisdiction tags per tenant and dataset before the first audit.
Security baseline checklist
Use these ten items as your data security baseline:
- BAAs with PHI-touching vendors
- OIDC/OAuth2 with MFA for clinicians
- RBAC and row-level security
- TLS 1.2+ everywhere
- KMS-backed encryption at rest
- field-level encryption for notes
- append-only audit logs with a normalized schema
- SAST/DAST in CI plus periodic third-party penetration tests
- threat modeling for new PHI surfaces
- tested incident runbooks
Specode's HIPAA Compliant App Builder includes these defaults for further configuration.
Telemedicine integrations: EHR, eRx, labs, payments and devices
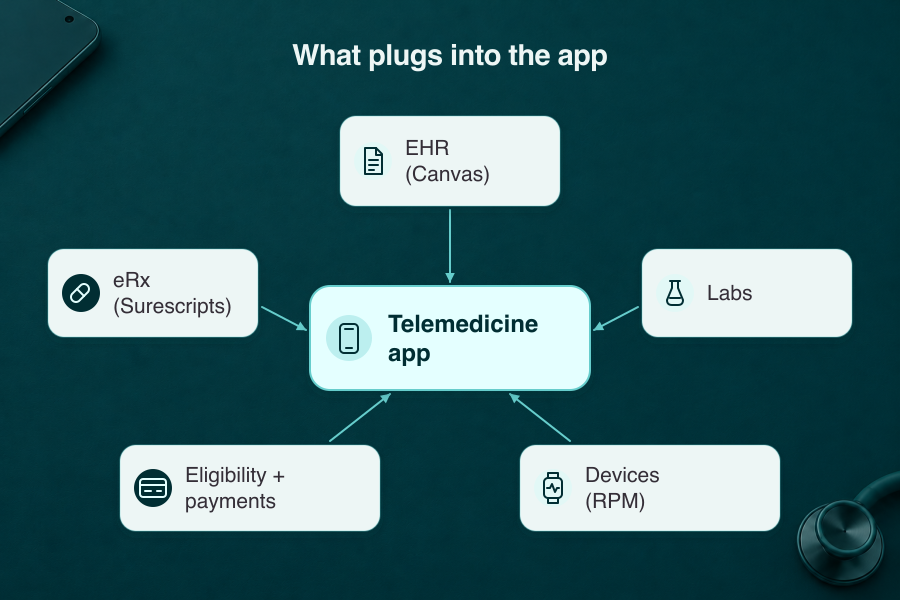
To develop a telemedicine app for a health system, prioritize data contracts and ownership for each external connection over UI details. Integrations affect the launch date more than features do.
EHR/EMR integration
Define the minimum set of medical records you need in-product (encounters, problems, meds, results) and adopt FHIR / HL7 models even when the other side still runs HL7v2. Split sync engines by workflow so one vendor's failure can't cause the entire platform to fail, and give ops reconciliation tools.
Canvas Medical is an AI-powered healthcare platform for clinics whose EMR is customizable through an SDK and FHIR API, and it works as the full EMR option where it fits; EHRs like Epic and Cerner are handled case by case. This is also where the broader healthcare app development question gets answered in practice.
Laboratory system connections
Labs use HL7v2 ORM/ORU with LOINC codes. Run a lab broker service that normalizes outbound orders, validates inbound results, maps codes and stores raw payloads for audit. Never let the core app parse lab messages directly.
Pharmacy integration
Prescribing uses e-prescribing (eRx) / Surescripts networks, with NCPDP for eligibility and formulary checks. Build it append-only: clinician intent, structured order, transmission, acknowledgment, dispense event. Controlled substances add state PDMP checks and hard-stop rules.
Insurance verification
Real-time eligibility verification checks visit type, co-pay, deductible and plan-specific telehealth rules before the visit. Cache and batch checks before the day starts, keep payer quirks in config, and summarize the payer codes as one status for staff.
Medical device integration
RPM flows need device-agnostic ingestion: normalize every measurement into a time-series model carrying device ID, firmware, calibration and patient binding, then validate ranges and rate-of-change before a clinician sees anything.
Third-party API management
A telehealth stack can use 15 to 30 external services. Keep an API gateway, a provider registry listing each dependency's data contract and BAA status, decoupled adapters with retries, and fallback paths (SMS when push fails). Use the adapters to change vendors when costs or compliance requirements change.
Telemedicine app development cost and timeline
Telemedicine app development cost is a range per tier. For a detailed breakdown, see our telemedicine app development cost article.
What drives the cost up or down
You're paying for foundations, core workflows, integrations and UX polish. Every step that involves clinical logic or regulated data costs more because it requires a development team, quality assurance and compliance work: closing audit findings, syncing documentation with implementation, penetration testing and remediation.
The cost increases fastest when you build without reusable components. The same cost article notes Western team rates, with nearshore or offshore teams cutting 40 to 60 percent while requiring more project management.
Ongoing costs after launch
After v1, budget for ongoing costs. From the cost article: $2,500 to $5,000 a month in maintenance for a basic app, $8,000 to $20,000 for an enterprise build, plus hosting, security tooling and the integration upgrades vendors force on you. Budget regulatory and payer changes as certainties.
ROI timeline
The cost article's working figure is positive ROI within 12 to 18 months through fewer no-shows, better utilization and new revenue. When you create a telemedicine app as a business, building a telehealth app is a capex decision: map each outlay to the metric it should move, and you can defend the budget in front of a CFO.
Common telemedicine app development challenges
When you make a telemedicine app, plan for three main challenges after launch: user adoption, performance and change management. The causes of failure are rarely technical.
User adoption
Design the app around clinicians' existing day: keep the same shortcuts and data, with fewer clicks. Teams with years of experience bring clinicians into weekly reviews while the app's still in development.
Give patients one obvious path to the first task, and measure adoption honestly: share of visits through the app, repeat usage, clinicians choosing it without being asked.
Performance
Define SLOs for join time, call quality, page loads and error rate, and test them with load and chaos runs. Move eligibility checks, notifications and batch reporting onto queues, and scale with autoscaling and honest capacity planning. This helps you manage reliability and cloud costs together.
Change management
Telehealth changes how the organization operates, so physicians and healthcare professionals need owners and superusers who coordinate between the product team and clinical staff. Roll out one service line, one region, one cohort at a time, each with explicit success metrics.
Fix the incentives: if leadership only rewards in-person volume, virtual care stays a side project. Medical care quality depends on how well the software supports the workflow, so clinical expertise matters more here than another feature.
Build a telemedicine app with Specode
If you're deciding how to build a telehealth app, start with Specode's HIPAA-ready foundation and adapt it to your care workflow. When you build telehealth app features with Specode, you get a first working version in about 10 minutes and a basic telehealth app in one to two weeks.
What the AI builds on day one
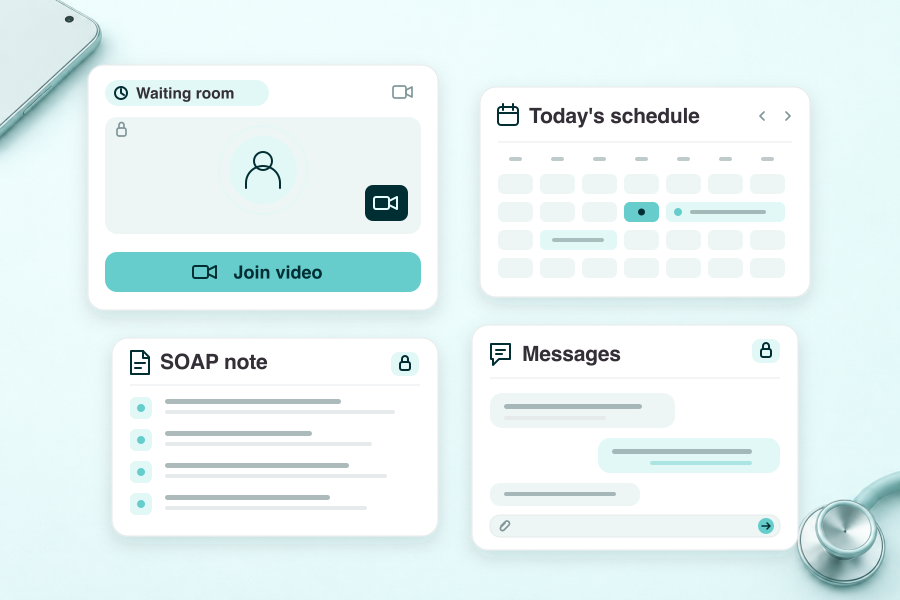
- video visits with a virtual waiting room
- live scheduling and provider profiles with availability
- intake forms and e-consent
- secure messaging and notifications
- a basic EMR with SOAP notes and an audit-ready trail
- payments configured under the processing rules above
The previews run on synthetic patient data only. Real patient data belongs in the separately prepared production deployment.
How the build works: plan, design, code
Specode's build engine, Maestro, runs three agents in sequence: a planning agent scopes the roadmap with you, a design agent shapes the look and feel (pulling direction from screenshots you upload), and an implementation agent writes the app, handling auth, routing, data models and the HIPAA-ready infrastructure underneath.
You approve the roadmap before design and the design before code. You control the development process: describe changes in plain English, then edit the code when you need precision. You can build your own telemedicine application and retain access to its code.
HIPAA Compliance Agent and code ownership
A built-in HIPAA Compliance Agent scans the codebase on demand, splits findings into must-fix and nice-to-fix, and sends fixes back into the chat. And you own the code outright: export it, modify it, deploy it anywhere, with no lock-in (Terms of Service, section 8.2).
Results: AlgoRX and DyadSync
AlgoRX used Specode to launch a medication storefront automating eligibility, provider review, pharmacy routing and checkout: $1M+ in sales by month 2, seven-figure ARR by month 3, a 12x ROI.
DyadSync launched a web platform where freelance surgeons and anesthesiologists find and book anesthesia cases, with role-based onboarding and credentialing, smart scheduling, contextual messaging, payments and reporting.
Our best HIPAA compliant telehealth platforms roundup compares the options on security and scale.
When a custom development agency is a better fit
Choose a custom development agency if you need heavy bespoke integrations or regulated medical device work, or want to hand over the whole build.
For that path, Topflight Apps has shipped telehealth platforms for years. Compare buy-versus-build telehealth solutions before you commit.
Conclusion
Telemedicine app development requires early decisions and verification: one workflow, its rules, a small MVP and a build route that gives you code ownership. Use an AI builder to implement the core workflows, then test them in a pilot.
After launch, keep the stack compatible with remote patient monitoring and AI documentation as your workflows develop over the next two years.
Start telemedicine app development at specode.ai. Describe the care workflow you're building a telemedicine platform for, and see the first version in minutes.
Frequently asked questions
By tier: a basic MVP runs $150,000 to $300,000 and four to six months; a mid-complexity platform about $250,000 to $400,000; an enterprise build $400,000 to over $1 million. The AI route reaches a first working version in about 10 minutes and a basic telehealth app in one to two weeks.
A traditional build takes four to twelve months depending on tier and integrations. With Specode, a first working version is ready in about 10 minutes and a basic telehealth app in one to two weeks, then production prep follows.
It depends on the model. Teladoc Health's Q2 2026 results show $606.9 million in revenue, $65.7 million in adjusted EBITDA and a $38.9 million GAAP net loss.
Hims & Hers' Q2 2026 results show $753.2 million in revenue and an $86.3 million GAAP net loss.
Budget 12 to 18 months to ROI.
Telemedicine apps can earn revenue through subscriptions, pay-per-consultation fees, care bundles and platform licensing. Clinics and health systems can license the software for their own clinicians; employer and health-plan contracts can use per-member-per-month pricing.
Visits can also be billed directly to patients or insurers. Choose the model around your buyer and care workflow, and define which services each price includes.
Live video visits, store-and-forward consults, and remote patient monitoring. Real products usually blend all three plus asynchronous visits and audio-only check-ins.
By build route: an AI builder like Specode for a HIPAA-ready foundation with full code ownership, a white-label platform for speed, or a custom team for bespoke integrations. See the best HIPAA-compliant telehealth platforms roundup for the comparison.
Can I build a telemedicine app without coding?
Yes. Describe the workflow in plain English and Specode's AI builds it on a HIPAA-ready foundation, with the code yours to export and extend.
For Medicare virtual check-ins (G2010, G2012), CMS requires the service not follow a related E/M service within the previous 7 days, nor lead to one within the next 24 hours. Medicare e-visits (99421-99423) must be patient-initiated and are paid by cumulative time over a 7-day period.
When the app belongs to a covered entity or business associate, yes: BAAs, encryption, access controls and audit logs. Apps outside HIPAA still face the FTC Health Breach Notification Rule and state health-data laws.
Through December 31, 2026, the DEA/HHS temporary rule lets DEA-registered practitioners prescribe Schedule II-V via telemedicine without a prior in-person visit, subject to state law. Re-check before year end; a final rule was still under review as of October 20, 2026.



