
Medication Reminder App Development in 2026: Features, Cost, and Compliance

Updated September 2026
One in 5 new prescriptions is never filled. Of the ones that are, about half get taken wrong: wrong time, wrong dose. CDC put the direct health care cost of that at $100 billion to $300 billion a year in its 2017 Morbidity and Mortality Weekly Report, and nobody has published a smaller figure since.
That gap is what medication reminder app development is for: the patient on 5 medications with a GLP-1 titration schedule and a daughter two time zones away, still taking the right dose on Thursday. A notification firing at 8am is the easy 10%.
We've built patient-facing health apps for over a decade, and the hard 90% is everything around the reminder. Which channel reaches the patient. What happens when they ignore it. Where the drug data comes from, and whether it's legal to send by text.
What does it take to build a medication reminder app in 2026?
A medication reminder app schedules doses, delivers reminders by push, SMS or a connected dispenser, tracks what the patient took, and shares that medication adherence record with a caregiver or clinician. Custom development runs $40,000 to $80,000 for an MVP and up to $350,000 for a clinical-grade build; building it on a healthcare app platform like Specode costs about $15,000 for the first year. HIPAA applies only when a provider or health plan hires you; otherwise it's the FTC Health Breach Notification Rule, enforced since 2023.
Key Takeaways:
- The reminder channel decides the product. Web push is free and works on iPhone only for an app added to the Home Screen. SMS costs about $0.013 a message, needs A2P 10DLC registration, and puts a drug name on a lock screen. Most serious builds run both.
- HIPAA probably doesn't cover your medication app. A direct-to-consumer app where users type in their own medications falls outside HIPAA entirely and lands under the FTC Health Breach Notification Rule instead. The FTC has fined GoodRx $1.5 million and Easy Healthcare $100,000 under it.
- You cannot write your own drug interaction logic. RxNorm gives you names and codes for free, but NLM shut off its interaction API on 2 January 2024. Interaction and dose checking comes from a licensed commercial database, quote only, at an estimated $20,000 to $100,000 a year (Appinventiv, 2026), which can make it the build's biggest line item.
- Refill automation and medication adherence are different problems, and the second one is yours. Ordering the refill belongs to the pharmacy. Knowing one is due and measuring whether doses were taken is the adherence product.
- GLP-1s broke the weekly-dose assumption most reminder apps were built on. 64.8% of patients without type 2 diabetes stop within a year, titration runs 17 weeks on Wegovy, and missed-dose rules are conditional rather than skip-or-take.
Medication non-adherence costs $100 billion to $300 billion a year
The case for medication tracking, and for medication reminder app development, rests on 4 numbers quoted constantly and sourced almost never.
The World Health Organization's 2003 report Adherence to Long-Term Therapies found adherence to long-term therapy for chronic illness averages 50% in developed countries, lower in developing ones. Note the scope: chronic illness, not every prescription.
CDC's 2017 MMWR anchors the US picture: about 1 in 5 new prescriptions is never filled, and of those filled, roughly 50% are taken wrong on timing, dosage, frequency and duration.
A 2018 study in Annals of Pharmacotherapy by Watanabe, McInnis and Hirsch put the annual cost of illness and death from non-optimized medication therapy at $528.4 billion in 2016 dollars, with a plausible range of $495.3 billion to $672.7 billion. If CDC's $100 billion to $300 billion feels conservative, that's why.
What the evidence says apps actually do
The effect sizes are real, modest, and they replicate.
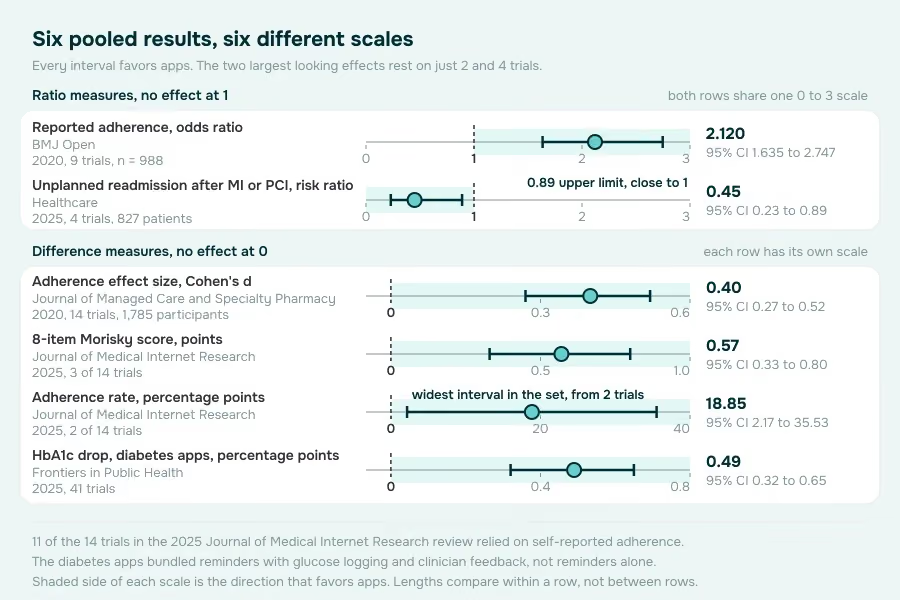
A 2020 meta-analysis in BMJ Open by Armitage, Kassavou and Sutton pooled 9 randomized controlled trials with 1,159 recruited participants. App users were more likely to report taking medication as prescribed, odds ratio 2.120 (95% CI 1.635 to 2.747, n = 988).
A second 2020 meta-analysis, in the Journal of Managed Care and Specialty Pharmacy, pooled 14 trials and 1,785 participants for a Cohen's d of 0.40 (95% CI 0.27 to 0.52).
A 2025 systematic review in the Journal of Medical Internet Research reviewed 14 RCTs. Across the 3 trials scored on the 8-item Morisky scale, app users averaged 0.57 points above controls (95% CI 0.33 to 0.80). In the 2 trials reporting adherence as a percentage, the gap was 18.85 percentage points (95% CI 2.17 to 35.53).
11 of the 14 trials relied on self-reported adherence.
So apps help, just less than the marketing suggests. Clinical outcomes follow the same pattern:
- Blood pressure: a 2022 meta-analysis in JMIR mHealth and uHealth across 15 RCTs and 7,415 hypertensive patients found an average systolic reduction of 1.64 mmHg (7,301 patients in the blood pressure analysis), rising to 2.92 mmHg where apps paired self-monitoring with tailored advice. Apps without tailored advice showed no significant change.
- Diabetes: a 2025 review in Frontiers in Public Health pooled 41 RCTs and found diabetes apps lowered HbA1c by 0.49 percentage points (95% CI 0.32 to 0.65), though those apps bundled reminders with glucose logging and clinician feedback rather than testing reminders alone.
- Readmissions: thin. A 2025 meta-analysis in Healthcare found fewer unplanned readmissions after myocardial infarction or PCI (risk ratio 0.45, 95% CI 0.23 to 0.89), from 4 trials and 827 patients, and the authors' own prediction interval leaves open that a new trial would show no benefit. There's no evidence base for "reduced hospital visits" as a general property of reminder apps.
Build around the effect that replicates: adherence behavior. Be careful about promising the downstream clinical numbers to a health plan.
There's a business model here too: medication therapy management is a statutory Medicare Part D obligation, and section 9 covers who pays.
Medication reminder app development loses more time to regulation than to engineering
5 things decide whether medication reminder app development ships on schedule. Two are regulatory and three are technical, and teams that create a medication reminder app usually lose the quarter to the regulatory pair.
HIPAA compliance is conditional, so settle which product you're building first
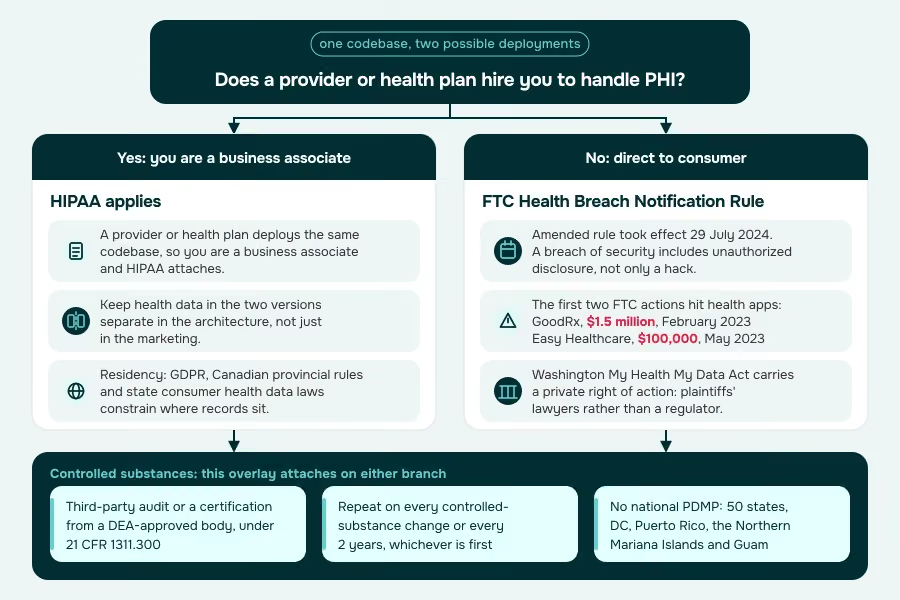
HHS is clear: a consumer app where the user enters their own medications, with no provider or health plan behind it, is not covered by HIPAA. The same codebase deployed for a covered entity is covered, because you're a business associate.
When HIPAA doesn't apply, the FTC does. Its amended Health Breach Notification Rule took effect 29 July 2024 and reaches health apps. Under the Rule, a "breach of security" includes unauthorized disclosure rather than only a hack.
The FTC's first two actions hit health apps: GoodRx paid $1.5 million in February 2023, Easy Healthcare $100,000 in May 2023.
State law adds a third layer. Washington's My Health My Data Act carries a private right of action, meaning plaintiffs' lawyers rather than a regulator.
Budget for residency too: GDPR, Canadian provincial rules and state consumer health data laws constrain where records sit, and retrofitting that during an enterprise deal is painful. Our HIPAA compliant app development cost breakdown has the line items.
Controlled substances put your software in front of the DEA
If prescribers touch controlled substances anywhere in your product, the audit obligation is yours.
21 CFR 1311.300 requires the application provider to obtain a third-party audit, or a certification from a DEA-approved certifying organization, before the app handles a controlled substance prescription. The audit has to come from one of:
- SysTrust
- WebTrust
- SAS 70
- a Certified Information System Auditor
Repeat it on every controlled-substance functional change or every 2 years, whichever is first.
Two requirements sit upstream: prescribers must be identity proofed to NIST SP 800-63-1 Assurance Level 3 by a federally approved credential service provider, and signing takes 2 of 3 factors under 21 CFR 1311.115. Building that signing workflow is prescriber-side work, and section 4 says where that work goes.
Then PDMP reporting. Prescription drug monitoring programs are state databases of dispensed controlled substances, with no national one. The Federation of State Medical Boards recorded in August 2025 that all 50 states, DC, Puerto Rico, the Northern Mariana Islands and Guam run operational PDMPs, each with its own cadence.
EHR FHIR integration is how you learn what the patient is actually prescribed
A reminder app that only knows what the patient typed drifts from reality within a month, and the chart is where allergy and problem data lives. Read-only covers most reminder products. Write-back is a different project at a different price.
Notification architecture is the product
A reminder app is a scheduling engine with a UI attached. Reminder load is spiky: 8am, noon and 8pm local in every time zone you serve. Size for the peak, and keep the scheduler idempotent so a retry doesn't double-dose someone. Quiet hours and fatigue control ship in v1, since the fastest way to lose a patient is 11 notifications a day.
Adherence analytics has to mean measurement
"Adherence analytics" usually means a ring chart counting taps. That is engagement data wearing a clinical costume.
Real measurement means picking a denominator and defending it:
- proportion of days covered, computed from refill data
- medication possession ratio, same source, different arithmetic
- self-report from taps, cheaper and weaker
Self-report is the same limitation sitting under 11 of the 14 trials in that 2025 review.
Decide early which one you're reporting to a clinician, because it changes the data model.
The features that separate a medication reminder app from a to-do list with alarms
If you're working out how to build a medication reminder app, this is where medication reminder app development budgets are won or lost.

Authentication and profile, with a medication list that came from somewhere real
Role-based access: patient, caregiver, clinician, admin. The profile carries dose, schedule, prescriber, pharmacy and allergies, imported rather than typed. Typing 8 medications into a phone is where consumer apps lose the user.
Dose scheduling that handles the regimens people are actually on
Once daily at 9am covers easy patients. The hard ones are why the app exists: multiple daily doses with food rules, tapering courses, PRN meds tracked without nagging, weekly injections with conditional missed-dose rules.
Model time windows rather than timestamps. "Between 7 and 9am" is what the prescription means, and it makes adherence scoring honest.
Refill tracking predicts the run-out date
Count the supply down from dispense quantity and schedule, and nudge in time for the pharmacy to fill it. Quantity and days supply come off the e-prescribing network instead of patient memory. Refill ordering belongs to a pharmacy product.
If the medication has to arrive, see medicine delivery app development.
Drug-drug interaction and allergy checking, which you will be licensing
RxNorm from the National Library of Medicine is free: it normalizes generic and branded names and carries NDC codes. The FDA National Drug Code Directory is free too. Neither contains safety logic.
NLM discontinued RxNav's drug interaction features on 2 January 2024, so tutorials pointing at the free NLM API describe a dead endpoint.
Interaction, dose range, allergy and duplicate therapy checking come from a licensed database: FDB MedKnowledge from First Databank, or Medi-Span from Wolters Kluwer. Neither publishes a price.
Budget in two halves: free for names and codes, licensed for safety claims.
GLP-1 workflows, because the weekly-injection patient broke the daily-pill model
Retention is the problem. Across 125,474 US adults with overweight or obesity, 64.8% of patients without type 2 diabetes stopped within 1 year, and 84.4% within 2 (Rodriguez et al., JAMA Network Open, 2025). A Cleveland Clinic study of 7,881 patients in Obesity (2025) found more than 80% never got past a low maintenance dose, and stopping inside 3 months cost most of the weight loss: 3.6% against 11.9% for those who stayed on.
It's improving: 1-year persistence rose from 33.2% for 2021 starters to 60.9% for first-half-2024 starters (Marshall et al., Journal of Managed Care & Specialty Pharmacy, 2026).
What that means for the build:
- Titration is a schedule rather than a dose: Wegovy steps up from 0.25 mg weekly at 4-week intervals to 2.4 mg maintenance at week 17. Zepbound rises from 2.5 mg in 2.5 mg steps, 4 weeks minimum per step.
- Missed-dose rules are conditional: Wegovy's label says take it if the next dose is more than 2 days away, skip it if less; 2 or more consecutive misses and the prescriber may restart escalation. Zepbound allows a 4-day window.
- Dose-day changes are legal within limits: Zepbound's label allows moving the weekly day if 3 days separate 2 doses. Patients do this anyway.
Cleveland Clinic traced discontinuation to cost, coverage, side effects and shortages, so a side-effect check-in during titration is a retention feature.
Smart pill dispenser and connected-device integration
Software-only is a choice, and for some populations it's wrong.
Hero Health's countertop dispenser holds a 90-day supply of 10 medications, with Wi-Fi app reminders, missed-dose alerts and caregiver monitoring. Subscriptions run $29.99 to $59.99 a month.
MedMinder pairs its dispenser with a pharmacy that pre-sorts doses. AdhereTech's cellular over-cap needs no app. Its site wasn't resolving when we checked in September 2026, so confirm it's trading before you design around it.
Ingestible sensors carry a warning. FDA cleared etectRx's ID-Cap System in 2019 as a Class II ingestible event marker, but Abilify MyCite, the first US drug with an embedded ingestion sensor, is discontinued on every kit product in Drugs@FDA.
Pharmacy integration and e-prescribing: 5 systems, and the slice you actually need
5 systems move US prescription data between prescribers, pharmacies and payers. A reminder app reads a narrow slice of one, and knowing which slice is the difference between a 3-week integration and a 3-month one.
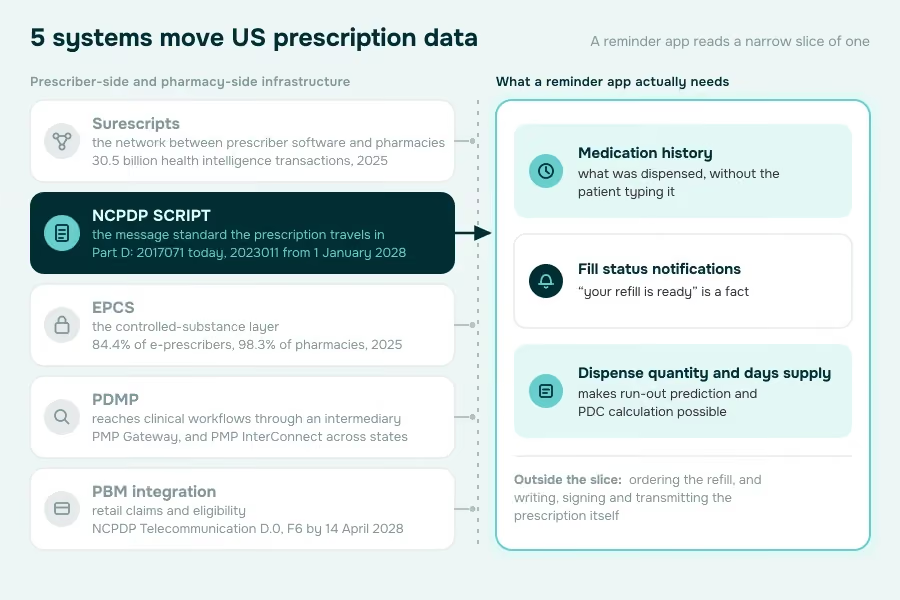
Surescripts runs the network that moves US e-prescribing traffic between prescriber software and pharmacies. Its Annual Impact Report 2025 counts 30.5 billion health intelligence transactions across 2.32 million connected healthcare professionals and provider organizations, with 1.39 million prescribers e-prescribing, up 4.0% year over year.
NCPDP SCRIPT is the message standard the prescription travels in: new prescriptions, changes, refill requests, fill status notifications, cancellations, medication history and electronic prior authorization. CMS requires version 2017071 for Medicare Part D today. Version 2023011 is adopted and usable during a transition period that opened 17 July 2024, and becomes the only permitted version on 1 January 2028.
EPCS is the controlled-substance layer, and it's mainstream now: Surescripts reports 84.4% of e-prescribers and 98.3% of pharmacies enabled in 2025. Section 2003 of the SUPPORT Act requires Schedule II through V drugs under Part D to be prescribed electronically, and CMS treats 70% or more of qualifying prescriptions sent electronically as compliant.
PDMP data reaches clinical workflows through an intermediary, which spares you 50 separate integrations: Bamboo Health's PMP Gateway is the standard route, and cross-state queries ride on PMP InterConnect, operated by the National Association of Boards of Pharmacy.
PBM integration is where the money moves. The FTC's July 2024 interim staff report found the 3 largest pharmacy benefit managers processed nearly 80% of the roughly 6.6 billion US prescriptions dispensed in 2023. Retail claims and eligibility run on NCPDP Telecommunication Standard version D.0 with Batch Standard 1.2, adopted at 45 CFR 162.1102. A final rule published 13 December 2024 names version F6 as the successor, with the compliance date extended to 14 April 2028.
What a reminder app actually needs from all of this
Most of that is prescriber-side and pharmacy-side infrastructure. A patient adherence product touches a narrow slice:
- Medication history, so the app knows what was dispensed without the patient typing it
- Fill status notifications, so "your refill is ready" is a fact
- Dispense quantity and days supply, which makes run-out prediction and PDC calculation possible
Ordering the refill is the other side of that line. The cart and the pharmacist review are a pharmacy operator's product, and our prescription refill app development guide covers that build.
Writing, signing and transmitting the prescription itself is a different product again, with its own audit burden. Our e-prescription app development guide covers that side. Read what you need and stay out of the prescribing workflow unless prescribing is the product.
Customizable reminders live or die on the channel you pick
In pill reminder app development, personalization means the channel a reminder arrives on, what happens when it's ignored, and who else sees that it was.
Pick your reminder channel before you design anything else
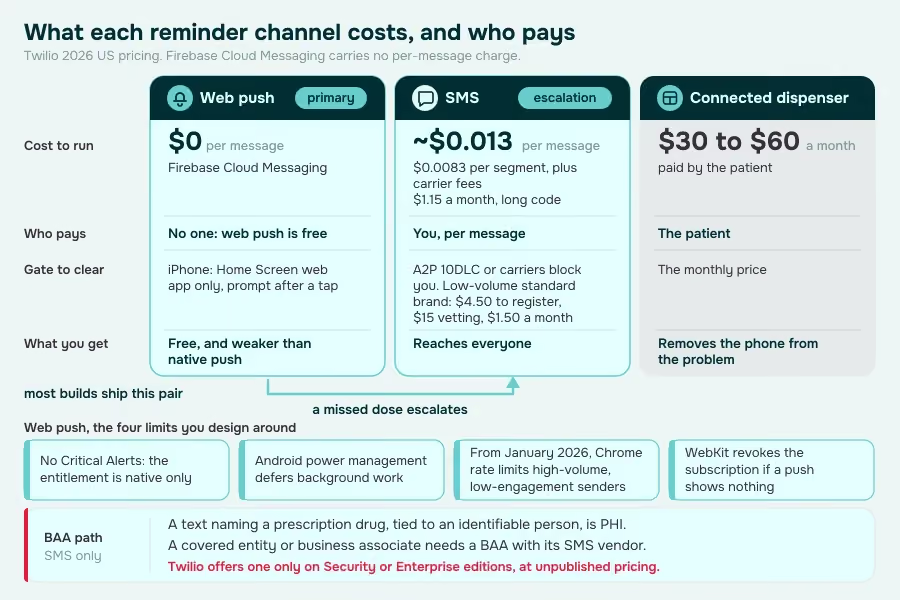
Web push is free: Google lists Firebase Cloud Messaging at no per-message charge. On iPhone there is no web push from a Safari tab: only from a web app added to the Home Screen, and the permission prompt has to follow a direct tap. Apple added it in iOS 16.4. Declarative Web Push landed in Safari 18.4, and on iOS 26 every Home Screen site opens as a web app, no manifest required. Once installed it behaves natively: Lock Screen, Notification Center, paired Apple Watch, Focus, and a Badging API for a dose count.
The limits you design around:
- No Critical Alerts. The entitlement that sounds through a muted or Do Not Disturb device is Apple-granted and native-only; the Web Notifications API has no interruption level.
- Android power management defers background work, and Firebase can deprioritize messages that produce no user-visible notification.
- Chrome began rolling out Push API rate limits in January 2026 for high-volume, low-engagement senders.
- WebKit revokes the subscription if your service worker receives a push and shows nothing.
SMS reaches everyone and costs money. Twilio's 2026 US pricing: $0.0083 per segment plus carrier fees, around $0.013 per outbound message, and $1.15 a month for a long code. Register under A2P 10DLC or carriers block you: $4.50 one-time registration for a low-volume standard brand, a $15 campaign vetting fee, then $1.50 a month.
A text naming a prescription drug, tied to an identifiable person, is PHI, so a covered entity or business associate needs a BAA with its SMS vendor. Twilio offers one only on Security or Enterprise editions, at unpublished pricing.
A connected dispenser removes the phone from the problem, and costs the patient $30 to $60 a month.
Most builds run push as primary with SMS as escalation, because a missed dose has a clinical consequence. Design quiet hours and fatigue control too: the fastest way to lose a patient is 11 notifications a day.
Caregiver access is an adherence feature
The patient on 8 medications often isn't the person managing them. A caregiver view needs alerts; a clinician view needs a defensible measure. Medisafe's Medfriend lets a patient nominate a family member for adherence updates. MyTherapy's one-time share code lets a clinician pull a report without an account. Hero lets caregivers join an account without their own subscription.
What to get right when you develop a medication reminder app with caregiver access:
- Consent that the patient grants and can revoke, per caregiver, per data type
- A caregiver view scoped to adherence rather than the full record
- Escalation that routes to a person after N missed doses rather than buzzing louder
- Separate consent handling for minors and for adults under a proxy
Care coordination beyond medication belongs in elderly care app development.
Design for the patient on 5 medications and a tremor
A custom medication reminder app for older adults or complex regimens rides on boring parts:
- large type that survives system scaling
- tap targets that work with a tremor
- one-tap confirmation from the notification
- voice input
- onboarding that imports medications instead of typing 8 drug names
Test with the actual population. Accessibility obligations attach through a covered entity partner, making this contractual, and healthcare app development practice has the broader patterns.
Adherence tracking is only as good as your definition of a dose taken
Tracking is where medication management app development earns its clinical claim or quietly fails to.
Decide what counts as a dose taken
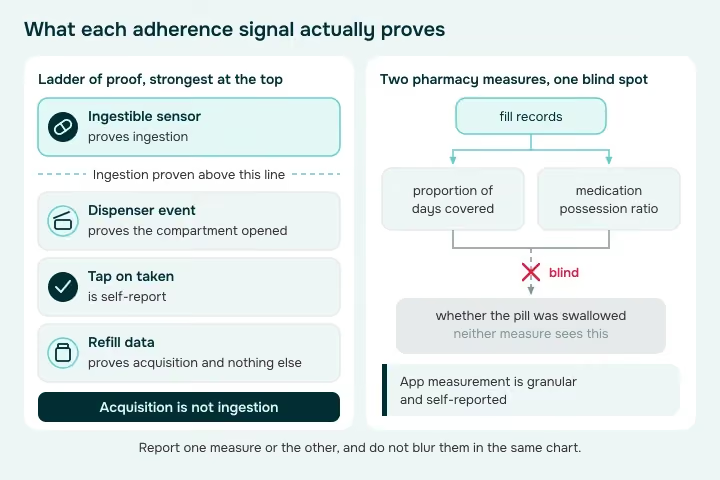
A tap on "taken" is self-report. A dispenser event proves the compartment opened. An ingestible sensor proves ingestion. Refill data proves acquisition and nothing else.
Pharmacy measurement uses proportion of days covered and medication possession ratio, both computed from fill records, both blind to whether the pill was swallowed. App measurement is granular and self-reported. Prescription management app development for a clinical audience means stating which one you're reporting and not blurring them in the same chart.
Make missed-dose handling a clinical decision
A missed antihypertensive dose and a missed immunosuppressant dose are not the same event. Let the regimen carry a criticality flag, and drive escalation from that:
- Low: log it, roll it into the weekly summary
- Medium: re-prompt once, surface it to the caregiver
- High: escalate through a second channel, and notify the care team if the pattern repeats
Give the clinician something actionable
A clinician receiving a 30-day adherence chart with no threshold does nothing with it. A flag saying this patient's PDC dropped below your threshold since the last visit is a task. Pick the threshold, defend it clinically, and send the exception rather than the data dump.
Best practices for medication adherence app development are mostly about sequencing
In medication adherence app development, sequencing is what separates a 4-month build from a 9-month one.
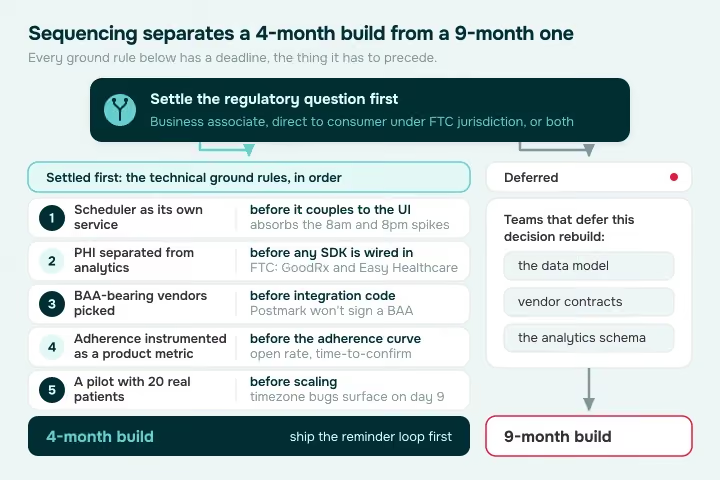
Settle the regulatory question first. Whether you're a business associate, a direct-to-consumer app under FTC jurisdiction, or both in different deployments, changes your data model and your vendor contracts. Teams that defer this decision rebuild.
Then the technical ground rules:
- Scheduler as its own service: it's what absorbs the 8am and 8pm spikes, and the part you'll swap channels inside. Coupling it to the UI is the mistake we see most.
- PHI separated from analytics from day one: the FTC actions against GoodRx and Easy Healthcare were both about data flowing to advertising platforms. That is a schema decision, made before any SDK is wired in.
- BAA-bearing vendors picked before you write integration code: Postmark, for one, states plainly that it isn't HIPAA compliant and won't sign a BAA. Teams find that out after they've built on it.
- Adherence instrumented as a product metric: notification open rate, time-to-confirm and snooze frequency tell you whether the channel is working long before the adherence curve does.
- A pilot with 20 real patients before scaling: reminder fatigue and timezone bugs surface on day 9, once people are running their own routines around it.
Ship the reminder loop first and let it earn the rest. A product that reliably reminds and escalates earns the right to add interaction checking later.
6 development steps, each with its own compliance checkpoint
Week ranges are our own planning guidance rather than published figures. The checkpoints keep the last 2 steps from becoming a quarter of rework.
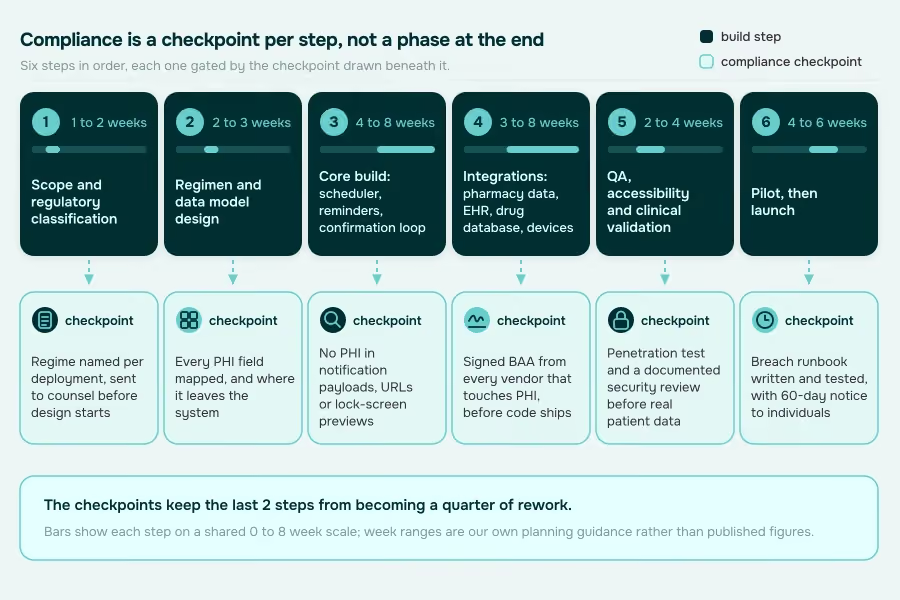
1. Scope and regulatory classification (1 to 2 weeks).
Decide who the customer is, because that sets the regime. A provider or plan contracting you makes you a business associate. Selling directly to patients puts you under the FTC Health Breach Notification Rule.
Run both and you carry two data stores and two contract sets.
Compliance checkpoint: write down which regime applies to which deployment, and get it to counsel before design starts.
2. Regimen and data model design (2 to 3 weeks).
Teams skip this step, and retrofitting a taper into a fixed-time schema means a migration. Model the awkward cases now:
- Time windows instead of timestamps
- Tapers and titration schedules
- PRN doses that need tracking without nagging
- Weekly injections with conditional missed-dose rules
- A criticality flag per medication, driving escalation
Compliance checkpoint: map every field that holds PHI, and decide which ones leave the system and where they go.
3. Core build: scheduler, reminders, confirmation loop (4 to 8 weeks).
Scheduler, notification delivery across at least 2 channels, the confirmation interaction, the adherence record. Nothing else. The rest distracts from making the loop reliable.
Compliance checkpoint: scan for PHI in notification payloads and URLs. A lock-screen preview naming a drug is a disclosure.
4. Integrations: pharmacy data, EHR, drug database, devices (3 to 8 weeks).
Order matters more than speed:
- Medication history and fill status first, since manual typing loses users at onboarding
- Drug interaction data second, once the license is signed
- Connected devices last, since each is its own protocol and support burden
Each adds a vendor to your BAA list. Pick the ones that earn it.
Compliance checkpoint: a signed BAA from every vendor that will touch PHI, before integration code ships. Confirm what subprocessors sit behind each one.
5. QA, accessibility and clinical validation (2 to 4 weeks).
A reminder app is never on the happy path. Test what breaks: daylight saving, time zone travel, a taper spanning a month boundary, 2 consecutive missed GLP-1 doses.
Test accessibility with your target population, on their devices and text sizes.
Compliance checkpoint: penetration test, and a documented security review before anything touches real patient data.
6. Pilot, then launch (4 to 6 weeks).
20 to 50 patients, instrumented, for at least 30 days. Watch 3 things:
- notification fatigue, measured as permission revocations and mutes
- confirmation rate by channel and time of day
- the gap between what people tap and what their refill data says
That gap tells you whether you built an adherence product or a tapping game.
Compliance checkpoint: breach notification runbook written and tested. Under the FTC rule, individuals get notice within 60 calendar days and the FTC is notified contemporaneously when 500 or more people are affected.
Medication reminder app development cost has 2 answers, an order of magnitude apart
The medication reminder app development cost depends on whether you build it from scratch or assemble it on a healthcare app platform.
Custom development
Those ranges track independent 2026 market guides:
- Nextolive: basic medication MVP, $40,000 to $60,000, 2 to 4 months; AI builds $150,000 to $350,000+
- Knack: basic HIPAA-compliant app at $40,000 to $80,000, with compliance engineering 20% to 30% on top
- Appinventiv: consumer reminder app, $50,000 to $120,000 over 4 to 6 months
2 line items outside the table can dominate it:
- A licensed drug interaction database runs an estimated $20,000 to $100,000+ a year, quote only, from First Databank or Wolters Kluwer. If you're building a real interaction checker, that can outrun your build budget yearly.
- Twilio's Security or Enterprise edition, required for a BAA, has no published price. The $0.013 per message never covered compliant texting.
Maintenance runs 15% to 25% of the build a year. For what HIPAA adds, from RBAC and PHI scoping to encryption and secure interface patterns, see our HIPAA compliant app development cost breakdown.
Building on Specode
Roughly $15,000 covers a year of the platform plus the penetration test that procurement will ask for.
Same caveats on the interaction database and Twilio. The Custom tier at $5,000 a month lands well above $15,000.
Who pays for adherence work
Consumer subscriptions are the obvious model and the hardest. Selling to providers or plans opens 2 reimbursement routes.
Medication therapy management is a Medicare Part D obligation under Social Security Act section 1860D-4(c)(2), rules at 42 CFR 423.153(d). Targeted beneficiaries qualify on chronic conditions, Part D drug count and projected annual spend, which CMS set at $1,276 for 2026. One constraint kills the pure-app play: CMS requires the comprehensive medication review as a real-time interactive consultation, in person or by synchronous telehealth.
Remote therapeutic monitoring fits better. CPT 98975 covers initial set-up and patient education on equipment use, and its descriptor names "therapy adherence." CPT 98980 and 98981 cover treatment management in 20-minute blocks, and both require at least one interactive communication with the patient or caregiver each month, meaning a live conversation.
Two limits: the data-collecting device must meet FDA's device definition, and RTM supply codes run by body system rather than by medication, so adherence has no supply code.
Hero sells its dispenser to providers this way, naming RTM codes and routing adherence events to a billing portal, while saying plainly it guarantees nothing about coverage.
4 medication reminder apps to learn from, and 2 that died
Every app below was checked in September 2026. That matters more than it sounds.
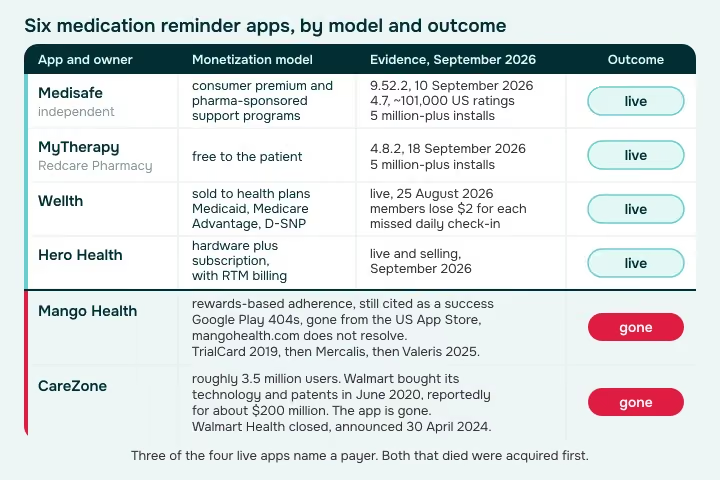
Medisafe is the category benchmark, still shipping: App Store 9.52.2 on 10 September 2026, a 4.7 rating across roughly 101,000 US ratings, and 5 million-plus Play installs. It's independent, backed by Sanofi Ventures, Pitango and Qualcomm Ventures, and it monetizes through consumer premium and pharma-sponsored support programs.
Steal: Medfriend, its caregiver mechanic. The patient picks who gets notified and what's shared, putting a person at the end of the escalation path.
MyTherapy is live (App Store 4.8.2 on 18 September 2026, 5 million-plus Play installs) and owned by Redcare Pharmacy through smartpatient GmbH. smartpatient claims over 12 million patients and keeps the app free.
Steal: the one-time share code. A patient generates a code, a clinician pulls the adherence report, no account creation on either side. Most apps put a signup wall exactly where the clinical value is.
Wellth is the one to study if you wanted Mango Health's rewards idea. Live as of 25 August 2026, it sells to Medicaid, Medicare Advantage and D-SNP plans rather than to patients. The mechanic is loss framing: members earn up to a fixed reward and lose $2 for each missed daily check-in, a photo of the medication in hand, per JMIR Mental Health (2022).
Steal: the structure. A payer pays for adherence, the patient feels a small daily loss. Points and badges have a worse track record.
Hero Health is the hardware-plus-subscription model, live and selling as of September 2026, with the RTM billing angle covered above.
Steal: caregivers join the account without their own subscription. Gating the caregiver behind a second paywall locks out whoever manages the medications.
Two cautionary tales
Mango Health, which the industry still cites as a rewards-based adherence success, is gone. Its Google Play listing 404s, it's absent from the US App Store, and mangohealth.com doesn't resolve. TrialCard acquired it in September 2019, then became Mercalis, which merged with PharmaCord in May 2025 to become Valeris, whose site doesn't mention the name.
CareZone had roughly 3.5 million users when Walmart bought its technology and patents in June 2020, reportedly for about $200 million. The app is gone, and Walmart announced on 30 April 2024 it was closing Walmart Health entirely. User counts don't protect a product that becomes a line item in someone else's strategy.
How Specode helps
Specode is an AI-powered healthcare app builder: you describe the app in plain English and it builds on a HIPAA-ready foundation. The Pro plan is $1,000 a month, including production deployment, hosting and the backend hosting BAA.
What Specode handles well. These ship as healthcare skills the AI applies directly:
- patient and caregiver roles
- intake and onboarding flows
- scheduling
- provider profiles
- MFA
Twilio SMS is a built-in skill too, which covers the escalation channel.
The HIPAA Compliance Agent scans your code across 11 categories, and 2 of them (Notifications and Messaging, and PHI Exposure in UI and URLs) are precisely the places a medication app leaks. A lock-screen preview naming a drug is a disclosure, and the agent looks for exactly that. Audit logging can be planned and implemented across confirmed PHI surfaces, with scalar-only metadata that never carries PHI values.
You own 100% of the code and can export it at any time.
The honest constraints. Specode builds responsive web apps and doesn't generate native mobile apps. For a reminder product, that matters. The route many of our clients use is a PWA with web push, inside the limits described in the patient engagement section: weaker than native push, and Home Screen install required on iPhone. SMS is the escalation path.
Pharmacy networks, EHR systems and drug databases are reachable as custom API integrations with your own credentials rather than shipped connectors. Specode doesn't provide e-prescribing, and no part of this guide's Surescripts or EPCS material describes a Specode feature.
Stripe, the default payment integration, doesn't sign a BAA and restricts prescription and pharmacy categories. A medication product that takes payment needs a BAA-signing processor instead.
The Compliance Agent is a scanner, and its documentation says plainly that it doesn't guarantee full HIPAA compliance on its own. It reads your code. Your policies and your risk analysis stay on you, and so does your training.
What that adds up to: if your product is patient-side adherence, reminders, caregiver access and tracking, most of the build is workflow and UI over a compliant foundation, and that's the part Specode compresses. If it's prescribing or dispensing, the integration work dominates.
We haven't shipped a public medication adherence case study yet, so there's no number to quote here. The apps in the previous section are better teachers than a vendor claim anyway. If you're scoping medication reminder app development and want to work out which route fits, talk to us.
Frequently asked questions
Custom development runs $40,000 to $80,000 for an MVP and $150,000 to $350,000+ for a clinical-grade build. Building on Specode costs about $15,000 for year one.
2 to 4 months for an MVP, 4 to 7 months with adherence analytics and an EHR feed, 8 to 12 months for a clinical-grade build with interaction checking.
Only if a provider or health plan hired you, which makes you a business associate. A direct-to-consumer app falls under the FTC Health Breach Notification Rule instead.
Through Surescripts, using NCPDP SCRIPT messages. A reminder app typically needs medication history and fill status rather than full prescribing capability.
Yes, modestly. Pooled trials show an odds ratio of 2.120 (95% CI 1.635 to 2.747) for self-reported adherence. Escalation to a caregiver beats louder alerts.
Timing optimization from observed behavior, and risk prediction for non-adherence. Interaction checking is a licensed drug database lookup, priced per contract.
It keeps the medication list accurate without patient data entry, and supplies allergy and problem data. Read-only access covers most reminder products.
Only if a clinician acts on what you surface. RTM billing requires an interactive conversation each month, which makes messaging a reimbursement enabler.
Role-based access, encryption in transit and at rest, audit logging, and PHI kept out of notification payloads and URLs. Separate analytics from PHI.



