
Healthcare Wearable App Development: RPM, EHR Integration & Compliance

Updated September 2026
Someone just pitched you a wearable-driven RPM program. Or your CMO wants a feature that works "like the Apple Watch," and you need to know by Friday what's buildable and what it costs.
Most healthcare wearable app development happens behind the screen on the wrist. Which data path you pick. Which side of FDA's wellness line you land on. Whether a clinician ever sees the reading inside the EHR they already use.
2026 moved two of those, and the money. FDA rewrote its general wellness guidance in January, and Google supports its old Fit APIs only until the end of this year. CMS started paying for monitoring months with as few as 2 days of data.
We've built healthcare apps for over a decade, and we've watched teams pour the budget into the wrist and discover the clinician side last. Plan it the other way around.
How do you build a healthcare wearable app in 2026?
Pick the clinical job and the FDA lane first, then the data path (a device's Bluetooth link, Apple Health or Health Connect, a device maker's cloud, or a middleware API), then build the alert loop and the EHR write-back on a HIPAA-ready backend. For custom healthcare wearable app development, published industry estimates put a connected RPM app at $100,000 to $350,000 and 6 to 12 months; FDA-regulated wearable software runs $500,000 to $1.5 million or more.
Key Takeaways:
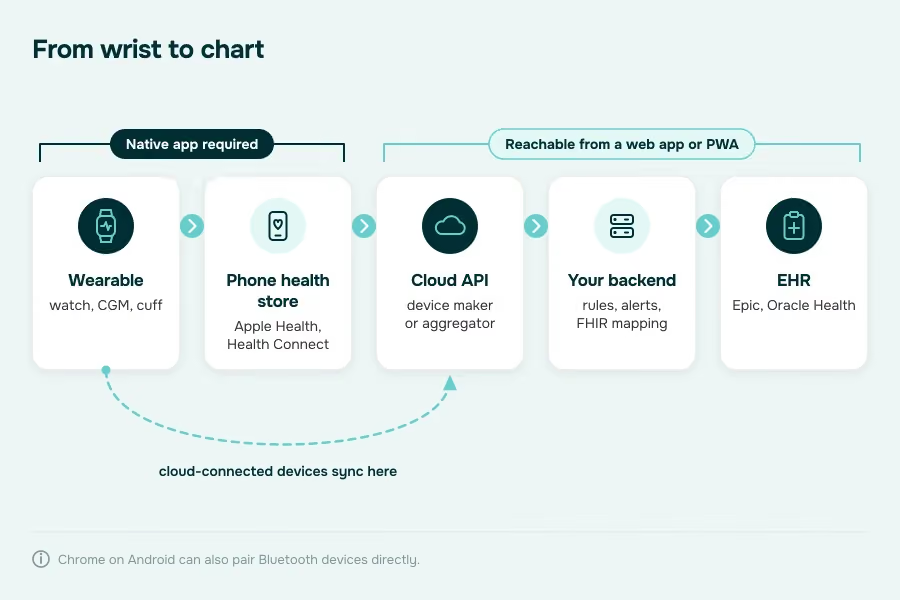
- Your data path decides whether you need native code. Cloud-connected devices reach any web app over OAuth. Apple Health and Health Connect data need a native phone app, because neither offers a web API.
- FDA's January 2026 wellness guidance widened the no-clearance lane, with conditions. Under the nonbinding guidance, FDA may treat a non-invasive wearable that estimates values like blood pressure as a wellness product if its outputs are solely for wellness use, the values are validated, and the app never names a disease, calls a reading abnormal, prompts clinical action, or claims medical-grade accuracy.
- A reading that never reaches the EHR rarely changes care. Map vitals to FHIR R4 Observations and land them where clinicians already work, in Epic or Oracle Health.
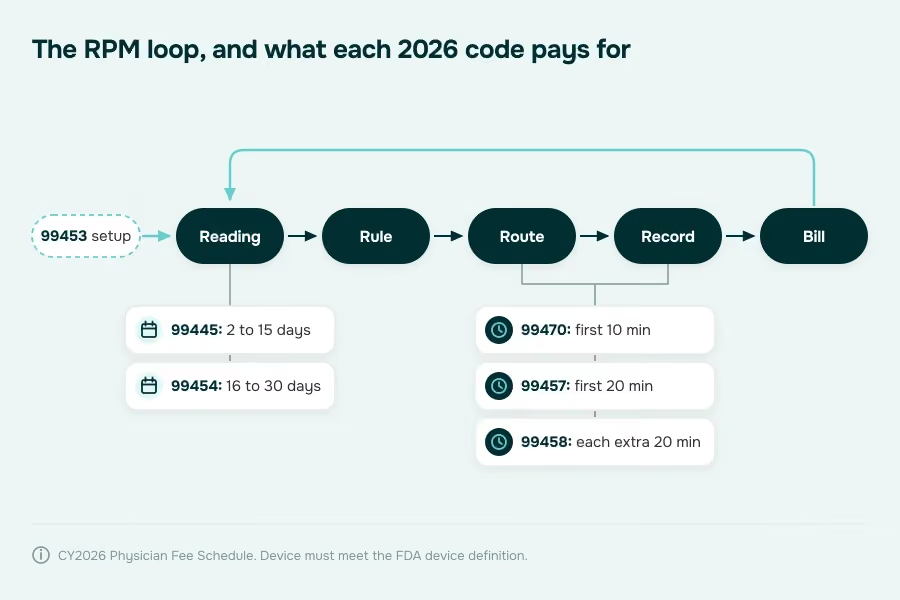
- CMS now pays for shorter monitoring months. From 2026, CPT 99445 covers 2 to 15 days of device data at the same national rate as the 16-day code, which changes the RPM math for patients who don't wear a device every day.

Healthcare wearables matter once a clinician can act on the data
Rock Health's 2025 Consumer Adoption Survey (published June 2026) found that 46% of U.S. adults own a wearable, and 59% of those owners have already discussed their wearable data with a healthcare provider, 30% of them regularly. Pew put smartwatch ownership at 37% of U.S. adults in February 2026.
With the market in place, healthcare wearable app development comes down to the data each device produces, and whether anyone downstream can act on it:
Two things in that table shape your build. First, most of this is biometric data from devices consumers bought for themselves, which puts health monitoring and fitness tracking in the same pipe as clinical care.
Second, only some of these devices are FDA-cleared for the claims your clinical program wants to make. That line decides your regulatory lane.
If your product sits on the consumer end (steps, workouts, coaching), our guide to fitness app development covers that build.
Spend this year's budget on the watch, the patch, the CGM and the cuff. Smart clothing and smart glasses (sensor-woven shirts, augmented reality overlays for clinicians) are technology we'd file under the future.
RPM and CGM app development: where wearables pay for themselves
2 application types have the clearest business case: remote patient monitoring and continuous glucose monitoring.
According to a 2025 HHS Office of Inspector General report, nearly 1 million Medicare enrollees received remote patient monitoring in 2024, up 27% in a year, and Medicare RPM payments reached $536 million. The same report flagged billing patterns for further scrutiny, so build the audit trail in from day one.
RPM app development is a care loop with a billing clock
RPM app development is mostly plumbing around one loop. A device reading lands, gets normalized, hits a threshold rule, raises an alert to the right person, and ends as a documented interaction someone can bill for. Care loops that skip the last step produce dashboards clinicians stop opening.
The billing side changed in 2026. Under CMS's CY2026 Physician Fee Schedule, these are the remote monitoring codes you'll design around (national non-facility rates, computed from CMS's 2026 RVU file):
CMS's CY2027 proposed rule would revalue the device-supply codes, so treat these as 2026 numbers.
2 product consequences. The device has to meet the FDA definition of a medical device and digitally upload data, so check where a consumer wellness band stands before you design around these codes. And your vitals data model needs day counts and minute tracking baked in, because that's what the codes pay on.
The clinical evidence is real, and narrower than vendor decks suggest. A 2025 meta-analysis of 41 heart-failure trials in the European Journal of Heart Failure found that remote monitoring, mostly weight and blood-pressure telemonitoring, lowered the odds of a first heart-failure hospitalization by about 22%.
Programs that included ECG monitoring did no better than those without it, and all-cause hospitalizations didn't fall significantly.
For condition-specific builds, see our guides to blood pressure monitoring app development and chronic care management app development.
CGM app development runs on delayed data
The FDA cleared the first over-the-counter CGM, Dexcom's Stelo, in March 2024, and Abbott's Lingo and Libre Rio followed in June 2024. The same Rock Health survey found 47% of U.S. CGM owners report no diabetes diagnosis. Continuous glucose monitoring now has a consumer market next to the clinical one.
In a Veterans Affairs cohort published in Diabetes Care in 2023, starting a CGM was linked to an 11% lower risk of all-cause hospitalization in insulin-treated type 2 diabetes and a 25% lower risk in type 1. It's observational, so treat it as an association worth testing in your own program.
The trap in CGM app development is latency. If your product promise depends on real-time data, check the path first:
- Dexcom's v3 API delivers readings with a 1-hour delay in the US
- G7 data reaches Apple Health 3 hours late
- Abbott routes Libre data to clinicians through LibreView, including a direct Epic link announced in April 2025
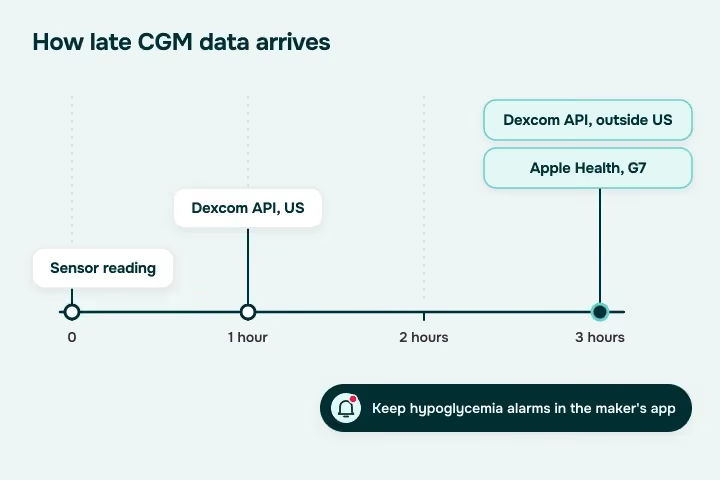
Time-in-range reports and daily summaries work fine on that clock. Hypoglycemia alarms belong to the manufacturer's own app. Our diabetes management app development guide goes deeper on program design.
4 more use cases built on the same care loop
- Cardiac: patches and ECG wearables for post-discharge and arrhythmia monitoring, where alert routing is the part to get right.
- Mental health: passive sleep and HRV data feeding behavioral care. Our guide on How to Create a Mental Health App covers the clinical side.
- Women's health: cycle and temperature tracking tied to a care team and secure messaging.
- Post-op recovery: activity and vitals trends for the first weeks home, with escalation to the surgical team.
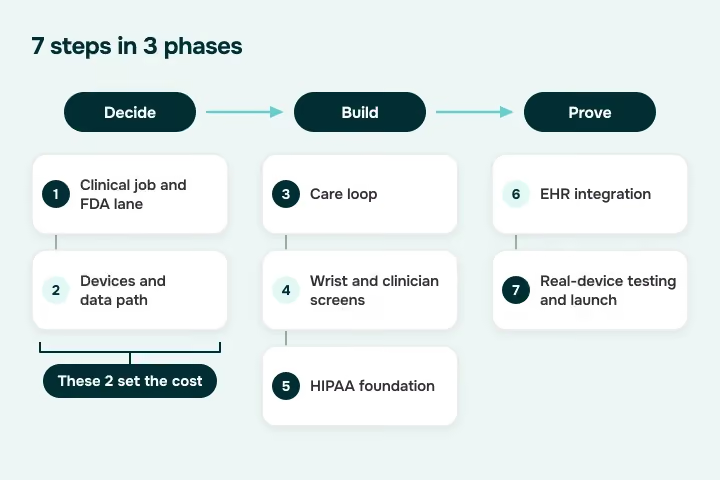
How to build a healthcare wearable app in 7 steps
This is the order we'd run a wearable app development for healthcare project in, whether it's a fresh product or a rebuild. The first 2 steps decide the cost of everything after them.
1. Pick the clinical job and the regulatory lane
Write one sentence: what the app does when a reading is bad. "Shows a trend" and "pages a nurse" are different products, with different FDA exposure and budgets. Decide here whether you're building a wellness product or a medical device, because creating the evidence for a device claim later means rebuilding.
2. Choose devices and a data path
Start from the devices your patients already own or your program will ship. Then pick how the data travels:
- a device maker's cloud API or a middleware platform, when you need many devices fast
- a native companion app, when the data lives in Apple Health or Health Connect
3. Design the care loop before the screens
The loop has 4 parts: a reading, a rule, a route, a record. Name who gets the alert, what escalates after how long, and where the interaction is documented. In our experience, wearable application development that stalls in pilot usually stalls here.

4. Design for a glanceable wrist and a busy clinician
Design the user experience for 2 screens at once:
- Glanceable data: one number and one trend per screen.
- Few inputs: gestures and voice commands over typing on a watch.
- Context-aware alerts: timed to the patient's day and delivered one at a time.
- Clinician views: the user interface for the care team matters as much as the watch face, and it lives on a laptop.
5. Build the HIPAA foundation
Whether HIPAA applies depends on who runs the app. If a provider or health plan runs it, whether that's you or your customer, build in:
- encryption
- access control
- audit logs
- signed BAAs with every vendor that touches the data
Put that in before the first real patient, since retrofitting it means rewriting your data layer.
6. Integrate with the EHR
Map readings to FHIR and decide what gets written back to the chart. Then get the health system's integration team on the calendar early: their queue is usually the longest lead time in the project.
7. Test on real devices, then launch
Run quality assurance and testing on the actual hardware, because that's where developing apps for medical wearables breaks:
- a full wear day of battery drain, with sync running
- offline gaps and late-arriving data
- pairing and re-pairing after OS updates
If the product needs FDA clearance, it's almost always a "cyber device," so the submission also needs a cybersecurity plan and a software bill of materials. Launch to a small cohort first and focus on alert volume in the first month.

Wearable EHR integration starts with the data path
Anyone who's done custom healthcare software development knows the EHR is where timelines slip. Wearable EHR integration adds a second problem in front of it: getting the data off the device at all. For app development for medical wearable devices, pick the path first, because it decides whether you need native code:
If your spec still says Apple HealthKit and Google Fit, update the Android half: build on Health Connect, and point cloud or server integrations at the new Google Health API.
FHIR and HL7 are the easy part now
Map each reading to a FHIR R4 Observation using the US Core vital-signs profiles. R4 is what US EHRs serve in production, HL7 has published R5 (2023), and R6 is still in ballot. Certified EHRs moved to USCDI v3 on January 1, 2026.
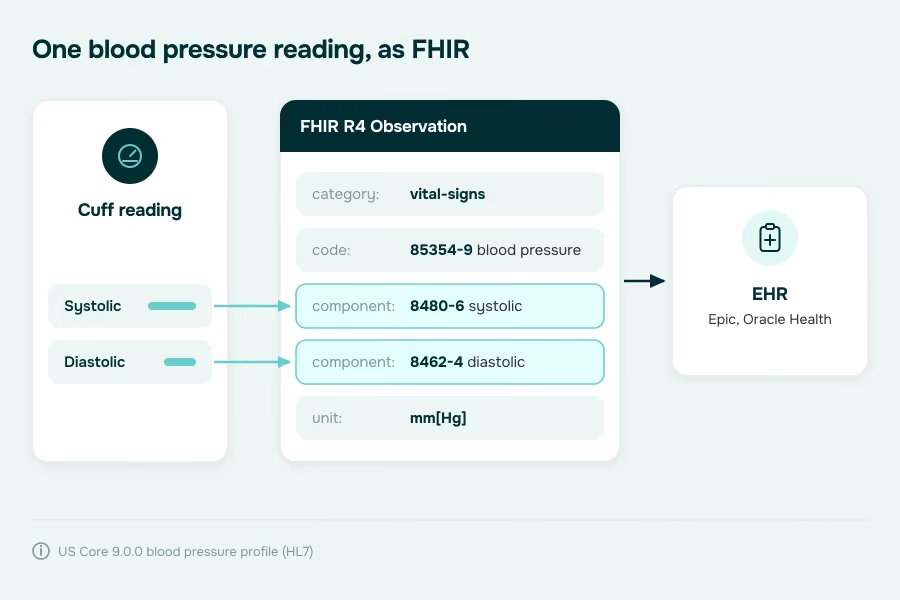
For remote patient monitoring, Epic integration means patient-sourced readings land in patient-entered flowsheets that care teams can see. Cerner integration now means Oracle Health: Oracle closed the Cerner deal in June 2022, and its Millennium platform exposes FHIR R4 APIs. The former Allscripts EHRs are split between Veradigm and Altera Digital Health, so ask which one your customer runs.
Validic middleware (with managed programs that write to Epic and Oracle Health) is often the fastest route when you need dozens of devices in year one. For the wider build, see our medical app development guides; our EHR integration guide covers the EHR side in depth.
Integration practices that survive a pilot
- Start with one high-value use case: remote cardiac rehab or hypertension, with an outcome the clinic already tracks.
- Land data where clinicians work: inside the EHR workflow, so the care team never needs a second login.
- Close the consent loop: tell patients how their readings become part of the record, and get explicit consent for secondary use.
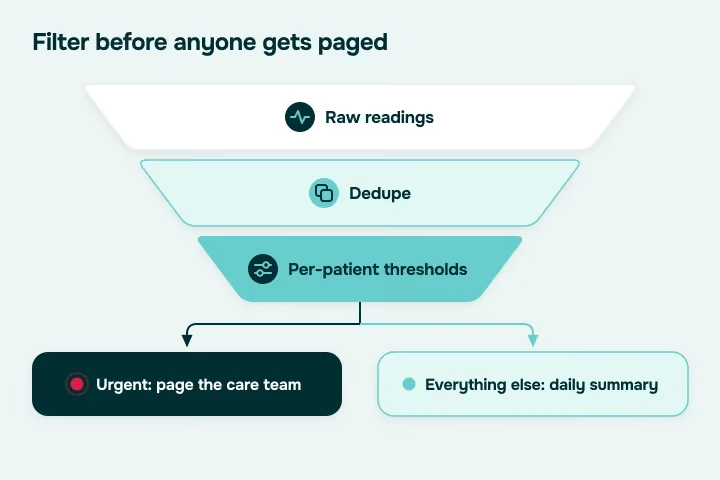
- Filter before the EHR: dedupe and threshold readings so the software sends events a clinician can act on.
- Set the write rules early: decide how your app will interact with the chart on every write.
Medical wearable rules turn on who runs the app and what it claims
Medical wearable app development answers 2 questions before any code ships: who runs the app, and what it claims. HIPAA compliance follows the first. FDA follows the second.
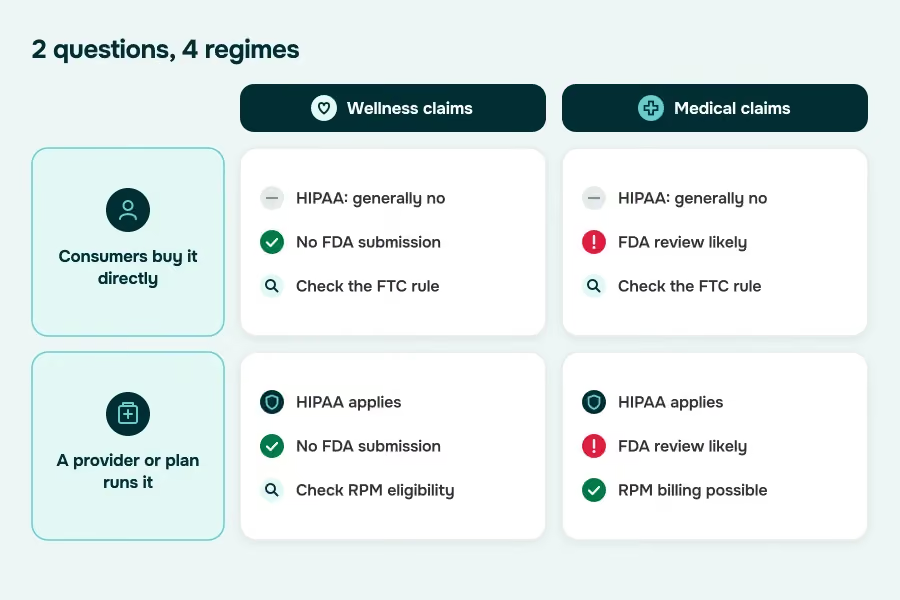
Who runs the app decides between HIPAA and the FTC
HIPAA applies in 2 cases:
- You're a provider or health plan: the readings your program collects are patient data, and every vendor that touches them, from hosting to the device-data API, signs a BAA.
- You build the program for one: you're their business associate for that work (HHS OCR's 2016 app scenarios), with a BAA of your own.
If you sell straight to consumers, you're generally outside HIPAA, even when a doctor recommends the app or a patient shares readings with one. That's where the FTC's Health Breach Notification Rule comes in. Amendments effective July 29, 2024 confirm it reaches many health apps that act as personal health records, such as an app that syncs with a wearable, and that sharing data without authorization counts as a breach.
FDA's wellness lane got wider in 2026
Under FDA's nonbinding general wellness guidance of January 6, 2026, FDA may treat a non-invasive wearable that estimates values such as blood pressure or SpO2 as a low-risk wellness product if:
- its outputs are solely for wellness use
- any clinical-style values are validated
- it never names a disease or calls a reading abnormal
- it never prompts specific clinical action or claims medical-grade accuracy
The FDA Class I/II question mostly resolves one way: most regulated wearable software lands in Class II. And a connected wearable that needs clearance is almost always a "cyber device" under section 524B, which since March 2023 requires a cybersecurity plan and a software bill of materials in the submission.
One link between FDA and CMS gets missed: RPM billing requires an FDA-defined device. Before you settle on a pure wellness positioning, check whether your device still qualifies for RPM billing.
Your tech stack needs native code on the wrist
The stack question for wearable app development for healthcare comes down to one fact: React Native and Flutter work for the phone app, but neither officially targets watchOS or Wear OS. If there's a watch app, it's native.
Cross-platform for the phone, native for the wrist. That split keeps healthcare wearables app development affordable without fighting the tech on the smallest screen.
Machine learning belongs on the backend, where it runs anomaly detection across trends. Generative AI can summarize a week of biometrics into a paragraph a clinician can scan, as long as a person reviews it before it becomes a clinical message.
On the device itself, artificial intelligence is still mostly the manufacturer's job. Skip virtual reality unless rehab is the product.

Wearable app challenges end up in the clinical record
In healthcare wearable app development, a device problem becomes a clinical problem once a clinician depends on the data. A dead battery mid-monitoring is a gap in the record.
Battery life comes down to sync schedules
Sync schedules are the battery lever your project actually controls, whatever power electronics the device ships with. So batch uploads and match sampling to the clinical question; that sync logic decides what a patient's watch looks like at 6pm.
Research helps at the margins: a 2025 Scientific Reports study found that SmartAPM, a deep reinforcement learning power manager, extended wearable battery life by 36% over traditional methods in simulation. Treat it as a simulation result until someone publishes a field case study.
More OS versions and screen shapes mean more testing
Plan for more than one watchOS or Wear OS version and more than one screen shape. Test on the smallest screen you support and the oldest OS version you promised, based on what your patient population actually wears.
Sync has to survive offline gaps
Offline gaps are normal. Store readings locally, timestamp them at capture, and make sure late data never fires a stale alert. Remote therapy products feel latency first; our guide on how to build a CBT tool app covers one of them.
Tune alerts per patient, and plan for WCAG 2.1 AA
Noise kills RPM programs. Set thresholds per patient and bundle non-urgent events into a daily summary.
Accessibility is now a buying requirement too. In May 2024, HHS updated its Section 504 rule so providers receiving HHS funding must make patient-facing websites and mobile apps meet WCAG 2.1 AA. After a May 2026 extension, the deadlines are:
- May 11, 2027, for providers with 15 or more employees
- May 10, 2028, for smaller ones
If your business sells to health systems, expect that question in procurement.
Healthcare wearable app development cost depends on the FDA lane
The biggest single swing in healthcare wearable app development cost is whether FDA reviews your software. Published 2025 and 2026 industry estimates for custom development land here:
The top tier is priced on enterprise-scale platforms that carry FDA clearance; a narrower regulated product can cost less.
Line items that move a quote, from the same estimates: EHR integration runs $20,000 to $40,000 one-way and roughly double for two-way sync, and HIPAA compliance work adds $15,000 to $30,000. Depending on the device mix, per-device integrations add up fast.
Any development company quoting well below these ranges should say what it left out. For what HIPAA adds line by line, see our HIPAA-compliant app development cost breakdown.

FDA's own fees sit on top. For fiscal 2027 (from October 1, 2026), a 510(k) costs $28,653 ($7,163 for a qualifying small business) and a De Novo request $191,020 ($47,755). FDA aims to decide 95% of 510(k)s within 90 FDA review days, against a shared average of 112 calendar days.
Building on Specode: about $15,000 for the first year
That covers the web and cloud side of a connected RPM product: patient web app, clinician dashboard, alert workflows and EHR connections. Our own estimates put a custom patient portal at 2 to 4 weeks and a full healthcare platform at 4 to 8 weeks. The Custom plan, with our engineers coding alongside you, starts at $5,000 a month.

How Specode helps
Specode is an AI healthcare app builder: you describe the app in plain English and it builds on a HIPAA-ready foundation.
What Specode covers on a wearable product:
- responsive web apps the patient can install as a PWA on their phone
- your data model and escalation logic: the thresholds, and who gets paged when a reading crosses one
- device data through Junction (covered in our docs) or any other fitting third-party API you ask Specode's AI to integrate, with your own keys
- EHR integrations such as Epic and Oracle Health (Cerner), reached the same way
Cloud-connected devices like Fitbit, Garmin, Oura, Withings or a Dexcom CGM don't need a native app for this.
The honest limit: Specode doesn't build native watch or phone apps, and a PWA can't read Apple Health or Health Connect. If your data lives there, you'll need a native companion, built separately against the same backend.
On compliance:
- the hosting BAA is included on Pro
- our team reviews every app for security and HIPAA before it goes live (1 to 2 business days)
- a built-in HIPAA Compliance Agent scans your code and flags which third-party services still need a signed BAA
The agent doesn't guarantee compliance on its own, and device-data vendors may need their own BAAs.
You own the code and can export it any time. If you're scoping healthcare wearable app development and want to see which parts compress, talk to us.
Frequently asked questions
Industry estimates: $25,000 to $90,000 for an MVP, $100,000 to $350,000 for a connected RPM app. On Specode, the web side runs about $15,000 in year one, plus device fees and any native app.
Watch and phone apps buffer readings locally and sync when the connection returns. Timestamp every reading at capture so late data never triggers a stale alert.
HIPAA when a provider or plan runs the app or you handle its patient data, the FTC Health Breach Notification Rule for many consumer health apps, FDA Class I/II for device claims, and GDPR for EU users.
Intended use. A fitness tracker makes wellness claims. A medical wearable diagnoses, monitors or manages a condition and usually needs FDA clearance, most often as a Class II device.
Pull readings through a device API or middleware into the visit record so the clinician sees trends during the call. Specode apps can add this through Junction or another API.
It summarizes biometric trends and drafts coaching messages for a person to review. Promise real-time data only where the source is live; CGM feeds reach third parties late.
Glanceable data, one action per screen, gestures and voice commands over typing, and alerts timed to the patient's day. Test on the smallest watch you support.
Industry estimates put a custom MVP at 3 to 5 months, an RPM app at 6 to 12 and FDA-regulated software at 12 to 24. Specode estimates 4 to 8 weeks for the web side.
Often not, if it stays a wellness product under FDA's nonbinding 2026 guidance: validated values, no disease claims, no clinical-action prompts. Diagnosing or monitoring a disease usually means a 510(k) or De Novo.



