
How to Create a Mental Health App in 2026

Updated October 2026
Here's how to create a mental health app: choose one care journey and define a working crisis path. Mental health app development then moves through clinical and regulatory scoping, prototype testing with real users, building V1, integration and a security review before real patient data goes in.
Development firms' 2026 quotes put a focused MVP at $40,000 to $80,000 over 3 to 5 months, and a clinical-grade platform with EHR integration at $150,000 to $400,000 or more over 8 to 14 months.
Most people asking how to create a mental health app start with the wrong question. They scope a feature list (a mood tracker, a booking screen, a chat window) and assume the parts add up to something people open twice.
A user may open the app when they're exhausted or halfway through a bad night. Make care easier to follow in that moment.
That's why mental health app development is mostly about what happens off the patient screen: the therapist's side, the EHR your clinical data has to reach, billing and scheduling, and a safety plan that works at 2am. Get one of those wrong and the app feels broken even when the screens look fine.
Key Takeaways:
- Build the care loop before the feature list. The apps people keep connect daily check-ins to a clinician who can act on them, with a crisis path one tap away.
- Scope sets the price. Published 2026 agency quotes run from about $40,000 for a focused MVP to $400,000 or more once EHR integration, AI and insurance billing come in.
- Specode builds the regulated plumbing on a HIPAA-ready foundation. You describe the app in plain English and keep the code, and a releasable MVP takes 2 to 3 months, depending on complexity.
Mental health app features for V1
Mental health app features for V1 cover consent, mood check-ins, screening, secure communication and a working crisis path. Mental health app development should connect these into a care journey that patients and clinicians can follow.
When designing a mental health app, plan the patient experience and clinician handoff together. A mental health app project should give healthcare providers information they can act on.

| Feature | Ships in | What good looks like |
|---|---|---|
| Onboarding and consent | V1 | Plain-language consent that says what's stored and who sees it |
| Mood tracking and self-monitoring | V1 | A log that takes seconds, with charts a patient can read |
| PHQ-9 and GAD-7 check-ins | V1 | Each score explained in plain words, with a next step attached |
| Secure messaging and scheduling | V1 | Clinical context stays on the thread; booking needs no phone call |
| Crisis support and safety plan | V1, always | 988 and emergency options reachable from any screen, plus the user's own plan |
| Resource library | V1, kept small | Organized around moments like "can't sleep" or "before a session" |
| Progress sharing with providers | V1 | Sharing is a deliberate user action, never silent |
| Teletherapy video and provider portal | V1 if therapists are in the loop | The therapist sees check-ins and scores before the session |
| EHR integration | Later, unless a health system is the buyer | User-approved data lands inside the clinician's workflow |
| AI personalization and peer community | Later | AI suggestions a clinician can review; moderation built in |
The PHQ-9 and GAD-7 are validated, public-domain questionnaires, so you can build them in without a license.
Two design rules sit on top of the table: navigation simple enough for someone anxious or exhausted, and a clear next step after every assessment and session. The list should feel boringly practical. That's usually a good sign.
How to develop a mental health app in 7 steps
Here's how to develop a mental health app: pick a care journey, set the clinical scope, choose a build path, test a prototype, build V1, integrate and review, then launch and measure. Steps 1 to 3 happen once; steps 4 to 7 keep repeating.
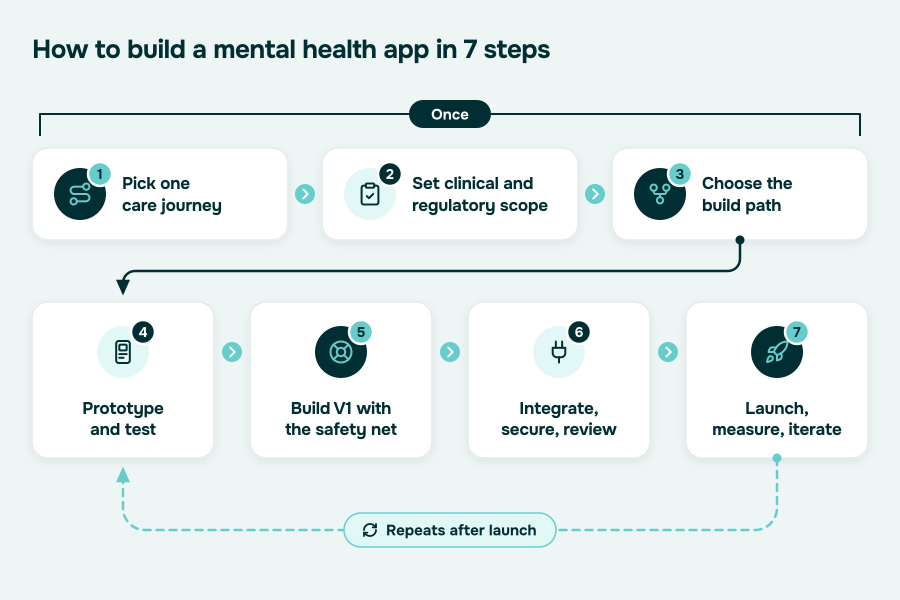
Step 1: pick one care journey
Choose one user state and one path through it, such as a first screening that ends in a booked session, or a daily check-in that a therapist reviews weekly. Then write down what V1 won't do. Most bloated mental health apps we see started by supporting every condition at once.
Step 2: set the clinical and regulatory scope
Decide what the app claims, because claims decide the rules:
- Wellness or treatment: stress and sleep claims are wellness under FDA's guidance; treating a disorder makes the app a medical device.
- HIPAA or FTC: handling PHI on behalf of a covered provider or health plan can make you a business associate, and a consumer app outside HIPAA still answers to the FTC.
- Clinical ownership: name the clinician who signs off on content, assessments and the crisis protocol before design starts.
Step 3: choose the build path
Decide how to build a mental health app with the team and budget you have. Compare the options in the mental health app developers and services section below.
Step 4: prototype and test with real users
User-centered design puts people with mental health concerns first. In practice, you build a clickable prototype, put it in front of real users, and watch where they hesitate, skip, misread or quit.
The best findings hide in the awkward pauses, and survey answers rarely surface them. Fix the flow before you polish a single screen.
Step 5: build V1 with the safety net in it
Build the features marked V1 in the table, plus the parts users never see:
- consent records and an audit trail
- role-based access for clinicians and admins
- the crisis path and safety plan, tested as hard as a payment flow
- the platform call: native iOS and Android when you depend on push, wearables or offline use; a responsive web app is often enough for V1
Test the crisis path with a clinician in the room before anyone relies on it during a crisis.
Step 6: integrate, secure and review
Connect the EHR, payments and messaging vendors, and sign a BAA with each vendor acting as a business associate. Start with read access to the EHR, and plan write-back as a separate milestone. Then run a security review and a penetration test before real patient data goes in.
Step 7: launch small, measure, iterate
Launch to a pilot group and watch the outcome metrics from week one:
- PHQ-9 and GAD-7 score changes
- completed referrals
- engaged retention
- how often the crisis path gets used
Ship fixes on a fixed cadence.
Mental health app developers and services
Choose mental health app developers according to the work you want to keep in-house. Compare mental health app development services by delivery responsibilities and code ownership.
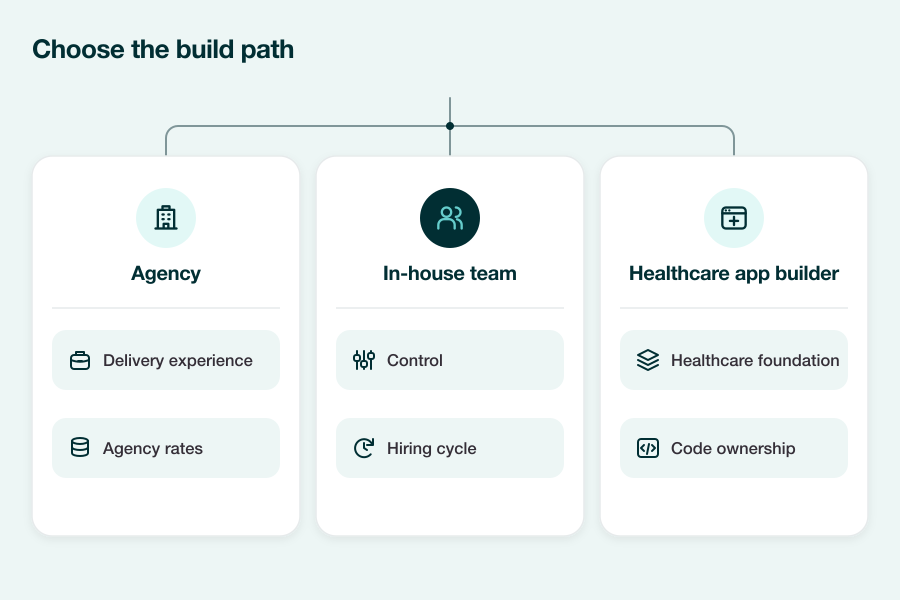
A mental health app development company brings healthcare experience, with agency rates reflected in the cost section. An in-house software development team gives you direct control, though hiring takes time.
A healthcare app builder such as Specode provides a working foundation, and the code stays yours.
Hand-coding login screens and audit logs is a poor use of a mental health team's first months.
Scope sets what it costs to build a mental health app
Mental health app development cost depends on scope far more than on any single feature. Development firms' published 2026 guides put the price to build a mental health app with an agency in these bands:
| Scope | What's in it | Cost | Timeline |
|---|---|---|---|
| Focused MVP | Mood tracking, journaling, self-guided CBT or mindfulness content, reminders, crisis resources | $40,000 to $80,000 | 3 to 5 months |
| Teletherapy or CBT platform | Adds video sessions, secure messaging, scheduling, payments, PHQ-9 and GAD-7 | $80,000 to $200,000 | 5 to 8 months |
| Clinical-grade platform | Adds EHR integration, clinician and admin portals, AI, insurance billing | $150,000 to $400,000+ | 8 to 14 months |
| Prescription digital therapeutic | Clinical-grade software built for FDA clearance | $250,000 to $800,000+ for the software (one vendor's estimate) | 9 to 18 months, before the clinical study and FDA review |
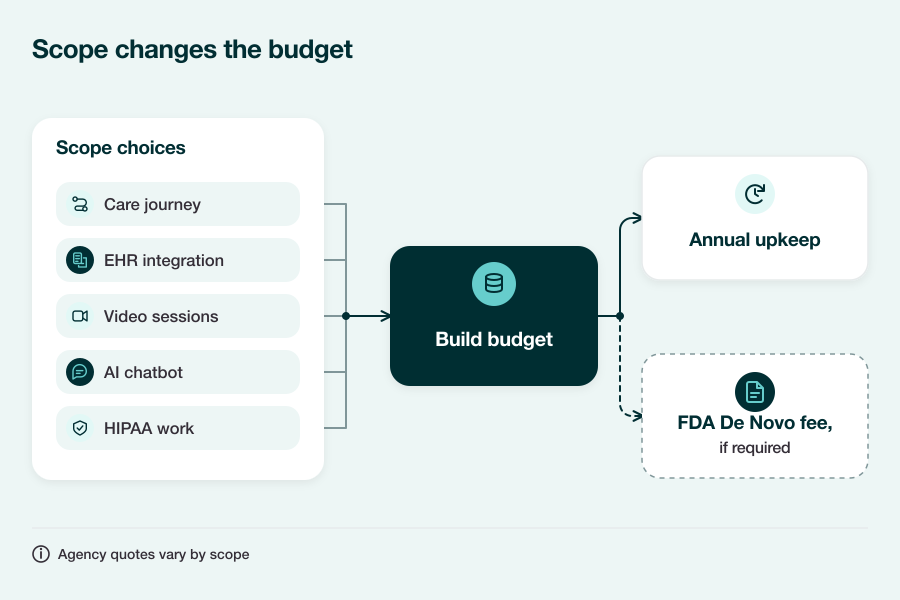
Budget for annual upkeep (15 to 25% of build cost) and any applicable regulatory fees or clinical studies. Integrations, AI and security work raise costs; keep V1 to one care journey.
On Specode, Pro is $1,000 a month; a releasable MVP takes 2 to 3 months, depending on complexity. See our HIPAA-compliant app development cost guide.
How to make a mental health app around user needs
Plan how to make a mental health app around a gap in care: support people can't reach, follow-up between therapy sessions or self-care between sessions. Mental disorders are common, and V1 should make one useful care path easier to follow.
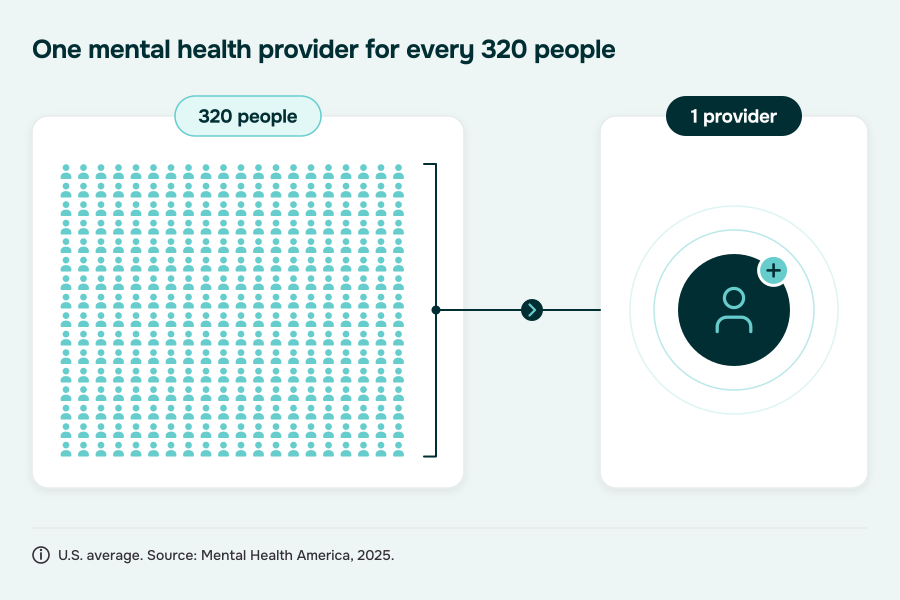
The access gap has numbers behind it
- About 1 in 5 U.S. adults (20.6%, or 54.6 million people) had a mental illness in the past year, according to SAMHSA's 2025 National Survey on Drug Use and Health.
- Half of mental health conditions in adulthood start by age 18, per the World Health Organization (2024).
- There are about 320 people for every mental health provider in the U.S. (Mental Health America, 2025).
- As of June 2026, about 157 million people, 31.7 million of them rural, lived in federally designated mental health shortage areas (HRSA).
- About 1 in 10 adolescents aged 12 to 17 (10.4%) had serious thoughts of suicide in the past year (SAMHSA, 2025).
Digital platforms can take the parts of care that don't need a room: intake, screening, mindfulness exercises and follow-up between sessions.
Social media pressure also matters when creating an app for mental health. Nearly half of U.S. teens (46%) have faced at least one form of cyberbullying (Pew Research Center, 2022), and digital mental health tools can give them a way to respond in the moment, with a path to a real person when self-guided help runs out.
Design for the user's state, whatever their age
Your app may serve a student opening it after midnight, a parent managing anxiety between sessions, an adult sliding into burnout, or a clinician reviewing their data later.
If you're working out how to make a mental health app, start with the state people are in when they open it.
Stressed users skim onboarding. Depressed users stall on long flows. Someone mid-crisis needs the next step in one tap.
Symptoms set the feature depth. Anxiety and depression, PTSD, eating disorders and bipolar disorder call for different tools:
- low-effort logging when sleep and appetite change
- short prompts when concentration drops
- escalation paths when hopelessness shows up
- mood patterns over months for bipolar disorder
Types of mental health apps differ by clinical weight
Mental health app developers need to choose between wellness tools, licensed therapy or psychiatry, and prescription digital therapeutics before adding features. That choice sets the clinical weight: the regulation, clinician time and evidence the product has to carry.
| Type | Core job | Clinical weight | Examples (September 2026) |
|---|---|---|---|
| Mood tracking and self-monitoring | Quick logs of mood, sleep and triggers, charted over time | Wellness, unless it claims to treat a condition | Daylio |
| Meditation and mindfulness modules | Guided sessions for stress, sleep and focus | Wellness | Headspace, Calm |
| CBT modules and AI coaching | Structured self-help exercises, often with a chatbot coach | Wellness until it claims to treat a disorder | Wysa (AI coach plus human care since its 2025 merger with April Health) |
| Prescription digital therapeutics | Clinician-prescribed programs cleared as medical devices | FDA clearance; Medicare codes cover qualifying devices | Rejoyn (depression), DaylightRx (anxiety) |
| Teletherapy | Video and messaging sessions with licensed therapists | Licensed care; HIPAA through providers | Talkspace, BetterHelp |
| Telepsychiatry | Psychiatric evaluation and medication management | Licensed prescribing; HIPAA | Talkiatry, Cerebral |
| Peer support | Moderated community and trained listeners | Wellness, with a heavy moderation duty | Our peer support app guide covers the build |
The clinical weight column is the one to argue about. FDA's General Wellness guidance, reissued in January 2026, treats stress, relaxation and sleep claims as wellness, while a claim to treat an anxiety disorder makes the app a medical device.
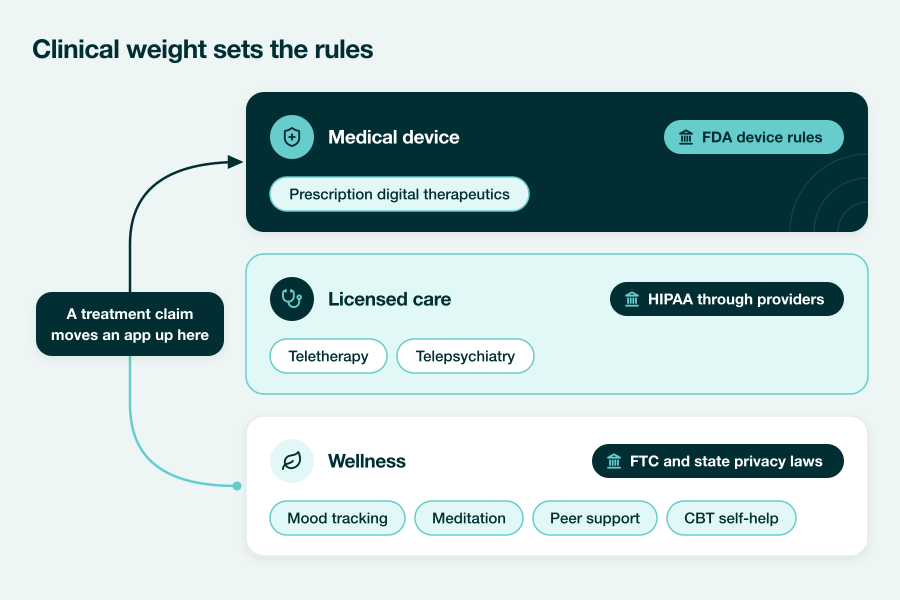
A CBT tool app sits closest to that line. So do behavioral health products, which our guide on how to build a behavioral health app covers.
Meditation app development sits furthest from it. And teletherapy apps are clinics with software attached, so read up on running a teletherapy practice before you scope telepsychiatry on top.
Monetization: decide who pays before you build
Choose who pays before creating a mental health app: consumers, employers, health plans or Medicare. The payer determines whether you need subscriptions, employer reporting or clinical billing workflows.
| Model | Who pays | Fits when | Watch out for |
|---|---|---|---|
| Consumer subscription | The user | Self-guided content with daily use | Headspace lists at $69.99 a year and Calm lists $14.99 to $79.99 purchase options (U.S. App Store, October 2026); that's your price anchor |
| Freemium | The user, eventually | You need reach first | Median Day 35 download-to-paid conversion is 2.1% for freemium versus 10.7% for hard paywalls in RevenueCat's all-category subscription-app dataset (2026 report, primarily 2025 data) |
| Employer and EAP | The employer | Stress, burnout and access-to-therapy products | Buyers want utilization and outcome reports; KFF found 48% of firms with 200 or more workers offering health benefits increased counseling resources through an EAP or third-party vendors such as Headspace or Lyra Health (2024) |
| Insurance billing | Health plans and Medicare | Licensed therapy and psychiatry | Credentialing and claims work; psychotherapy by video (CPT 90832 to 90837) and collaborative care (99492 to 99494) run on standard codes |
| Prescription digital therapeutic | Medicare, billed by the treating clinician | FDA-cleared treatment | Since 2025, Medicare codes G0552 to G0554 pay for cleared devices; 2026 added ADHD devices |
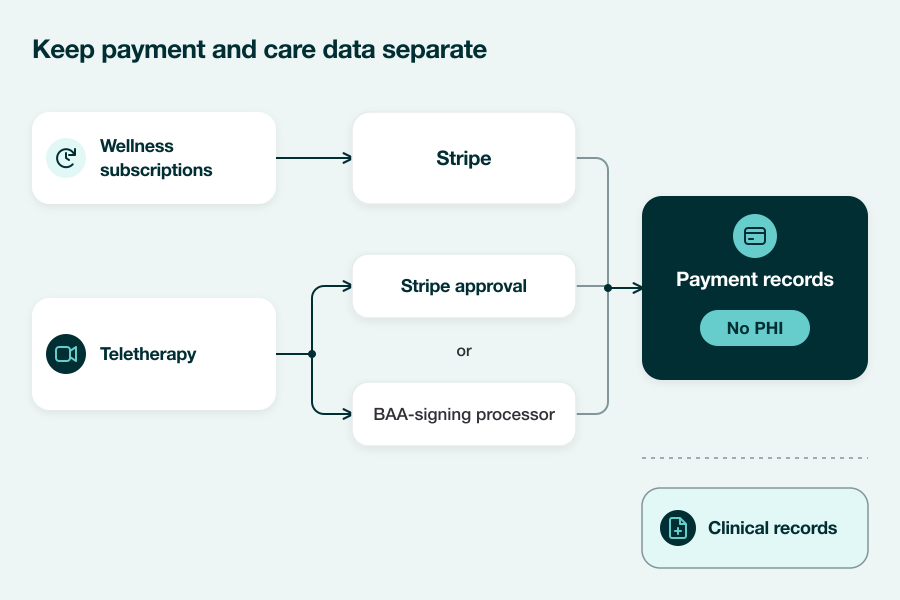
Subscription monetization is the default for consumer apps, and payments need their own check.
Stripe works for non-clinical wellness subscriptions. Teletherapy is a restricted Stripe category, so you'll need Stripe's approval or a processor that signs a BAA, and PHI never goes into a payment record. Our guide to a subscription telehealth app with HIPAA-compliant billing walks through the setup.
Tech stack and security: privacy is a product decision
In mental health application development, choose a stack your team can operate with controlled access, encrypted data, backups and monitoring. Plan clinical handoffs and integration boundaries before adding architectural complexity.
Pick an architecture your team can run
Any of AWS, Google Cloud or Azure can host it. Pick the one your team can run cleanly under healthcare rules: storage, backups, access controls, monitoring.
A microservices setup helps once messaging, scheduling and integrations need to scale on their own; before that, it's overhead with a nicer diagram. Part of how to develop a mental health app that survives launch is choosing an architecture you can change without breaking what patients rely on.
HIPAA compliance depends on who you sell to
HIPAA applies to covered entities and business associates. A mood tracker people download on their own usually sits outside it, and handling PHI on behalf of a covered provider or health plan can make you a business associate.
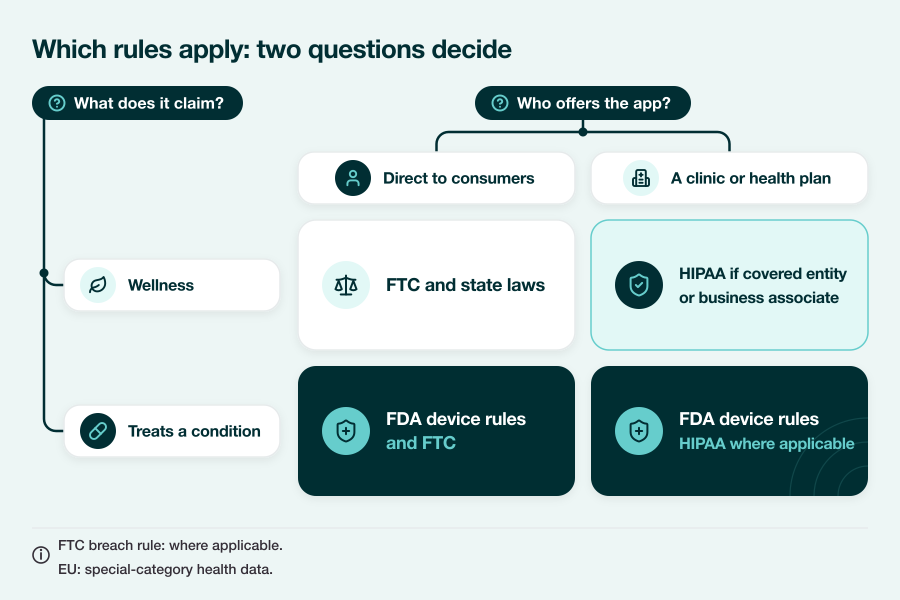
Outside HIPAA, the FTC's Health Breach Notification Rule covers certain health apps, and an unauthorized disclosure of covered health information can count as a breach. The FTC has already made the point with mental health apps:
- BetterHelp paid $7.8 million in 2023 for sharing users' questionnaire data with ad platforms.
- Cerebral agreed in 2024 to pay more than $7 million after its tracking tools sent data on nearly 3.2 million users to third parties.
State law adds a layer: Washington's My Health My Data Act generally requires consent for consumer health data, mental health included, and GDPR treats it as special category data in the EU.
The security measures follow from there. Encrypt data in transit and at rest, use MFA where the risk calls for it, write down who sees which data and why, and give users real controls to delete an account, export their data and see how it's shared.
Our healthcare app development guide covers the wider build, and the mhealth app development guide covers the mobile side.
Integration with healthcare systems is where apps become care
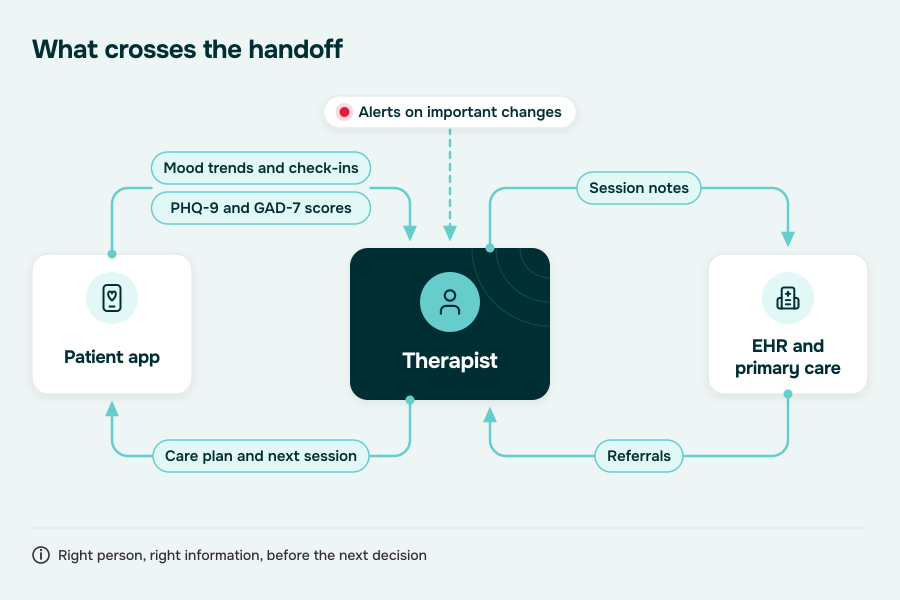
Mental health app development should connect the care team's records, scheduling, billing and referrals. Scope EHR integration around what the therapist needs to see, so staff can follow the patient without copying notes between systems.
Teletherapy needs the clinical context around it
A teletherapy session needs product work on both sides of the call: intake, consent, scheduling, notes, follow-up and escalation when a patient needs more. Telehealth app development should connect the session to the patient's record where the workflow calls for it, so the therapist sees what happened before and after the visit.
Self-improvement apps and self-help resources help between sessions, but only when the care team knows what the patient is using.
Care teams need shared workflows
A 2024 scoping review found that effective integrated mental health care models share a few elements:
- mental health services co-located in primary care
- licensed mental health clinicians on the team
- a case management approach
- depression monitoring for up to 24 months
Mental health providers can team up with primary care, but the platform has to make that practical: shared data, joint care plans, referrals that don't stall, alerts on important changes.
The test is simple. Can the right person see the right information before the next clinical decision? Our mental health EHR requirements guide covers the record side.
Engagement only counts when the safety net holds
Judge mental health app features by the care actions they support: check-ins completed, sessions booked, skills practiced and crisis paths found when needed. Daily opens alone can't tell you whether the app is helping someone follow care.
Notifications and content should protect the routine
Mental health app features like mood tracking and reminders help users see patterns, but this audience has a low tolerance for nagging. Let users choose how often they hear from you.
Use reminders for appointments and care actions the user chose. Appointment reminders follow the patterns in our doctor appointment booking app development guide.
Content works the same way. Short coping-skill lessons, audio meditations and exercises for moments when stress levels spike, such as exam weeks, all beat a bloated library.
Crisis support needs rules underneath it
Chat helps when the care team isn't available. AI chatbots can cover common questions after hours, especially when you create a mental health chatbot with clear boundaries and escalation paths.
Community helps too: a moderated forum or peer support layer gives users a safe place to share. Skip the moderation and the space turns into a liability.
A 2024 review of engagement in digital mental health interventions is a good map of what keeps people coming back.
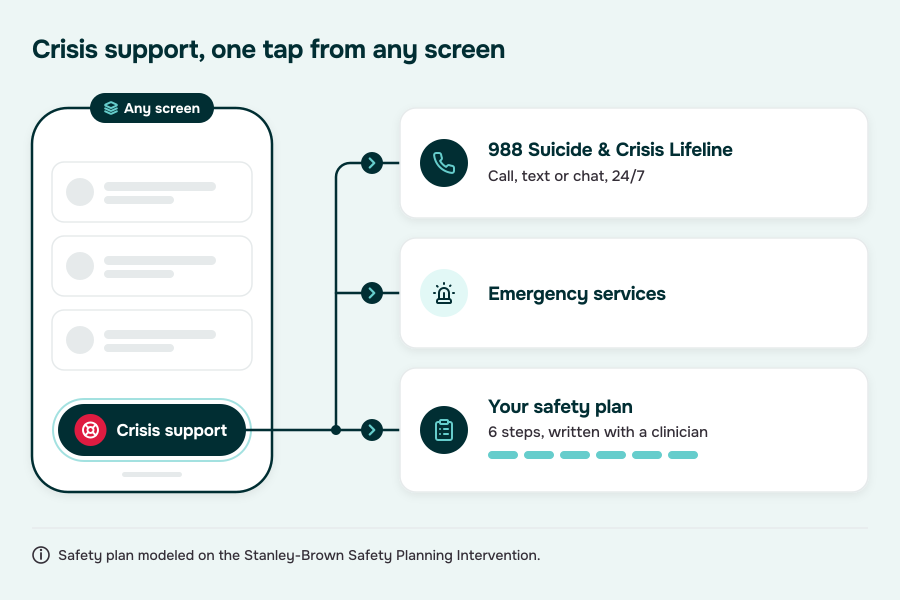
Two rules hold for every mental health app:
- One-tap crisis access: the 988 Suicide & Crisis Lifeline (call, text or chat, 24/7 since July 2022) and emergency options from every screen.
- A real safety plan: model it on the Stanley-Brown Safety Planning Intervention, which walks a person through warning signs, coping strategies, people and places for distraction, people to ask for help, professional and crisis contacts, and making the environment safer.
Outcome metrics decide what you fix next
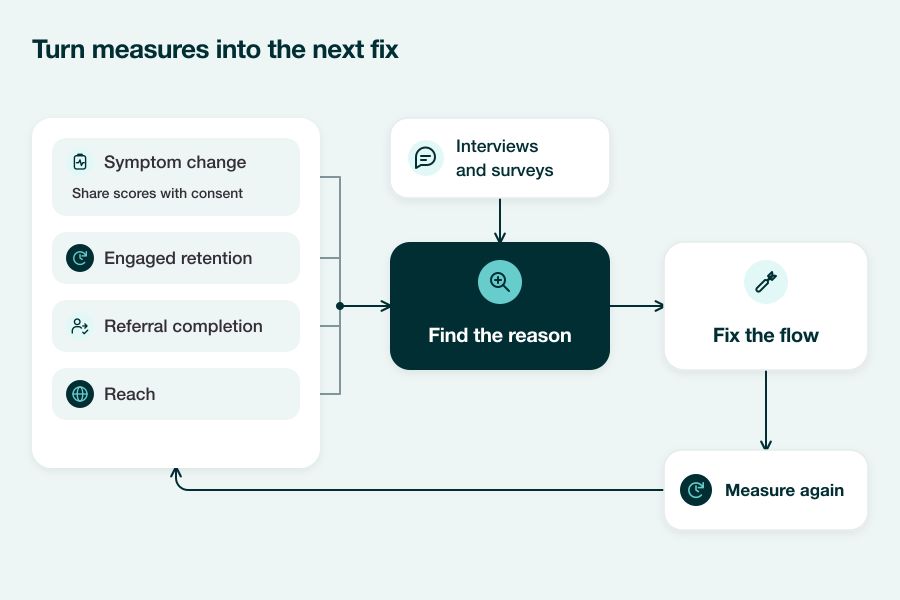
When developing a mental health application, track symptom change, engaged retention, completed referrals and reach, then use interviews to choose the next fix. Mental health app developers should define app metrics around those care decisions:
- Symptom change: PHQ-9 and GAD-7 scores over time, for users who agreed to share them
- Engaged retention: users completing check-ins and exercises each week
- Referral completion: if you refer users to outside clinicians, a booked and attended first visit
- Reach: who the product actually serves, if broader access is the goal
Pair the numbers with interviews and short surveys: satisfaction, how helpful each feature felt, and open feedback on anything that felt unclear or unsafe. Users will tell you why they abandoned a flow; the dashboard only shows that they did.
What's next: AI that knows when to hand off
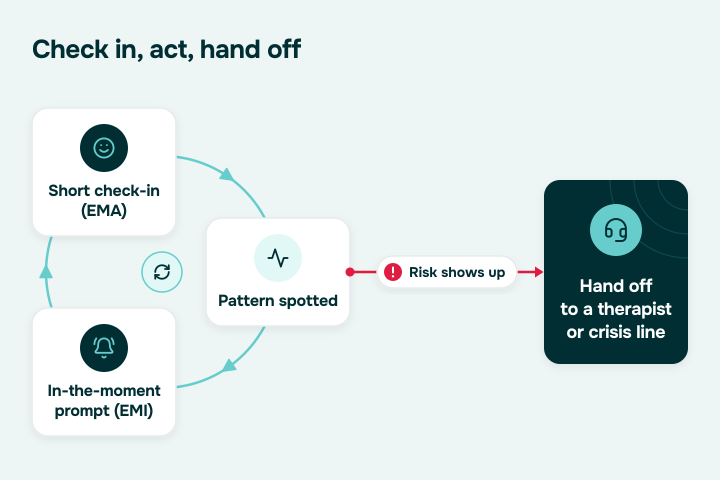
Creating a mental health application with AI starts with one bounded task, clear limits and a handoff to a therapist or crisis line. For administrative workflows, our guide to AI agents in healthcare covers tool permissions, staff review and exception handling.
Ecological momentary assessment (EMA) prompts short check-ins through the day, so the app sees mood and feelings in context. Ecological momentary intervention (EMI) acts on them in the moment, with a check-in or breathing exercises when a pattern suggests a hard evening ahead.
AI journaling could turn those check-ins into reflection prompts.
Regulators are watching: FDA's digital health advisory committee met in November 2025 on generative AI therapy tools.
Access is the other test. Many digital therapies that improve patient care still depend on who pays. Mental wellness tools are also moving outside the clinic: the share of U.S. public schools delivering mental health treatment by telehealth rose from 17% in 2021-22 to 22% in 2024-25 (KFF, 2025).
Virtual reality has evidence behind it too, with a 2026 meta-analysis of 26 trials finding VR exposure therapy reduced phobia and PTSD symptoms.
How Specode helps with mental health app development
Specode is an AI healthcare app builder for mental health app development. You describe the app in plain English, and its Maestro workflow scopes the first version with you, proposes a design, then builds on a HIPAA-ready foundation, with your approval at each handoff.
You define the data model, screens, roles and workflows yourself, and you own the code, whether it's a wellness tool or a clinical mental health application.
- Care flows from one prompt: "Onboarding → PHQ-9/GAD-7 → goal setting → session booking → teletherapy room → notes and handoffs → safety plan" becomes screens, roles and data flows you can preview.
- The care stack: EHR systems such as Epic and Cerner, insurance verification, and any service with an API. Stripe covers non-clinical subscriptions; for teletherapy, our team helps with Stripe's approval or a BAA-signing processor.
- A release path built for PHI: build and test with synthetic data. At go-live, production moves to your GitHub and Convex accounts, where you sign Convex's BAA as part of Pro. Specode keeps a deploy-only key; a third-party security assessment runs before real patient data goes in, and every release is tagged with a rollback path.
- Support and review: Pro ($1,000 a month) includes PM consultation, prompt guidance, bug fixes, a HIPAA Compliance Agent that scores and fixes your code, and a team security review before go-live. On Custom, Specode's engineers build alongside your team.
Specode builds responsive web apps that work in mobile browsers; native iOS and Android output isn't available today.
A working prototype takes about 10 minutes, and a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build, though timelines vary by complexity. The HIPAA Compliant App Builder page covers the platform itself.
For teams creating a mental health app, that's the trade: a working first version fast, code you keep, and your time spent on the care model instead of rebuilding healthcare plumbing. The video, scheduling and compliance layers behind that care model get the same treatment in our telehealth app development guide.
Frequently asked questions
It can use mood logs, check-in answers and session history to suggest the next step: a coping exercise, a journaling prompt, a booking reminder, or escalation to a clinician. It should say why, and hand off when risk shows.
HIPAA if you're a covered entity or business associate, the FTC Act and, where applicable, the Health Breach Notification Rule, state laws like Washington's My Health My Data Act, GDPR for EU users, and FDA rules if you make treatment claims.
Through EHR integration, so clinicians see user-approved data such as assessment scores, mood trends and session notes inside their own workflow. It only helps if the data is clean enough to act on.
Engagement, privacy, clinical safety and workflow fit. Most failures start with scope: trying to serve every condition and user type at once. Pick one care journey, build it well, then expand.
Development firms' 2026 quotes run $40,000 to $80,000 for a focused MVP, $80,000 to $200,000 for a teletherapy or CBT platform, and $150,000 to $400,000 or more for a clinical-grade platform. Upkeep adds 15 to 25% a year.
With an agency, 3 to 5 months for a focused MVP and 8 to 14 months for a clinical-grade platform. On Specode, a releasable MVP takes 2 to 3 months, and timelines vary by complexity. Products requiring FDA clearance add regulatory review and may need clinical studies.
Usually not. FDA generally doesn't require clearance for apps that help people manage stress or practice coping skills. A claim to treat a condition, such as an anxiety disorder, makes the app a medical device.
Consent, mood tracking, PHQ-9 and GAD-7 check-ins, secure messaging, scheduling, and a crisis path with a safety plan. Add EHR integration, AI and community features once the first care journey works.
Only with guardrails: clear limits, escalation to a human, and no treatment claims you can't back. Woebot closed its consumer app in June 2025, and its founder pointed to the cost of FDA authorization.



