
Telehealth Website Development in 2026: Features, Cost, and Compliance

Updated September 2026
To a new patient, your telehealth website is the practice until someone on staff learns their name. If the booking page stumbles on mobile or the intake form confuses them, they leave and book with another clinic.
So telehealth website development is two jobs. One is turning a first-time visitor into a booked patient in a few taps. The other is building in the rules healthcare providers answer for online.
We'd plan both together: several of those rules now carry dates, and a booking flow designed before you've mapped them gets rebuilt.
How do you build a telehealth website, and what does it cost?
Telehealth website development builds the web front door of a virtual practice, where patients find a clinician, complete intake, book, join a video visit and pay in the browser. In the US, four rule sets shape the build: HIPAA for patient data, DEA rules on prescribing controlled substances by telemedicine (the current flexibility runs through December 31, 2026), state licensure where the patient is located, and Medicare telehealth rules, extended through December 31, 2027. Built from scratch, a telehealth website costs $40,000 to $80,000 over 3 to 5 months for an MVP and $150,000 to $300,000 or more over 9 to 12+ months for a full-featured build, while on Specode, a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build.
Key takeaways
- Budget by tier: From scratch, an MVP runs $40,000 to $80,000 over 3 to 5 months and a full-featured build $150,000 to $300,000 or more over 9 to 12+ months, plus 15 to 25% of the build a year to maintain.
- Put the rules in the flow: Clinicians need a license where the patient is, so intake captures the patient's location. Controlled-substance visits go to live video under DEA's telemedicine flexibility, which runs through December 31, 2026. Medicare's telehealth flexibilities run through December 31, 2027, so set up Medicare booking rules you can change without a rebuild.
- Build on a HIPAA-ready foundation and keep the code: Specode builds your telehealth website by chat as a responsive web app. On Specode, a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build. You own 100% of the code.
What is a telehealth website?
A telehealth website is where a patient goes to get care online: finding a clinician, booking a visit, joining the video call and checking records afterward. User experience sets how many patients make it from the first click to the video call.
Pages have to respond to any screen size and work for patients with disabilities. Every form that collects health data needs protection from the first field.
Patients never see the scheduling rules, the video vendor, the EHR connection or the payment processor.
When one of them breaks, patients blame your website.
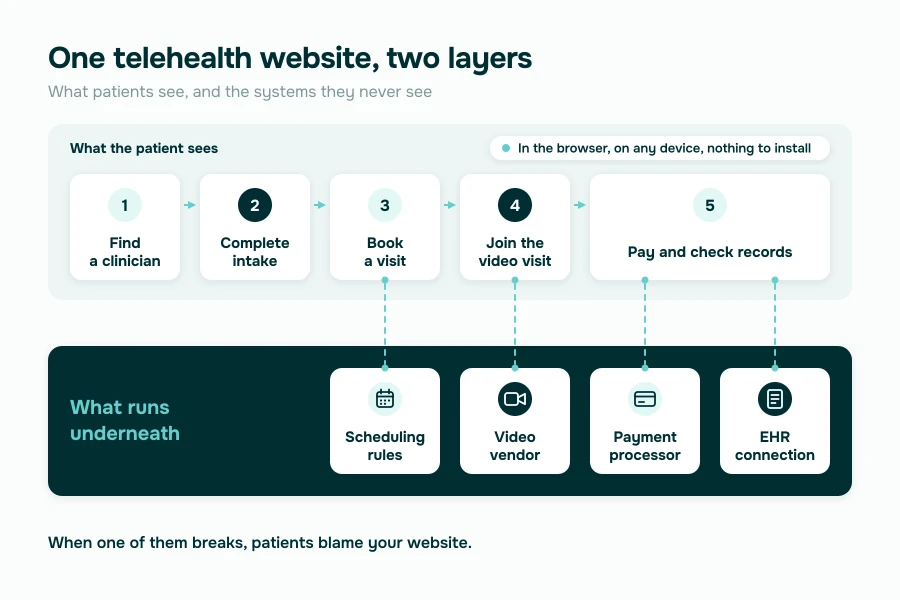
A telehealth website runs in the browser, so patients can go from booking to payment on whatever device they already own, with nothing to install. A telehealth app is a native iOS or Android build that ships through the app stores.
You can run both. A responsive website can carry the whole service at launch, and native apps can follow on the same backend.
Demand for telehealth website development services keeps growing
The global telehealth market was valued at $186.41 billion in 2025 and is projected to reach $219.31 billion in 2026, growing at a 24.6% CAGR through 2034 (Fortune Business Insights, 2026). That scope counts remote patient monitoring and telehealth products as well as virtual visits.
If you're shopping for telehealth website development services, look at where the care itself goes. Behavioral health made up 65.6% of telehealth volume in 2024 (Trilliant Health, 2026).
The market figure goes in your pitch deck, and the behavioral health share goes in your scoping doc. If therapy or psychiatry is on your service list, you're building for the biggest slice of that volume, and our guide to mental health app development covers the clinical product side.
Key features of a telehealth website
Telehealth website design starts with who's on the page. We sort features four ways: patients, the whole site, providers and admin staff.
Patient-facing features cover the whole visit
Patient engagement rides on these:
- Appointment scheduling: Open slots plus appointment and follow-up reminders, the booking flow we break down in doctor appointment app development.
- Patient portal: Records and test results behind one login.
- Video consultation: Live audio-video through a vendor that signs a BAA, on its HIPAA-grade plan.
- Async messaging (store-and-forward): Patients send secure messages, photos, forms or records that a clinician reviews later. HHS notes it's often used for intake and follow-up care (HHS, 2024).
- Accessibility tools: Multilingual support and easy-to-read text.
Site-wide features sit under every page
- Security: Encryption in transit (TLS 1.2 or later) and at rest, unique user logins, role-based access, audit logs and automatic logoff.
- EHR integration: Certified EHRs have to provide a standardized HL7 FHIR API (ONC criterion 170.315(g)(10)), and middleware covers the systems that don't.
- Symptom checker: A questionnaire that suggests when to see a clinician or which kind of care fits. FDA lists tools like this among the software functions where it doesn't intend to enforce device rules (FDA, 2022).
- E-prescribing: A third-party integration with its own contract and BAA (the build itself is covered in e-prescription app development).
Controlled substances bring in DEA's EPCS rules (21 CFR part 1311): identity proofing before a prescriber gets a signing credential, two of three authentication factors on every controlled-substance prescription, and a third-party audit or DEA-approved certification before use, repeated every two years or whenever that function changes. An EPCS-certified e-prescribing vendor carries that audit.
Provider features keep the chart close
Clinicians need the record open during the call:
- Notes and templates: Faster visit documentation.
- Patient history: Medical records and EHR data on demand.
- Multi-device support: Move between an office workstation and mobile devices mid-shift.
Admin features handle the back office
- Scheduling oversight: Department calendars in sync, with canceled slots offered to the waitlist.
- Billing: Payment processing and reimbursement tracking.
- Provider dashboards: Session lengths and patient outcomes.
- Staff onboarding: Accounts and permissions for new clinicians.
Conversion and patient acquisition need a short booking path
A new patient should see where to start the moment your homepage loads.
Design for the phone first: 91% of US adults own a smartphone, and 16% go online only through their phone, with no home broadband (Pew Research Center, 2025 survey).
In Experian Health's 2025 State of Patient Access survey, 80% of patients said they want to schedule appointments anytime from home or a mobile device, while 55% of providers said patients are unsure how to use self-scheduling (Experian Health, 2025).
Close that gap with a short path to a booked visit:
- booking one tap from the homepage
- open times before any account setup
- intake that saves progress between steps
- only the questions the first visit needs
How to build a telehealth website, step by step
Building the site takes six steps, each with a compliance checkpoint. Knowing how to build a telehealth website mostly comes down to clearing each checkpoint in the step that owns it.

Plan around two gating decisions
Start with a roadmap that names your primary users and core features, then check competitors for gaps you can fill. Settle two questions before design starts:
- which states you'll serve, since that sets the licenses your clinicians need
- whether any visit can end in a controlled-substance prescription, since that decides whether live video is mandatory
Both are gating decisions. Get either one wrong and you rebuild intake and the visit flow later.
Assemble the right development team
Whether you hire a telehealth website development company or an internal team, staff it with people who know healthcare rules as well as code: developers, UX designers, security experts and QA testers, plus a project lead who owns the timeline.
Any agency, contractor or vendor that will handle real patient data signs a BAA first (45 CFR 164.502(e)).
Select a technology stack
If native apps are on your roadmap too, read how to build a telehealth app before you pick a backend. For the website itself:
- Core stack: One responsive interface for every screen size, on cloud hosting that holds up as patient volume grows.
- AI integration: Routing only, pointing patients to the right kind of care.
Shortlist only hosting, video and e-prescribing vendors that will sign a BAA. HHS counts a cloud provider storing patient data as a business associate even if it holds only encrypted data and no key (HHS, 2022).
If your plan put controlled substances in scope, the e-prescribing tool also needs the third-party audit or certification DEA requires (21 CFR 1311.300).
Create wireframes and prototypes
Wireframe the user flows first, then prototype them to fine-tune the web design.
- Share early: Show stakeholders prototypes with clear navigation and short forms, and refine from their feedback.
- Accessibility pass: Check contrast, keyboard paths, form labels and target sizes against WCAG 2.1 AA, or 2.2, while changes are still free.
Develop and test
Split the development process into short sprints, with testing and deployments automated so every release ships the same way. Put each sprint's build in front of end users to catch blind spots.
Run vulnerability scans and a penetration test before launch. HHS's proposed Security Rule update would make both mandatory, so treat them as baseline even though today's rule doesn't require them.
Launch and improve the website
Before real patients arrive, confirm that:
- the HIPAA risk analysis is done (45 CFR 164.308(a)(1)(ii)(A))
- every BAA is signed
- no third-party trackers fire on login, intake or booking pages
- the state and prescribing rules are enforced in the flow itself
Then launch to a small group to shake out bugs, and let session length and engagement show what to improve on the site.
Ask any telehealth website development company you're considering where each of these checkpoints lands in its project plan.
Compliance requirements for telehealth website development
Telehealth website development picks up rules a brochure site never meets, and they shape telemedicine website design at intake and booking.
DEA tele-prescribing and the Ryan Haight Act set your visit flow
The Ryan Haight Act requires at least one in-person evaluation before a practitioner prescribes a controlled substance online. DEA and HHS have extended the COVID-era flexibilities built on its exceptions four times, through December 31, 2026 (DEA, 2025).
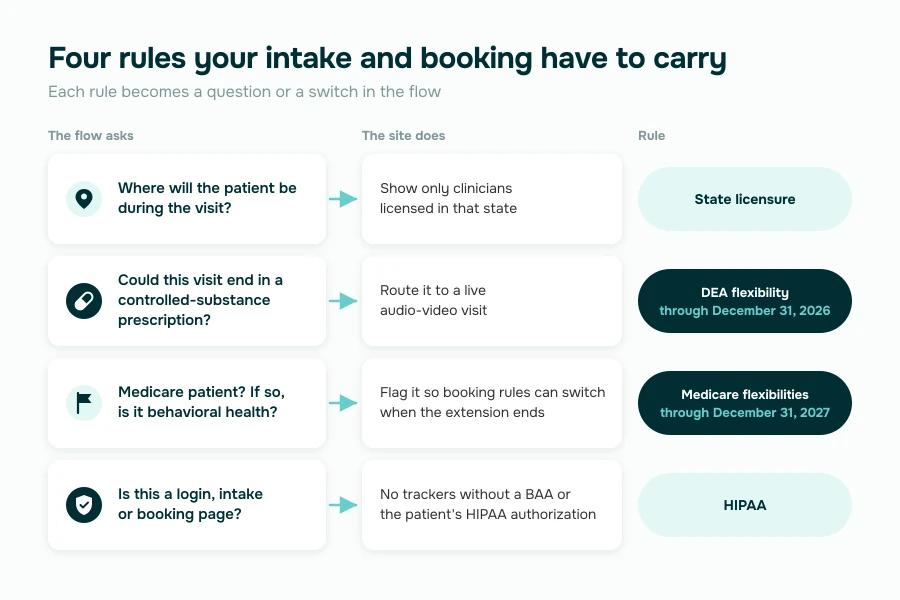
Until then, DEA tele-prescribing rules let registered clinicians prescribe Schedule II to V controlled substances without an in-person evaluation, if the visit is live audio-video and other DEA and state rules are met. Audio-only is allowed just for Schedule III to V opioid use disorder medications.
A questionnaire reviewed later doesn't qualify, so route any site path that can end in a controlled-substance prescription into that live audio-video visit. Async still has a job on the site, and our post on asynchronous telehealth platform development maps where it fits.
Special registration would permanently replace the flexibilities, and DEA's January 2025 proposal includes a registration for online telemedicine platforms connecting patients with prescribers of Schedule II to V drugs (DEA, 2025).
If your website does that, watch the final rule, under White House (OIRA) review since August 25, 2026, with a November 2026 agenda target and no public text yet (Reginfo.gov, 2026; Unified Agenda, 2026).
Without that rule or another extension in time, the in-person requirement returns on January 1, 2027 for patients a prescriber has never seen, apart from narrow exceptions. Flows for these drugs need a switchable in-person step:
- ADHD stimulants such as amphetamine and methylphenidate (Schedule II)
- buprenorphine (Schedule III)
- phentermine, or benzodiazepines such as alprazolam (Schedule IV)
GLP-1 drugs such as semaglutide aren't controlled substances (21 CFR part 1308), so a GLP-1-only flow sits outside these rules until it adds phentermine.
State licensure follows the patient
Your clinicians need a license or other legal permission to practice in the state where the patient is located (HHS, 2024). So your intake asks where the patient will be during the visit, and matching shows only clinicians licensed there.
A state licensure compact shortens the route, profession by profession, though no compact covers every state:
- IMLC: 44 member states plus DC and Guam as of August 31, 2026, four still implementing (IMLCC, 2026). Qualifying physicians get one expedited process, then separate state licenses.
- NLC: The Nurse Licensure Compact has been enacted in 43 jurisdictions, with Guam, Massachusetts and the US Virgin Islands still implementing (NCSBN, 2026).
- PSYPACT: Covers telepsychology for psychologists.
- Counseling Compact: Live for counselors in nine states (Counseling Compact, 2026).
Medicare telehealth flexibilities have an end date
Pandemic-era Medicare telehealth rules, which cover patients at home anywhere in the country and audio-only visits, run through December 31, 2027 (Consolidated Appropriations Act, 2026).
Unless Congress extends them again, most revert on January 1, 2028, when patients generally must be in a medical facility in a rural area (CMS Telehealth FAQ, 2026).
Behavioral and mental health are the permanent exception. Those patients can keep being seen at home, but starting that same day, Medicare wants an in-person visit within six months before the first mental health telehealth visit and at least every 12 months after.
For Medicare patients, reuse the licensure location question and flag behavioral health services, so booking rules can switch when the extension ends.
HIPAA compliance hinges on who handles patient data
If your website is run by or for a provider that sends standard transactions such as claims or eligibility checks electronically, it's in HIPAA scope from the first intake form, as is every vendor handling patient data for that provider (45 CFR 160.103). A slip costs fines and patient trust.
The pandemic pass for consumer video apps without a BAA closed August 9, 2023 (HHS OCR, 2023).
- BAAs: Every vendor handling protected health information needs one before real data flows (45 CFR 164.502). That usually means video, hosting, e-prescribing, messaging, forms, scheduling and analytics that see patient data. Our guide on how to make a website HIPAA compliant has the full checklist.
- Encryption: It's addressable for data in transit and at rest, so implement it or document why an equivalent safeguard is reasonable, and for telehealth that argument is hard to win (45 CFR 164.312).
- Logins: Unique user IDs are required, with access limited by role.
- Audit logs: Required too, covering who opened, changed or exported a record.
On pages where patients log in or enter health details, tracking technologies can disclose patient data. That needs a BAA with the tracking vendor or the patient's HIPAA authorization, and a cookie banner isn't that authorization (HHS OCR, 2024). A 2024 ruling struck down the public-page part of HHS's tracking guidance and left the rest standing (AHA v. Becerra, 2024).
HHS's January 2025 Security Rule proposal would require encryption, multi-factor authentication, vulnerability scans at least every six months and a penetration test at least every 12 months (90 FR 898). Final action is estimated for July 2027 (Unified Agenda, 2026). We'd build to it now: on a new website, it costs little.
GDPR compliance can reach a US website
GDPR reaches a US website offering services to people in the EU or monitoring their behavior there, even with no EU office (GDPR Art. 3(2)). Processing health data, a special category (Art. 9), needs a specific condition, usually explicit consent or care by confidentiality-bound health professionals.
- Record the condition behind each use of health data. If that condition is consent, make withdrawing it as easy as giving it (Art. 7(3)).
- Collect only the personal data the visit needs (Art. 5(1)(c)).
- Map record-retention duties before honoring erasure requests, since Art. 17(3) lists exceptions.
- Cover EU-to-US vendor transfers with a safeguard such as standard contractual clauses (Art. 46(2)(c)).
HHS moved its WCAG accessibility deadlines
If you receive federal financial assistance from HHS, Section 504 requires your website and apps to meet WCAG 2.1 Level AA (HHS, 2024). In May 2026 HHS pushed the deadlines back a year: May 11, 2027 for recipients with 15 or more employees and May 10, 2028 for smaller ones (HHS, 2026).
On every intake and booking page, start WCAG accessibility checks with these criteria:
- Keyboard: Every control works without a mouse (2.1.1).
- Text alternatives: Images and icons carry them (1.1.1).
- Contrast: Text stays at 4.5:1 or higher (1.4.3).
- Label in name: Each button's accessible name includes its visible label, so voice-control users can say what they see (2.5.3).
Meeting WCAG 2.2, the current W3C Recommendation, also meets 2.1 (W3C, 2024).
Telehealth website trends for 2026
A trend matters to your website when it changes a page you have to build.

Async telehealth starts with a form
More telehealth now opens with questionnaire intake, secure messaging and subscription checkout. In async telehealth, the website carries the intake a visit used to, so the clinician's first read of the patient is whatever your form captured.
Build that form like a chart note, and route any path through it that could lead to a controlled-substance prescription into a live visit.
GLP-1 product pages draw FDA warning letters
Compounded GLP-1 drugs get sold from telehealth product pages, and that's where the FDA looked. In March 2026 it sent warning letters to 30 telehealth companies over website claims implying compounded GLP-1s are the same as FDA-approved drugs (FDA, 2026).
Put your product pages and eligibility screens through the same review your clinical protocols get.
Mental health care sets the booking pattern
Among commercially insured patients, mental health conditions were the top telehealth diagnostic category in every age group and every US region in early 2026 (FAIR Health, 2026). Therapy runs as a series of visits, so the booking flow needs:
- recurring slots with the same clinician
- matching patients to therapists licensed in their state
Patients arrive self-triaged
More patients show up with a chatbot's opinion: 32% of US adults have used an AI chatbot for health information, double the 16% a year earlier (Rock Health, 2026). So AI intake on your website should ask what the patient already suspects, then route them to the right visit type. For intake automation and staff handoffs, our guide to AI agents for healthcare covers workflow limits and review points.
Ambient scribes land on the provider side
In January 2026, 29% of US physicians surveyed used ambient listening or AI scribe tools, up from 20% in April 2025 (Doximity, 2026). Doximity sells AI tools to physicians, so read that as a vendor's survey.
On the website, the scribe belongs in the provider console. Add a patient consent step before it starts listening, and check the recording rules in every state you serve.
Challenges in telehealth website development
The same six problems show up for an in-house team and for a telemedicine website development company.
Budget constraints hide in HIPAA work
Underestimating costs for HIPAA compliance is the classic budget miss, and hosting and maintenance after launch are the easy lines to leave out. The cost section below shows what drives HIPAA cost and gives the yearly maintenance ratio.
Solution: Create a phased roadmap that ships what a first visit needs and adds the rest in order of patient demand.
Integration schedules slip on legacy systems
On a telehealth website, integration means moving patient records between the site and the practice's EHR:
- Certified EHRs: Their standardized FHIR API, covered under key features, gives your website a documented way to connect.
- Legacy systems: Anything without that API needs middleware, which usually slips the schedule.
Hire for integration expertise with the exact EHR you're connecting to, test sandbox included.
Demand spikes test the backend
Telehealth demand comes in spikes, and a website that slows down under load usually has a thin backend. Host on cloud infrastructure that adds servers as traffic climbs, and split into separate services once one part needs to grow on its own.
A rushed build pays for its speed after launch
Rushed telehealth builds ship bugs and security holes, and both cost more to fix once patients are on the site.
Keep the sprint routine from the build steps when the launch date tightens, and pick a team experienced in custom healthcare software development so the deadline doesn't eat the testing.
Communication needs one tracker and one tiebreaker
Designers, developers, compliance advisors and clinicians all have a say in every screen. When their priorities drift apart, work gets redone and the budget absorbs it. Keep decisions in one project tracker, since communication that lives only in meetings gets re-argued a sprint later.
Pro tip: Give one project manager the final call when clinical and technical priorities collide.
Security risks fall on patients
Phishing, ransomware and DDoS attacks can take a telehealth website offline and put patients at risk. Today's Security Rule and HHS's proposed update set different bars for these defenses:
- Multi-factor authentication: It's standard practice on clinician and staff logins today and would become mandatory under the proposal.
- Automatic logoff: Signing out idle sessions is already an addressable safeguard under today's rule (45 CFR 164.312(a)(2)(iii)).
- Penetration testing: The proposal would require it.
- Encryption: Encrypt stored and transmitted patient data to the NIST guidance HHS points to, and a stolen copy doesn't trigger breach notification, as long as the key wasn't compromised too (HHS, 2013).
Put all six problems to any team you shortlist as interview questions. Teams with real expertise answer with a past project and the thing that broke on it.
Telehealth website development cost
To build a telemedicine website, you pay twice: once for the build, then every year to keep it running. Scope sets the first bill, and the second follows from it.
Features decide the tier
From scratch, the telehealth website development cost lands in one of three tiers:
| Tier | What it includes | Cost | Timeline |
|---|---|---|---|
| MVP | Responsive patient website with appointment booking, online intake, video visits through a HIPAA-eligible vendor, and payments | $40,000 to $80,000 | 3 to 5 months |
| Mid-complexity | Adds async messaging, e-prescribing integration, provider and admin panels, and multi-state licensure logic | $80,000 to $150,000 | 5 to 9 months |
| Full-featured | Adds EHR integration, analytics, multi-specialty support and custom workflows | $150,000 to $300,000 or more | 9 to 12+ months |
A mid-level healthcare app with telemedicine features runs $80,000 to $150,000 (GoodFirms, 2026). The scope splits are our editorial read of a telehealth website build.
Complexity and integrations move a quote up the table: every extra user role adds screens, and every EHR or e-prescribing connection adds build work.
A telehealth website usually prices below a native telemedicine app, because one responsive build serves phones, tablets and desktops, while native iOS and Android apps are two more builds, each with its own app store review. Our guide to telemedicine app development cost prices the native route.
Upkeep runs by ratio, HIPAA by scope
The same GoodFirms guide (April 2026) puts annual maintenance at 15 to 25% of the initial build: $12,000 to $20,000 a year on an $80,000 website, and $22,500 to $37,500 on a $150,000 one.
Push back on any quote that adds HIPAA as a percentage of the build. HIPAA cost depends on how many screens and services touch patient data, and which controls each one needs:
- access control
- audit logging
- encryption
- a signed BAA behind every vendor that handles PHI
Building on Specode is priced by the month
On Specode, Pro is $1,000 a month with 2,200 credits, one published project, production deployment, hosting setup and a custom domain. Custom starts at $5,000 a month (Specode docs, 2026), and third-party services such as video, messaging, e-prescribing and analytics bill separately.
From scratch or on Specode, launch the must-have features as an MVP and park the rest, which keeps spend in check during the website's creation.
How Specode helps with telehealth website development
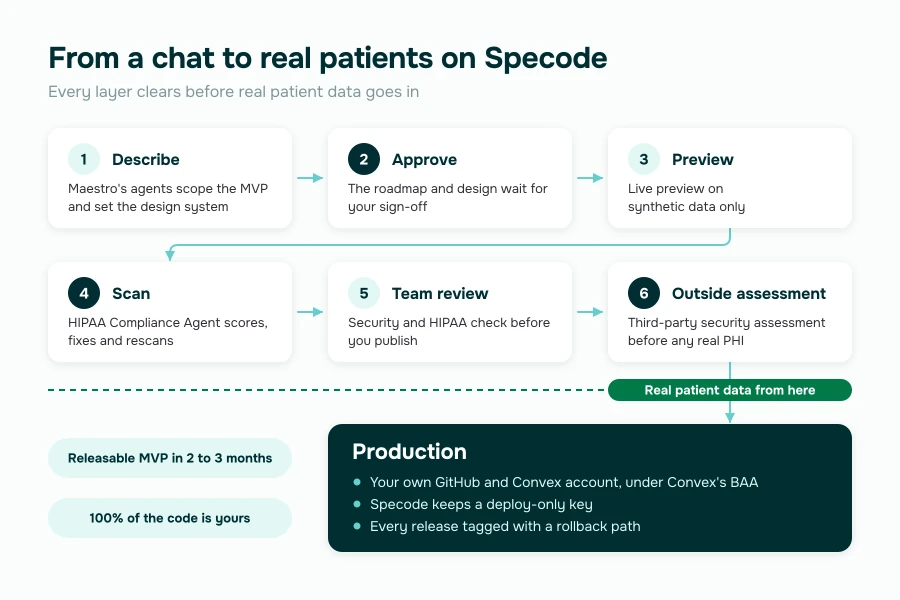
Specode is an AI builder made for healthcare. For telehealth web development, you describe the website in plain English, and Maestro's agents scope the MVP, set the design system and write the code.
You approve the plan before any code exists
The roadmap and the design both wait for your sign-off. Then the website takes shape in a live preview, from intake and booking to the video visit and payment. Previews aren't HIPAA-compliant, so you test with synthetic data only.
The website Specode builds is fully responsive, so it works in phone and tablet browsers. Speed to market is essential. On Specode, a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build.
Specode connects your vendors through their APIs and your own credentials, on any plan (Specode docs, 2026):
- EHR and EMR systems such as Epic and Cerner
- lab systems
- pharmacy networks
- insurance verification
The Custom plan adds advanced integrations. Video visits and in-app messaging run on CometChat, whose standard accounts aren't HIPAA-compliant. Pay for its HIPAA subscription before the first live patient visit.
HIPAA best practices get checked more than once
Specode builds on a HIPAA-ready foundation. Its HIPAA Compliance Agent scans your code by category, gives it a compliance score, fixes what it finds and rescans. The score follows today's Security Rule, and the proposed 2027 requirements show up as recommendations you can adopt early or suppress.
On the way to real patient data, the release path stacks security best practices in layers:
- Your own accounts: Production runs in your own GitHub repository and Convex account, under Convex's self-serve BAA, and Specode keeps a deploy-only key.
- Team review: Specode reviews security and HIPAA compliance before you publish.
- Outside assessment: A third-party security assessment comes before any real PHI.
- Rollback: Every release is tagged with a rollback path.
- Pen test: An optional $3,000 in-house test, for when procurement or an enterprise customer asks for the report.
Our docs are explicit that the HIPAA Compliance Agent doesn't guarantee full HIPAA compliance on its own, so keep your counsel in the compliance call.
The code is yours, and the results are public
Section 8.2 of our terms gives you 100% of the code, on a standard React, Tailwind, Shadcn and Convex stack any team can pick up, with a 60-day export window if you leave. If licensing a ready-made branded platform might fit better than building one, weigh a white label telehealth platform against the build.
AlgoRX built and scaled their platform on Specode. It's a direct-to-patient storefront for non-controlled prescription medications, where patients complete product-specific questionnaires and providers review orders and can message patients in the app before fulfillment.
AlgoRX's case study reports 12x ROI, more than $1M in sales closed by month 2 and a 7-figure ARR within 6 months of launching. Video visits aren't part of that case study.
Book a demo when you're ready to build a telemedicine website, and we'll scope it with you. Within a week of signing up you get a custom starting template built for your product, with a walkthrough video. Support runs 24/7 at support@specode.ai.
Frequently asked questions
From scratch, $40,000 to $80,000 for an MVP, $80,000 to $150,000 for mid-complexity and $150,000 to $300,000 or more for full-featured, plus 15 to 25% of the build a year in maintenance. On Specode, Pro is $1,000 a month plus your vendors' fees.
From scratch, 3 to 5 months for an MVP, 5 to 9 for mid-complexity and 9 to 12 or more for full-featured. On Specode, a releasable MVP takes 2 to 3 months, 30 to 60% faster than a traditional custom build.
A DEA-registered clinician writes the prescription, and your website decides which visits can lead to one. Through December 31, 2026, DEA's fourth temporary extension lets clinicians prescribe Schedule II to V controlled substances without a prior in-person exam, after a live audio-video visit (audio-only is allowed for opioid use disorder medications). The final version of DEA's permanent special registration rule has been in White House review since August 25, 2026, with a November 2026 agenda target. If nothing replaces the extension, the in-person requirement returns on January 1, 2027 for patients a prescriber has never seen, apart from narrow exceptions. GLP-1 drugs aren't controlled substances, so a GLP-1-only program sits outside these rules.
The licenses belong to your clinicians, who need one in every state where their patients are during visits. The Interstate Medical Licensure Compact (44 member states plus DC and Guam as of August 31, 2026) gives a qualifying physician one expedited process, then a separate license in each state. Your site's job is to capture the patient's location at intake and match them only with clinicians licensed there.
A telehealth website runs in any browser, and a telehealth app is a native iOS or Android build installed from an app store. The website usually costs less, since one responsive build serves every screen size, while native apps add a build per platform, each with its own app store review. On Specode you get the website, a responsive web app that works in phone and tablet browsers. There's no native iOS or Android output today, and app-store apps are a separate build that can reuse the same backend.
HIPAA applies when the website is run by or for a health care provider that bills or checks insurance electronically. It covers the provider's patient data on the site and every vendor that handles it. A purely cash-pay company may fall outside HIPAA and still answer to the FTC's Health Breach Notification Rule and state laws such as Washington's My Health My Data Act. If it handles patient data for covered clinicians, it's likely their business associate. There's no official HIPAA certification for a website, and HHS doesn't endorse or recognize private ones. On Specode, the HIPAA Compliance Agent scans your code and Specode's team reviews security and HIPAA compliance before you publish. Neither is a certificate or a substitute for your own risk analysis.


