
White Label Telehealth Platform: Vendors, Costs and How to Launch (2026)

Updated October 2026
What is white label telehealth?
A white label telehealth platform is a prebuilt virtual care system you launch under your own brand instead of building the video, scheduling, intake, and HIPAA plumbing from scratch. It suits health systems, specialty networks, behavioral health groups, and digital-first providers who need a branded telehealth platform this year rather than after the next budget cycle. Configuring and branding a vendor's white label telehealth product typically takes 4 to 8 weeks, building a real platform you own on an AI builder runs 2 to 3 months of focused work, and a custom build runs 6 to 18 months. Vendor licensing is usually quote-only; white label telehealth platform cost on Specode lands around USD 5,500 to 7,000 all in, plus the HIPAA tier on every third-party service that touches PHI.
Key Takeaways
- What white-label actually buys you: a white label telemedicine app lets you skip the commodity build (auth, video, scheduling, and the HIPAA plumbing) and spend your engineering on the care model instead.
- What it doesn't buy you: the clinical infrastructure. A medical director, written protocols, and a professional corporation structure under Corporate Practice of Medicine rules stay on your side of the line, whichever vendor you pick.
- Timeline is an effort question, not a platform question: prototypes take days, a lean production app takes weeks, and a real product takes months of full-time focus. Teams building in spare hours run considerably longer.
- Cost sits mostly outside the platform: the HIPAA tier on each third-party service handling PHI, from messaging to email, moves your budget more than the platform fee does.
White label telehealth and telemedicine platforms compared
Most white label telehealth software comparisons rank vendors on feature checklists. Features are the least differentiated thing about them. What actually separates a white label telemedicine platform is who supplies the clinicians, what you own when you leave, and whether anyone independent has audited the compliance claims.
The shortlist, one line each:
- OpenLoop and Wheel: clinicians included. Both bundle affiliated physician groups and medical-director oversight, which solves the staffing half and limits how much of the clinical model you control.
- VSee: the strongest attestation stack in the table. A BAA on all clinic plans, SOC 2 Type II, and a FedRAMP High ATO through HHS ASPR.
- 98point6: EHR writeback. Epic and Cerner integration with bidirectional pull and writeback is the most credible documented sync in the set.
- Healthie: practice management. It comes at telehealth from the EHR and operations side, which fits groups that already live there.
- VCDoctor: self-hosting. The only vendor here with a client-hosted tier.
- Specode: code ownership. The only one whose contract transfers the code to your repository.
We reviewed the public materials of every vendor below in October 2026: product pages, terms, security documentation, developer docs, and SEC filings where they exist. Where a cell says not published, it may still exist under NDA. The gaps matter, because these are the terms that decide what happens to your business in year three.
| Vendor | What it actually is | Clinical infrastructure | Code ownership and exit | Named EHR integrations | Independent attestation |
|---|---|---|---|---|---|
| OpenLoop Health | Hosted white-label stack with optional clinical and operational services | Included: clinicians, affiliated PCs, medical director with final protocol approval, CPOM-compliant structuring | No IP transfer. The SEC-filed agreement (S-4/A Exhibit 10.11) keeps IP with each party, bars reverse engineering, and sends patient records to a partner-chosen EMR at termination | Schedule D names Healthie, with API calls and webhooks in both directions | Acts as a HIPAA business associate and publishes a Subcontractor BAA (audit report required, PHI returned within 20 days of termination). SOC 2 Type 1 announced January 7, 2025; no report public |
| Wheel | Hosted white-label platform bundled with clinicians and clinical operations | Included: 50-state clinician network, affiliated PCs, medical-director oversight, 70+ care programs | Usage license. Source, self-hosting and termination export not published; terms allow deletion of your data after termination | None named. API retrieval and transmission described without standards or direction | HITRUST-aligned; says SOC 2 certified, without publishing type or date |
| VSee | Hosted SaaS and API stack, white-label on the Enterprise plan | Clinician staffing through a separate company (This American Doc); medical director and standing orders not published | Licensed. Source and self-hosting not published; exit is report and API export only | Epic and Oracle Health (Cerner) documented via HL7, FHIR, APIs and SFTP | BAA on paid clinic plans, SOC 2 Type II, and an HHS ASPR FedRAMP High ATO |
| 98point6 Technologies | Hosted white-label SaaS licensed to organizations bringing their own clinicians | Technology only. The company says it no longer operates a clinic | Licensed software. Source, self-hosting and termination export not published | Epic and Cerner over HL7 and FHIR, with bidirectional pull and writeback | No current SOC 2 report or BAA terms public |
| Healthie | Hosted EHR and telehealth SaaS; white-label and headless APIs on Enterprise | Technology only. Clinicians and clinical governance are yours | Export your data before cancellation; no export window is published, and data is retained at least six years. Source and self-hosting not published | FHIR and C-CDA, with bidirectional exchange through Zus | HIPAA with BAA, SOC 2 Type II (recertified March 2024) and HITRUST R2 |
| VCDoctor | Prebuilt white-label product, hosted or on your server, built by DreamSoft4u | Technology only. Terms state it is not a healthcare provider | The only vendor here with a client-hosted tier. Source ownership not published; API export claimed | None named. HL7, FHIR and APIs mentioned without direction | Self-claimed HIPAA, BAA advertised, no SOC 2 status published |
| Specode | AI builder that produces a conventional codebase you own | Technology only, stated plainly. No clinicians, medical director or PC structure | Code ownership in the contract: transfer to your repo within 5 business days, 60-day export window after termination | Epic, Cerner and others through their APIs, built as real integration work | You sign the production BAA with Convex. Not SOC 2 certified; the managed backend it runs on is. Built-in HIPAA scan, optional USD 3,000 pen test |
What the empty cells tell you
Read down the ownership column. Of seven vendors, one publishes contractual code transfer terms, one has a client-hosted deployment, and one gives a data export window. The rest don't say.
The one place we found actual terms, an OpenLoop agreement filed with the SEC because a customer had to disclose it, says nothing in it transfers IP and that patient data goes to a partner-selected EMR when the relationship ends.
Exit terms exist in every one of these contracts. They're simply not on the website, which means you will negotiate them from a position of not knowing what normal looks like. Ask for the termination and data-portability clauses on the first call.
Then read the attestation column. Three of seven have a current independent audit worth the name.
Several claim HIPAA compliance with nothing behind it but their own security page, and two rest on attestations old enough that the report period has likely lapsed. HIPAA has no certification, so "HIPAA compliant" is a self-assessment unless someone names an auditor, and you should ask who actually holds the attestation. A platform relying on its cloud provider's SOC 2 is a reasonable, materially different answer.
One more column that isn't in the table: whether the vendor will still be here. Several are publicly traded or owned by companies that are, so their financial condition is public record.
Read the liquidity and going-concern language before you sign a multi-year contract, because a migration forced by someone else's balance sheet is the most expensive kind. For private vendors, ask about runway directly.
Choosing by what you actually lack
The clinical infrastructure column is the real fork here, and it maps to a question about your own company rather than about software.
If you don't have a medical director, protocols, and a PC structure, and standing those up isn't something you want to spend two quarters on, the bundled platforms solve a genuine problem. OpenLoop and Wheel supply clinicians, affiliated professional entities, and medical-director oversight, and OpenLoop's filed agreement even warrants CPOM and fee-splitting compliance. You're buying a business in a box, and accepting less control over the clinical model and, on current evidence, no code ownership.
If you already have the clinical side, or you're a health system that inherently does, the bundle is redundant and its constraints are pure cost. Then the question narrows to which technology you would rather live inside in three years. Healthie comes at it from practice management, 98point6 from enterprise licensed software with the most credible documented EHR writeback in the set, VCDoctor from the low end with the option of hosting it yourself, and Specode from the position that you should end up owning the code outright.
Three vendors we researched didn't make the table. Oystehr is a hosted API and headless-EHR toolkit with a forkable reference app, genuinely useful for developer-led builds, and its license bars using it to build a competing product. MyTelemedicine and DrCare247 both bundle clinician networks and both publish very little on BAA tiers or exit terms; DrCare247 does publish a security page claiming HIPAA safeguards, BAAs in place, and SOC 2 "independently examined", with no type, auditor or date.
Adjacent options exist if none of the above fits. SteadyMD, now owned by DocGo, pairs white-label technology with a national clinician network.
Bask Health and Turbopills target direct-to-consumer telehealth spanning intake through pharmacy fulfillment; we walked through what Bask ships in our Bask Health review. And for a ranked comparison of platforms to buy, start with our guide to the best HIPAA-compliant telehealth platforms.
How white label telehealth compares to custom and SaaS
Every telehealth program starts from the same three-way decision: build it yourself, buy someone's SaaS, or launch a white-label platform under your own brand. A white label platform, whether the label says telehealth or white label telemedicine, is a prebuilt core that one or many organizations brand and run as their own, with customizations on top.

White label vs. custom build vs. off-the-shelf SaaS
The trade-offs, side by side:
| Dimension | Build from scratch | Off-the-shelf SaaS | White label platform |
|---|---|---|---|
| Time to launch | 6 to 18 months, more for full-stack builds | Days to weeks | 4 to 8 weeks configured, 2 to 3 months owned |
| Cost structure | USD 40,000 to 300,000+, unpredictable overruns | Low per-seat subscription | Predictable license plus targeted custom work |
| Brand and control | Everything yours, nothing prebuilt | Vendor's brand, fixed workflows | Your brand and workflows, room to customize |
| Compliance | You build HIPAA controls, logs and BAAs from zero | Inherited, rarely your call | HIPAA-ready modules with audit trails pre-validated |
| Features | Everything custom-built | Fixed set, vendor roadmap | Commodity features prebuilt, dev time goes to the care model |
| Integration paths | Costly EMR and billing work, years of upkeep | Limited, or gated behind enterprise tiers | Prebuilt hooks and unified data models |
| Maintenance and tech debt | All yours, compounds fast | Vendor's, but you cannot fix or extend | Centralized upkeep, plus your own code if the contract says so |
| Scaling | Capacity planning and load audits on you | Vendor tiers | Auto-scaling foundation, modular reuse |
| Exit | Yours by construction | Data export, if they allow it | Depends entirely on the contract |
For most providers, white label is usually the practical middle. You skip the development overhead and compliance work of a custom build, but you keep brand identity, room to customize, and the ability to integrate with the systems you already run. Off-the-shelf SaaS gives you the first of those only if you accept the vendor's brand, workflows, and roadmap, and the vendor lock-in only becomes visible the day you try to leave.
What you inherit on day one:
- Core telehealth flows (intake, triage, visit, documentation, billing) already implemented.
- HIPAA safeguards and auditability built into the platform instead of bolted on at the end.
- Your team's time going into differentiation: the clinical model, the care programs, the UX.
The newest version of this idea is the HIPAA compliant app builder, where an AI assembles the app from a plain-English description rather than a vendor handing you a fixed product to configure.
Private label vs white label
"White label" and "private label" get used interchangeably, but there's a useful distinction. White label usually means a shared core product that multiple organizations brand and configure on common infrastructure. A private label telemedicine platform implies more isolation: a dedicated environment, deeper customization, or stricter data and integration boundaries for one organization.
For most buyers the label matters less than the control surface: can you enforce your own security policies, model your own roles and care pathways? Good white label platforms give you enough private-label control where it counts without losing the economies of reuse.
What's in the stack
A serious platform is more than a video widget and a calendar:
- Responsive frontends for patients, providers, and admins, built for accessibility and clinical-grade reliability on any screen.
- Backend services for identity, permissions, scheduling, virtual doctor visits, messaging, and payments.
- A data and compliance layer with PHI-aware schemas, audit logging, retention policies, and encryption in transit and at rest.
- An integration fabric for EHR systems, billing, eRx, lab vendors, and analytics.
Some platforms are glorified video chat with a logo on it. Others are a healthcare-grade app framework built for reuse across programs. You're buying an architecture your team has to live with for years, so weigh it as an architecture decision.
What's not in the stack: your clinical infrastructure
Every vendor in this category sells technology. Almost none sells the clinical and legal apparatus a virtual care business runs on, and that gap catches founders out more often than any technical limitation does.
You still have to stand up:
- A medical director for clinical oversight. Licensure follows the patient's location, and whether you need an in-state medical director and written protocols varies by state and service line.
- Written protocols and standing orders defining what your providers can treat asynchronously and what has to escalate to a synchronous visit.
- A professional corporation (PC) structure in states with Corporate Practice of Medicine (CPOM) rules. In many states a corporation can't employ physicians, so groups run a physician-owned PC linked to the management company through an MSO agreement.
- Provider licensing, credentialing, and malpractice coverage across every state in your footprint.
Get legal counsel on the corporate structure budgeted before you budget the software. The software is the cheaper problem.
Who should consider white label telehealth?
If you're a health system adding virtual care across service lines, a specialty network standardizing intake and follow-ups, a behavioral health group, or a company selling branded platforms to payers and employers, white label is how you get a branded front door without a multi-year build. If you're a single-location practice wanting video visits and scheduling, an off-the-shelf platform will cost less and take less of your time. The use cases below map the fit.
Market demand
Grand View Research sized the global telehealth market at USD 77.4 billion in 2025 and USD 87.7 billion in 2026, projecting USD 187.5 billion by 2033 at 11.5% a year (Grand View Research, 2026).
Epic Research analyzed 411 million primary care visits from July 2022 through October 2025 and found telehealth holding at 6% to 7% of visits, with mental health above 26% virtual in October 2025, per Healthcare Dive (Epic Research, 2026). Neither figure captures the direct-to-consumer telehealth companies operating outside Epic's EHR, so the true share sits higher.
White label telehealth platform cost
Here's the real economics of a white-label telehealth platform, sized the way a founder or CFO would size it: how vendors actually price, what the build costs, the line items that sneak up on you, and where the return comes from.

Pricing models
Four models dominate, and the right one depends on your scale and how much risk you want up front.
| Model | How it works | The trade |
|---|---|---|
| Subscription | Recurring license, monthly or annual, per user or facility | Predictable, often caps customization |
| License plus customization | Base license, paid integrations, branding and workflow logic | Buys control, front-loads cost |
| Usage-based | Scales with patients, sessions, or throughput | Fair until a growth spurt lands with an invoice |
| Transaction or revenue share | Vendor takes a cut of platform revenue | One OpenLoop agreement filed with the SEC prices on transaction fees plus processing percentages, with the figures redacted |
What vendors actually publish
Here's the awkward part of researching white label telehealth platform pricing: most vendors won't tell you. We checked the public materials of these platforms in October 2026.
| Vendor | Pricing model | Published figures |
|---|---|---|
| VCDoctor | One-time fee by tier, plus support | USD 1,500 to 6,100 one-time depending on tier and whether mobile is included; support from USD 500 per quarter up to ten providers, then USD 30 to 45 per provider a month. Client-hosted tier is quote-only. |
| Oystehr | Platform floor plus usage | The greater of USD 1,000 a month or 5% of usage fees, plus USD 0.25 per active user, USD 0.004 per video minute, and USD 35 to 45 per provider a month for eRx. |
| VSee | Per-provider subscription | Free tier, Plus at USD 29 and Premium at USD 49 per provider a month; Enterprise is quoted. |
| Healthie | Per-provider subscription | Core from USD 19.99 to Group from USD 149.99 a month; Enterprise is quoted. |
| DrCare247 | Per-provider, PMPM, or per-encounter | Publishes nothing today; directories disagree at USD 25 per provider a month in one place and USD 15 in another. |
| OpenLoop | Transaction fees plus processing percentages | Publishes nothing; cost varies by service mix, buyers go to sales. |
| MyTelemedicine | Not disclosed | Publishes no rates and states no model, routing buyers to a demo. |
Wheel, 98point6 and Bask publish no pricing either. Two takeaways: third-party pricing data is close to worthless (the DrCare247 figures differ by a factor of two and a half across directories), and a vendor's willingness to publish pricing tells you how much of the deal they expect to negotiate.
What building it yourself costs
Published vendor guides put a custom telehealth build at USD 40,000 to USD 300,000 or more, from basic MVP to enterprise platform.
| Complexity | Typical cost range | What drives the cost |
|---|---|---|
| MVP / basic telehealth (video, scheduling, auth) | USD 40,000 to 70,000 | Standard UI, few integrations, basic security and hosting |
| Mid-level telehealth (messaging, eRx, basic integrations) | USD 70,000 to 150,000 | More complex flows, broader compliance scope, richer data handling |
| Full-featured enterprise telehealth (EHR integration, multi-role, high scale) | USD 150,000 to 300,000+ | Deep EHR workflows, multi-environment hosting, serious security engineering |
Typically 6 to 18 months to production, with full-stack builds running out to 24. Our telemedicine app development cost guide breaks those ranges down line by line. A white-label platform turns most of that into license or subscription cost.
What it costs on Specode
Since we ask other vendors to publish, here is ours in full. This is white label telehealth platform cost for a real, HIPAA-ready launch, not a starting-from price.
| Line item | Cost | Notes |
|---|---|---|
| Specode subscription | USD 1,000 a month | Pro is the entry plan for production: HIPAA Compliance Agent access, weekly team support, and an on-demand human security review. Custom starts at USD 5,000 a month for managed development. |
| Build time | 2 to 3 months | So USD 2,000 to 3,000 in subscription to reach a real working product, assuming someone is on it full-time. |
| Production backend | USD 25 a month | Your own Convex Pro account, covering database, real-time engine, and hosting. You sign Convex's self-serve BAA in your dashboard, so there is nothing to negotiate. |
| Penetration test | USD 3,000 one time | Optional. Most teams add it when procurement or an enterprise customer asks. |
| Video and messaging | USD 359 a month | CometChat's Advanced plan, billed annually, carries the HIPAA terms and its own BAA. |
| Transactional email | Quote only | Your email provider's HIPAA plan is quoted separately. Budget for it as an unknown until you have the quote. |
| Everything else touching PHI | Varies | Payments, labs, eRx, SMS. Each is its own BAA and often its own compliance tier. |
Call it USD 5,500 to 7,000 to stand up a branded, HIPAA-ready platform you own outright, against USD 40,000 at the very bottom of the custom range.
Notice which line is unbounded. It's the last one.
Every third-party service that touches PHI has a compliance tier, and those tiers are priced for enterprises rather than for launches. Two identical-looking builds can differ by five figures a year purely on which services they connect. That's the single most underestimated number in virtual care budgeting.
The hidden costs that derail projects
Five costs get underestimated even on a white-label platform, and they cluster exactly where projects fail:
- Compliance scope creep: extra spend on integrations, PHI handling, multi-jurisdiction policy, audits.
- BAA tier inflation. The line above, listed twice on purpose.
- Integration entropy: every EHR, lab, pharmacy, and API costs more to maintain than to wire up.
- Support and change management. Onboarding providers, training staff, documentation, help desk.
- Regulatory drift: privacy, residency, and reimbursement rules keep moving, and keeping up keeps costing.
Ignore these and a cheap build gets expensive quietly. Clarity on total cost of ownership beats a low upfront quote every time.
When white-label pays for itself
Here's the payback arithmetic with your inputs and our costs, no invented numbers.
Your monthly contribution per virtual visit is what you bill minus what it costs you to deliver, using your own staffing, space, and admin numbers. Divide the launch cost above by that margin.
At USD 5,500 to 7,000 to launch and 200 visits a month, the platform is paid back inside the first quarter. At 40 visits a month it takes closer to a year. At 2,000 visits a month the platform cost stops being a line anyone discusses.
Payback turns on visit volume.
Ongoing costs and total cost of ownership
Going live doesn't stop the spending: hosting and video bandwidth, security and compliance upkeep, support, third-party APIs, and regulatory work as the rules move. The license fee is one line; total cost of ownership (TCO) covers integration work across EMR, billing, CRM, and reporting systems, plus years of maintenance.
On a custom build, the planning heuristic most teams use is 15% to 20% of the original build cost every year for maintenance and compliance. A USD 150,000 build carries USD 22,000 to 30,000 annually before anyone ships a new feature.
On a subscription platform, that line is the subscription, and it doesn't compound. That's the actual argument for white label on TCO, rather than the sticker price. Our telemedicine app development guide breaks down the resourcing trade-offs if you want to go deeper.
Looking to launch a compliant telehealth solution under your brand? Let's build it together.
What the ROI actually looks like
Search for telehealth ROI figures and you will find a tidy set: 315% over three years in behavioral health, 4x on remote monitoring, break-even in eight weeks. Trace any of them and the trail ends at a vendor blog citing another vendor blog. Keep them out of your board deck.
The numbers that survive scrutiny are delivery-cost studies. Penn Medicine measured its own on-demand telemedicine service against in-person care across primary care offices, emergency departments, and urgent care: USD 380 to deliver against USD 493 in person, USD 113 per visit (Penn Medicine, 2023). A 2019 Jefferson Health study in the American Journal of Emergency Medicine put net savings at USD 19 to USD 121 per telemedicine visit and USD 309 to USD 1,546 per avoided ED visit (AMA, 2019).
On the revenue side, the returns concentrate in programs that carry their own reimbursement rails rather than in video visits alone: remote patient monitoring (CPT 99453, 99454, 99457, 99458), chronic care management (CPT 99490 and its add-ons), and tele-psych, where virtual is already the dominant modality. A white-label platform earns its return by cutting the time and cost of getting onto those rails.
How to launch a white label telehealth platform
Going live with a white label telehealth platform is a sequenced project rather than a rebuild. The eight steps, one sentence each:
- Define programs and roles. Name the clinical programs, map the patient and provider journeys against real workflows, and set roles and permission scopes.
- Plan the scope. Decide what ships in the MVP and what defers to phase two, and wire up analytics before launch rather than after someone asks for a number.
- Brand it. Styling has to reach the apps, portals, onboarding, and notifications, with accessibility and mobile in the same pass.
- Integrate. Define the EHR, billing, labs, pharmacy, eligibility, and eRx connections, including directionality and conflict resolution.
- Test. Run the care model end to end, including negative paths, security checks, and load.
- Set up accounts and BAAs. Stand up hosting, messaging, email, and payment accounts, each with its BAA signed before launch.
- Pilot. One specialty, one region, one success metric, four to eight weeks.
- Scale. Add providers, regions, or service lines one variable at a time.
The timeline ladder: a first working build takes about 10 minutes, a shareable prototype a couple of days, a basic production-ready app 1 to 2 weeks, and a real product with EHR, pharmacy, or billing integrations behind it 2 to 3 months. Custom development covering the same ground runs 6 to 18 months.
The variable is hours per week. Teams building full-time hit those numbers; teams building in spare hours run considerably longer.

Define programs and roles
Start with the clinical programs you're launching, urgent care, mental health, chronic care management, or remote patient monitoring, and map the patient and provider journeys against actual workflows. Then define roles and permission scopes for front desk, MAs, providers, billing, and admin, and confirm the regulatory posture: state licensure, credentialing, prescribing rules. The output is a deployment-ready scope tied to real reimbursement and real volume, which stops scope creep three weeks in.
Plan the scope
Decide what ships in the MVP and what defers to phase two. Tailor the UX for your specialty's triage and documentation patterns rather than accepting a generic template, and plan the multi-brand structure now if you will be running affiliates on the same core.
- Ship: the flows that carry your core care model, nothing decorative.
- Defer: anything a stakeholder can live without for one quarter.
- Measure: analytics definitions agreed before go-live.
Brand it
Patients judge your technology on sight, often before using a single feature. Brand styling has to reach every surface: the apps, the portals, onboarding, and notifications, with the homepage being the least important of them. Accessibility refinements go in the same pass (font scale, contrast, cognitive load), and mobile gets its own review, since most encounters start on a phone.
Integrate
Telehealth has to fit the financial and clinical plumbing you already run:
- EHR and billing connections defined in detail, including directionality and conflict resolution
- Labs and pharmacy connectivity, if either sits in day-one flows
- Insurance eligibility and claims data mapped early
- eRx workflows, where prescribing is in scope
- API governance: versioning, failure handling, monitoring
Budget real time here: field mapping and error paths usually take several rounds, and this stage is what prevents the classic go-live conversation about revenue not posting correctly.
Test
Testing has to cover the whole care model end to end, and the screens are the easy part. Run end-to-end simulations across intake, triage, visit, documentation, and billing.
Then negative paths: no-shows, mid-visit disconnects, denial routes. Then security validation: role-based access, audit trails, access revocation, load checks for Monday-morning surges. Test auth on the deployed build, not a preview, and keep real patient data out of every preview environment: those URLs aren't covered by your BAA.
Set up accounts and BAAs
Before real patients touch the platform, the accounts and agreements have to exist. Open the hosting account your app will run in, the email service with its HIPAA tier, the payment account, and the domain DNS. Then sign a business associate agreement (BAA) with every service that touches PHI: hosting, messaging, email, payments, labs, anything else you connect.
One agreement can cover several services, but each business associate that handles PHI needs one. Run the security review before go-live. Whichever platform you pick, the same set of accounts and agreements has to exist somewhere.
Pilot
Run a controlled pilot: one specialty, one region, one success metric, four to eight weeks, with weekly reviews. Split findings into must-fix-before-scale and can-wait. You're proving the model is clinically safe, operationally viable, and worth scaling; perfection isn't on the list.
The pilot is also where your payback math either holds or doesn't: if the volume assumptions are off by half, this is the cheap moment to find out. Track a small set from day one: visit volume, no-show rate, time-to-appointment, connection success, error rates, support tickets by type. Dashboards and alerts exist before go-live, or your first monitoring system is an angry inbox.
Scale
Once the pilot stabilizes, resist turning it on for everyone. Add providers, regions, or service lines one at a time so you can still tell what caused what, and revisit staffing and workflows at each expansion.
Treat every major feature wave, ePharma, RPM, or group visits, as its own mini-pilot. Every state or country you add brings its own licensure, credentialing, and entity requirements, and those move on legal timelines. Plan around whichever is slower.
Integrations: EHR, payments, labs, pharmacy and insurance
Most white label platforms offer surface-level branding and call it enough. Real digital health solutions have to plug into clinical records, billing rails, pharmacy networks, lab vendors, and care-coordination systems.
Set one expectation first: none of this is a toggle you flip. Each integration is real work, mapping fields, handling error paths, and deciding what happens when two systems disagree about the same patient.
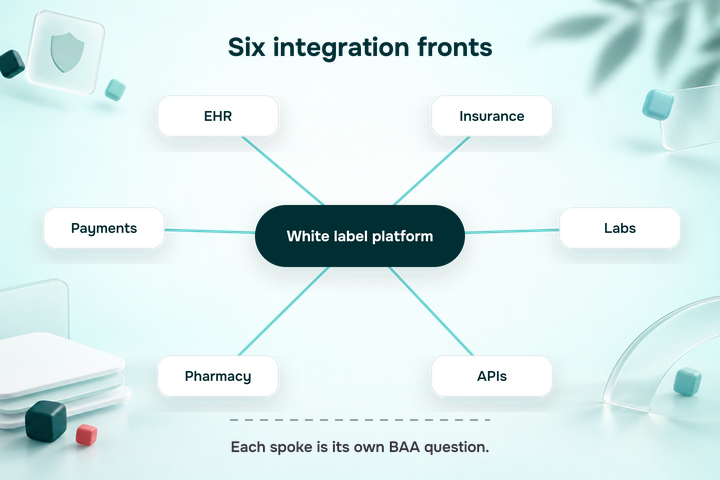
EHR and EMR integration
Your clinical system stays the source of truth, and the job is to meet it where it lives. That means FHIR and HL7-based interoperability, secure API pipelines with audit-grade data lineage, and patient context hand-offs between virtual encounters and in-person workflows.
Epic and Cerner go through their published API programs, and the work is real integration engineering rather than a connector you enable. What you avoid is the fragmentation of clinical data that shows up whenever a telehealth app gets built beside the EHR instead of into it.
Payments and billing
The financial plumbing has two separate questions, and most vendors only answer the first. The mechanics: PCI-compliant payments, real-time eligibility and copay estimates, billing that handles subscription and per-visit models alike. The question underneath is which processor.
Stripe is the default and works cleanly for non-clinical revenue, but telehealth consultations and prescriptions sit in Stripe's restricted categories and Stripe doesn't sign BAAs, so those flows need an approval or a BAA-signing processor. Clinical detail stays out of the payment record entirely: generic descriptors, no diagnosis in metadata, no CPT codes on invoice lines. Deciding this during the build costs a conversation; discovering it after launch costs a migration.
Laboratory connections
Diagnostics are where a lot of telehealth products quietly stop being useful. What gets built: orders and results exchange, LOINC-driven mapping for labs and vitals, notification hooks that trigger provider follow-up, and multi-state lab partner support. Many off-the-shelf tools collapse at exactly this point, leaving the workflow stuck at the lab slip and the follow-up happening over email.
Pharmacy and eRx
Virtual care without prescribing is urgent care with no door. What gets built: eRx workflows matching the rules in each state you operate in, medication history retrieval, configurable formulary controls, and specialty pharmacy routing.
The prescription stays tied to the clinical reasoning behind it rather than arriving at a pharmacy as a bare instruction. Prescribing also changes the payments picture and, in some flows, brings LegitScript certification into scope for card-not-present medication sales. Where controlled substances are in scope, EPCS requires DEA-compliant identity proofing at NIST level 3 or higher, two-factor credentials, and audit trails reviewed daily.
Insurance verification
Coverage ambiguity kills appointment conversion, so the boring parts get automated: eligibility checks through clearinghouses, a visible claims lifecycle, denial triggers routing straight into tasking and remediation, and payer-specific metadata captured for compliance. Every unverified patient is either a write-off or a phone call.
Third-party API management
As your care model evolves, the platform has to absorb new services without becoming a pile of duct tape: AI for triage or documentation plugged in as a service, remote monitoring devices syncing through secure API mediation, role-aware integration governance, and vendor uptime monitoring. Real-time video and messaging sit on a third-party service too, which makes them a BAA question: whoever runs them handles PHI and needs an agreement to match.
CometChat on its HIPAA plan brings its own. Our healthcare app development guide covers the broader architecture patterns.
Compliance and security questions for white label vendors
Integration is the part everyone demos; compliance decides whether you survive an audit. A credible white-label approach has to deliver the same governance, auditability, and patient-safety guarantees as an in-house clinical system, and that comes from architecture rather than a security page. Ask these of any white label telehealth platform vendor, ideally with their engineers in the room, and demand specific answers rather than paragraphs from the website.

HIPAA compliance architecture
Real HIPAA support is a design system rather than a feature. The controls that carry it: PHI isolated through role-based access control (RBAC) and tenant-aware data segmentation, immutable audit trails for every create, read, and update tied to a user identity, data minimization so only clinically necessary information reaches each component, and least-privilege defaults so a compromised account has a small blast radius.
Ask which identity protocols are actually wired in, because "enterprise SSO" and "SAML with your IdP" aren't the same commitment. Then ask the vendor to name one feature that sits outside those guardrails, and listen to how fast they can answer.
International regulations and data residency
Platforms that scale across borders localize compliance per jurisdiction while keeping one codebase: GDPR-driven consent models with data residency actually enforced, retention windows that differ by region, and granular control over cross-border exchange of clinical information. If you're selling into the NHS or Canadian provincial systems, ask directly about the certification layers those buyers require, such as the UK's DSPT, because the answer is either yes with evidence or no.
Data residency is the one to press hardest on: where PHI physically lives, and whether you can move it later without rewriting the app. Vendors who can't answer that in one sentence are telling you something.
Data privacy and protection
Privacy reduces to a single principle: every data access tracks the clinical reason for it. The mechanics are encryption across transit and internal service links, segregated keys with rotation, anomaly detection on patterns like mass exports and out-of-hours access, and formal governance of third-party access through revocable, scoped credentials.
Encryption alone does nothing about privilege creep. You also need access revoked the moment the reason for it ends, which is an operational discipline rather than a feature you buy.
Security audit and monitoring
Observability is what turns compliance from a launch event into a state you can prove: continuous vulnerability scanning and dependency inspection, alerting on identity anomalies and failed-access bursts, and structured logs that hold up under external examination, with no PHI in them. On penetration testing, get a clear answer on who runs it, how often, and what remediation looks like. On attestations, the precise question is whose: many platforms rely on their infrastructure provider's SOC 2 rather than holding one themselves, which can be a perfectly good answer as long as the vendor says so plainly.
Disaster recovery planning
When a clinical system goes down, patients can't get care, which makes downtime a safety problem rather than an availability metric. Ask about failover across zones, backups with restore procedures somebody has actually executed, recovery targets stated in numbers, and graceful degradation for the workflows that matter most, such as a fallback communication channel when video fails mid-visit. A recovery plan nobody has rehearsed is a slide.
Compliance documentation
If it isn't documented, it doesn't exist as far as your risk officers are concerned. What they will want to see: current compliance status for your PHI workflows on demand, traceable lineage from requirement to implementation to monitoring, policy templates mapped to HIPAA and, where relevant, GDPR, and evidence bundles ready for vendor assessments and payer credentialing. Done well, this turns weeks of audit paperwork into hours of structured validation.
How to choose a white label telehealth vendor
The comparison above shows what a white label telemedicine platform vendor publishes. This section is about what you have to ask, because the important terms are almost never on the website.
Engineering that survives your team's questions
A partner has to do more than theme a UI. What to check, and what a real answer sounds like:
- Interoperability maturity. Which named systems, over which standards, in which direction, with a walkthrough of a live integration including what broke and how they found out.
- Extensibility. API-first architecture and modular code your team can extend without going through the vendor.
- Security engineering. Least-privilege enforcement, structured logging, encryption in transit and at rest, explained by someone who isn't reading from a slide.
- Operational practice. How deploys work, what monitoring exists, what happened during their last incident.
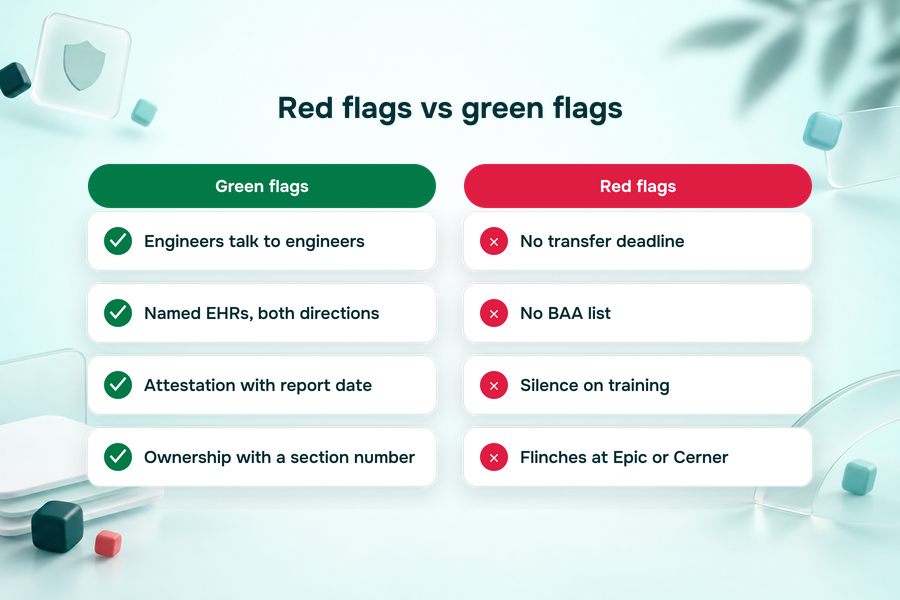
If a vendor won't let your engineers talk to their engineers, assume the technology doesn't hold up to inspection. And if their team flinches when you say Epic or Cerner, you have your answer early and cheap.
Domain blind spots become your regulatory failures
A vendor's gaps turn into your regulatory failures. A strong partner has the unglamorous parts down cold: credentialing, licensure, payer policy, and the PHI lifecycle from consent through access scoping to retention.
They design around the actual clinical journey, intake, triage, visit, documentation, billing, rather than screens. And they know specialty workflows don't transfer: behavioral health doesn't run like urgent care, and neither runs like physical therapy. A vendor who demos one and promises the others are configurable is describing work they haven't done.
Support when production breaks
Support decides how fast you recover when production breaks. Press on four points: who actually responds, frontend troubleshooters or compliance-literate engineers; how fast remediation moves when you're genuinely under pressure; what the subscription covers in security patches and regulatory updates; and whether anything happens on its own, or the system only moves when you file a ticket. Without real support behind it, you own every outage yourself.
Press hard on references
Vendors all demo well. The questions that get past it: do they have live deployments in regulated care models, can you get past the product sponsors to the clinicians using it daily, and how did they handle a go-live under stress, a surprise integration, a compliance audit.
Then the one that settles it: would the client hire them again? Anything short of an immediate yes is your answer.
Get these five things in writing
Everything above is judgment. These are the clauses, and the comparison table shows how rarely any of them appear in public materials, which means you have to ask.
- Code ownership, stated as ownership, not "usage rights" and not "perpetual license." If you own it, the contract says so and names a section.
- A transfer mechanism with a deadline. Who hands over what, in what format, within how many days of a request.
- A termination and export window. What happens to your code, your configuration, and your patient data when the relationship ends.
- A BAA, plus the list of everything it doesn't cover. Production hosting is usually covered. Video, email, payments, labs, and eRx usually aren't.
- A no-training clause on your data. Whether the vendor can use your code, prompts, or patient data to train or benchmark any model, aggregated and de-identified included. Ask explicitly, because silence isn't a no.
Those five clauses are also the risk section of your business case. Delivery risk drops when you start from a proven codebase, compliance risk when controls are inherited rather than reinvented, execution risk when you pilot before committing, and exit risk only when ownership is spelled out. If ownership isn't, assume you own nothing except future invoices.
Architecture questions to ask
Four questions separate a platform you can build on for years from one you will outgrow:
- Where does PHI live, and under which tenancy? Single-tenant per customer means higher isolation and a simpler compliance story; logically multi-tenant means shared infrastructure with strict tenant boundaries. Ask whether you can move onto your own cloud subscription later without rewriting the app.
- Is the platform API-first? Every core capability, intake, visits, messaging, billing, outcomes, should sit behind versioned APIs with clear resource contracts. Without that, your platform is another SaaS product with your logo on it.
- Who runs real-time video and messaging, under which BAA? Video consultations live on WebRTC with TURN/STUN fallback, and whoever hosts them is handling PHI. Get the provider's name and the agreement that matches, encrypted streams and scoped tokens included.
- Is the AI replaceable? PHI-touching models should stay walled off from non-PHI ones, and you should be able to swap one model vendor for another without rewriting the app. The day AI gets welded into the core codebase is the day a vendor pivot becomes a platform rewrite.
Questions to ask before you sign
Take these to every vendor on your shortlist, including us:
- If I buy a white label telemedicine app from you, will I own the codebase, and which contract section says so?
- What is the transfer mechanism, and how long does it take?
- What happens to my code and my data if I leave?
- Which named EHRs do you actually connect to, in which direction, and can I speak to that customer?
- Which third-party services will touch PHI, and which BAAs do I sign myself?
- Who holds your compliance attestation, and what is its report date?
- Can you supply clinicians and a medical director, or is that mine to build?
- What does your last production incident look like?
Compare that against traditional healthcare app development and the difference in what you're buying becomes obvious quickly.
White label telehealth by use case
Who is a white label telehealth platform actually for? The answer splits into six groups, and white label telemedicine fits each differently. For all six, white label telemedicine software is a faster path to market than a custom build.
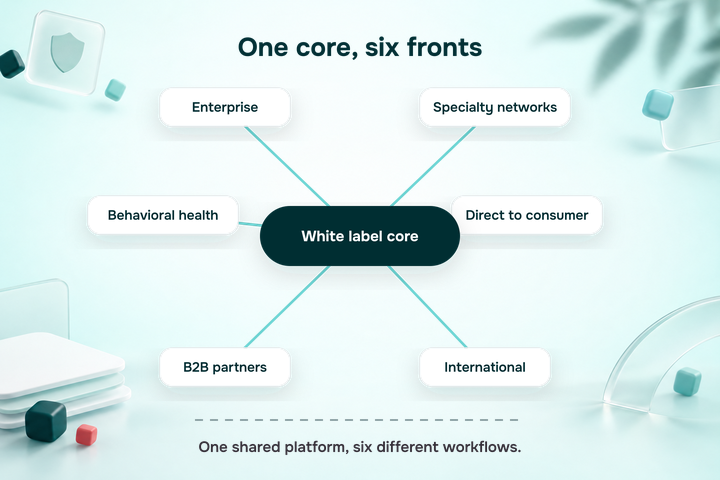
Enterprise health systems
Large healthcare organizations and IDNs need a branded telehealth platform with real EHR integration and HIPAA discipline at scale, which is a different problem from needing a nice app. The pattern: branded patient and provider portals for hospitals and doctors sitting on top of existing Epic and Cerner flows, with multi-site configuration for affiliates and partner clinics. A regional hospital chain can extend branded telehealth to dozens of satellite clinics without stitching three third-party platforms together to do it.
Specialty practice networks
Multi-location medical practices in cardiology, oncology, urgent care, pain, and women's health need workflows tuned to their specialty, and generic templates are exactly what they can't use. Virtual pathways for triage, follow-ups, chronic care, and remote patient monitoring with RPM reimbursement codes run on a shared backbone, so each practice gets its own flavor while operations stay manageable. A multi-state network can standardize intake, consults, and follow-ups centrally while each clinic localizes its own content and availability.
Behavioral health platforms
Mental health and addiction care run on trust, privacy, and continuity, which is also why this is the one vertical where virtual has already won: more than a quarter of mental health visits happen remotely. The flows that matter are one-on-one and group therapy sessions, longitudinal tracking for mood and medications, and hybrid models combining tele-psych with in-person care.
The typical shape is a multi-state group practice with role-based access and secure messaging from day one. Worth reading alongside our guide to integrating with behavioral health EHRs, since TherapyNotes and SimplePractice don't integrate the way Epic does.
Direct-to-consumer healthcare
DTC brands need consumer-grade patient experience and medical-grade compliance, quickly. White label means subscription programs, asynchronous consults, labs and ePharma flows, and follow-up automation, without building the stack underneath.
A virtual clinic selling cash-pay chronic care bundles gets app-based onboarding, telehealth, medication management, and patient engagement on one platform. This is also the vertical where the payments question gets decided early: prescribing anything means a processor that signs a BAA, and it's much cheaper to know that in week one.
B2B healthcare technology companies
If you're an agency, PBM, TPA, or employer-benefits vendor, reuse matters more than hero engineering. The play is shipping client-branded platforms in weeks instead of quarters, running the same hardened infrastructure across accounts and customizing only the fraction that's genuinely client-specific. One build can serve several brands or regions, which is the whole economic case for a services firm and its partners delivering branded virtual care to payers and employer plans.
International markets
Cross-border telehealth has to respect local regulation, language, and payer models. That means localization, configurable consent flows, and region-aware logic, so country-level rules get handled without forking the core.
A virtual-first provider launching in the US, UK, and EU runs one shared platform with country-specific onboarding, pricing, and compliance behavior. One caveat that applies across all six groups: the platform travels, and your clinical and corporate structure doesn't. Every state and country you enter brings its own licensure, credentialing, and entity requirements, which is the part to budget legal time for.
Whether you're a provider or a partner, we'll help you deliver high-quality virtual care.
White label telemedicine app: web, iOS and Android
A white label telemedicine app is a white label telehealth app published under your own brand, and it usually ships one of three ways: a responsive web app that runs on any device, native iOS and Android apps, or both, with native mobile apps usually an enterprise add-on.
The practical details matter more than the feature list. Two details decide the budget: whose developer account publishes it in the app stores, and what app store publishing adds to cost and timeline.
Apps usually sit in your own Apple and Google developer accounts, and the vendor often handles submissions and updates for you. Apple typically reviews at least half of submissions in under 24 hours and 90% in under 48 (Apple, 2026), and medical apps can get extra scrutiny under its health-data rules. Google Play's health policy adds its own declarations, and both stores require a privacy policy and data-safety disclosures.
Native adds real cost and timeline: Bask Health puts custom native builds at USD 150,000 or more and 12 to 18 months (Bask Health, 2026), and that's a vendor estimate, but the direction is real.
Ask a vendor these before you buy: who owns the app-store listing, who handles store review and updates, and whether video and push notifications run under a BAA. Any vendor that creates, receives, maintains, or transmits PHI needs a BAA, and app-store distribution doesn't change that.
On Specode, the honest answer: you can't vibe-code native apps. The platform ships one responsive web app that installs to the home screen and runs as a progressive web app (PWA), with push on Android and, since iOS 16.4, for home-screen web apps, with limits native apps don't have.
On the Custom tier the Specode team can assist with native apps using tools like Capacitor. Native apps aren't the platform's primary offer, and we will say so on the first call.
Specode: a white label telehealth platform you own
Most white-label vendors hand you a product to configure. Specode is a white label telehealth platform with a difference: you describe the app in plain English, the AI builds it on HIPAA-ready foundations, and what you end up owning is a production-grade codebase your own developers can read, extend, and deploy like anything else they build.
The distinction matters only on the day you need a workflow your vendor hasn't built, or your vendor gets acquired. From the Pro plan up, weekly hands-on support, bug fixes, and small implementations come with the subscription, and platform improvements arrive continuously rather than as version upgrades you migrate onto. That support is healthcare-savvy: people who have shipped clinical apps and debugged real EHR integrations, not a customer service queue reading from a script.
What the AI builds and how the build works
The build runs through two agents, and you approve each handoff. The Planning agent scopes the MVP through conversation: who the users are, what "shipped" means for v1, and it turns the answers into a prioritized roadmap you sign off on before any code gets written.
The Design agent takes your brand direction and produces a design system covering color, typography, component styles, spacing, and motion, applied across the whole app. You approve the design before implementation starts.

From there the build flow: describe the app in plain English, watch it come together in a live preview with desktop, tablet, and phone views, and iterate on flows, rules, and data through conversation with auto-save and rollback.
Connect real-shaped data early, test records or synthetic patient data, so the UI reflects actual patients and providers; previews are outside your BAA, so real PHI stays out. What gets built is the usual telehealth surface: a branded patient portal, intake, appointment scheduling, secure messaging, secure video visits, payments, health questionnaires, outcomes tracking, pharmacy flows, provider portals, admin dashboards. AI agents in healthcare can also run inside the product for triage, documentation help, and eligibility checks.
The production checklist is short and concrete: your GitHub repo connected to the app you're building in Specode, your own Convex Pro account at USD 25 a month covering database, real-time engine, and hosting with a self-serve BAA, Mailgun on its HIPAA plan with DNS records configured, your custom domain pointing at the app, and BAAs signed with every service that touches PHI.
Publishing is self-serve: the only gate is a green HIPAA audit with every Must-Fix finding resolved, and the app goes out through your own GitHub and Convex accounts when you're ready. An optional penetration test is available when procurement asks for one. How that stack compares with the leading platforms is covered in our top telemedicine apps for doctors and patients roundup.
HIPAA Compliance Agent and optional penetration test
Every vendor in this category says HIPAA-compliant. Here's what it means on Specode, concretely.
The HIPAA Compliance Agent scans your codebase on demand with a multi-agent review rather than a single pass: two agents search from opposite directions, one tracing patient data forward from where it enters to everywhere it could surface, the other starting at risky operations like downloads, notifications, and API routes and working backward to see whether PHI reaches them. A third agent re-reads the code and drops any finding it can't confirm against the source.
Findings come back across 11 categories, including role-based access control, audit logging, encryption, PHI exposure in URLs, file uploads, API security, MFA, and log sanitization. Each is split into Must-Fix and Nice-to-Fix, with the file, the line, the offending code, a data-flow trace, and a recommended fix.
Every finding explains why the fix matters, and you pass the fixes straight back to the AI builder to apply. This audit is required before you can publish: every Must-Fix finding has to go green first. Every scan is saved with a score, so compliance progress is a record you can hand to a reviewer.
The penetration test is the optional step, and it is a different job from the HIPAA audit. Independent security professionals try to break into your live app the way an attacker would, then show you exactly what to fix.
Publishing only waits on the HIPAA audit. The pen test is the extra step most teams take once the app handles real patients: first results within 5 to 7 days, end to end often 2 to 3 weeks, and re-tests covered for 90 days.
Specode doesn't run it in-house and doesn't sign a BAA. At go-live, you sign the BAA with Convex for production hosting. The report comes back to you, and you apply the fixes in your Specode account.
Underneath it: audit logging wired into every approved PHI read and write, with scalar-only metadata that never carries PHI values. MFA as a build step. Encryption in transit and at rest at the platform level.
Role-based access enforced centrally. Preview and demo environments outside the BAA.
On attestations, we're direct: Specode isn't SOC 2 certified. The managed backend it runs on, Convex, is, and that's what goes into procurement conversations.
Any vendor telling you their whole stack is certified without naming who holds the certificate is worth a follow-up question. The agent has its own product page if you want the full detail on the HIPAA Compliance Agent.
Code ownership in the contract
Everyone in this category promises code ownership. Ours is in Section 8.2 of the terms: you own the code, Specode cannot repurpose, resell, or sublicense it, and it transfers to your repository within five business days on request.
Terminating opens a 60-day export window. Section 8.4 bars training, fine-tuning, or benchmarking any AI model on your code, data, prompts, or apps, aggregated or de-identified included.
Production runs in your own Convex Pro account, and the team moves the app over; a self-service connection is still rolling out. Apps can also run multi-tenant, so one build serves several brands or regions. When you compare white-label vendors, ask each one to point at the clause.
Results: AlgoRX and DyadSync
DyadSync turned spreadsheet-and-text-message anesthesiologist scheduling into a working platform for freelance surgeons and anesthesiologists: role-based onboarding, scheduling dashboards, in-app messaging, Stripe-powered payouts, feedback flows, and admin analytics, all built without funding a multi-quarter custom build.
AlgoRX built a medication storefront on our telehealth white label framework. Patients move through guided onboarding and eligibility screening, add several medications to one cart, and check out through a PCI-compliant, BAA-backed processor; providers handle credentialing, automated reviews, and secure chat from one dashboard. It reached USD 1M+ in sales by month 2 and seven-figure ARR by month 3, a 12x ROI on the build.
"They delivered our product on the exact day that they said that they would. And the best part was that product far exceeded any expectations that we had." - Adam Hotchkiss, founder, AlgoRX
The payments detail in those two is worth pausing on, because it's exactly the kind of thing that costs teams after launch. DyadSync runs on Stripe because it moves money between professionals with no clinical content attached.
AlgoRX prescribes, so it needed a processor that signs a BAA and sits outside Stripe's restricted categories. Same platform, different integrations, decided during the build rather than discovered at launch. Those are the decisions that decide whether a launch date holds, and the parts transfer to any white label telemedicine app.
Launch your platform in record time, let's talk timelines.
When Specode is the right call, and when it isn't
We're a good fit when:
- You want to own the code, not license access to a product.
- Your workflows are specific enough that configuring someone else's templates would mean compromising on the clinical model.
- You have, or can stand up, your own clinical infrastructure.
- Someone on your side can put real hours into the build over two to three months.
We're the wrong call when:
- You need clinicians, a medical director, and a PC structure supplied along with the software. The bundled platforms in the comparison above genuinely solve that, and we don't. Specode provides technology only, stated plainly.
- You need a fully white-labeled product live in three weeks with nobody dedicated to it.
- Your requirements are generic enough that an off-the-shelf platform would serve you fine and cost less.
That last one is a real answer. A single-location practice wanting video visits and scheduling doesn't need a custom codebase, and we will say so on a call. If you do want your brand, your workflows, and your code, that's exactly what this is built for.
Consolidation among white label telehealth vendors
White-label telehealth stopped being a side bet, and the vendor list is shrinking. Consolidation matters more for white label telemedicine than for most software categories, because a buyer can do everything right and still wake up holding a contract with a company that no longer exists. Look at the last three years:
- Florence acquired Zipnosis in 2023 and rebranded as Fabric in February 2024.
- eVisit acquired Bluestream Health in April 2023.
- Bright.md's technology went to Evernorth, and 98point6 acquired the remaining assets in January 2024.
- DocGo acquired SteadyMD in October 2025.
- ZapEHR rebranded as Oystehr in July 2024.
- MyTelemedicine rebranded its consumer service as Lyric Health in February 2022, with the white-label business continuing separately.
- OpenLoop acquired Season Health in April 2026.
Seven changes of ownership or identity among vendors a buyer would plausibly have shortlisted. The pattern is two tiers: large platform-as-infrastructure stacks powering many downstream brands, and niche vertical players built around behavioral health or remote monitoring.
That history is the entire argument for code ownership in a white label telehealth contract. Every one of those transitions left customers holding a contract with a company that no longer existed in the form they signed with.
If your platform is a license, an acquisition can force a migration you never budgeted. If your platform is a codebase you own, an acquisition changes nothing about your deployment. Ask what happens to your deployment if the vendor is acquired, and get the answer before you sign, in writing.
Frequently asked questions
Most vendors won't tell you their price. Of the platforms whose public materials we reviewed in 2026, four publish figures: VCDoctor at USD 1,500 to 6,100 one-time, Oystehr from USD 1,000 a month plus usage, VSee from USD 29 per provider a month, and Healthie from USD 19.99 a month. The rest are quote-only.
On Specode, a compliant launch runs USD 5,500 to 7,000 all in: the subscription across a two-to-three-month build, your production backend at USD 25 a month, and an optional USD 3,000 penetration test. Add the HIPAA tier for every third-party service that touches PHI, the line that varies most. Building the same thing custom runs USD 40,000 to 300,000 and up.
Configuring and branding a vendor's existing product takes 4 to 8 weeks. Building a platform you own takes a couple of days to a shareable prototype, 1 to 2 weeks for a lean production app, and 2 to 3 months for a real product with EHR, pharmacy, or billing integrations behind it.
Custom development covering the same ground runs 6 to 18 months, with full-stack builds reaching 24. The variable is hours per week: teams working full-time hit those numbers, teams building in spare hours run considerably longer.
On a platform, the app rides on the launch cost above: USD 5,500 to 7,000 all in on Specode, or a vendor's license fee, usually quote-only. Native iOS and Android builds change the picture.
Bask Health puts custom native builds at USD 150,000 or more and 12 to 18 months, and that's a vendor estimate, but the direction is real: native apps are usually an enterprise add-on with their own price and timeline. A responsive web app that runs as a PWA skips most of that cost. For the custom-build breakdown, see our telemedicine app development cost guide.
Usually for the platform itself, and almost never for everything else your app connects to. Production hosting typically carries a BAA, but video and messaging, transactional email, payments, labs, and eRx are each their own agreement with their own vendor, often on a more expensive compliance tier.
Preview and demo environments aren't covered by any of it. Ask any vendor to enumerate exactly which services you sign for yourself before you commit to an architecture.
Functionally, yes. Telehealth is the broader term covering remote clinical and non-clinical services, and telemedicine refers to remote clinical care specifically. In this market the two get used interchangeably, and the same platforms rank for both queries.
Depends on what you lack. If you lack clinicians and a medical director, OpenLoop and Wheel bundle them. If you need EHR writeback, 98point6 documents the strongest sync in the set.
If you need to host it yourself, VCDoctor is the only option. If you want to own the code outright, Specode is the only one whose contract transfers it. The comparison table above walks through the columns that decide it.
On Specode the honest answer is that you can't vibe-code native apps. The platform ships one responsive web app that installs to the home screen and runs as a PWA, with push support on Android and, since iOS 16.4, for home-screen web apps.
On the Custom tier the Specode team can assist with native apps using tools like Capacitor. Native apps aren't the platform's primary offer, and we will say so on the first call.
In most cases yes, and the software won't supply it. You need clinical oversight from a medical director, written protocols and standing orders, and in states with Corporate Practice of Medicine rules, a professional corporation owned by a licensed physician connected to your management company.
Whether the medical director must be licensed in each state varies, since licensure follows the patient's location. Licensing, credentialing, and malpractice coverage sit on your side too.
A few vendors bundle a clinician network, which solves this at the cost of some control over the clinical model. Specode provides technology only, so budget legal counsel alongside the software.
White label, on upfront cost and time to launch, usually by an order of magnitude. A custom telehealth build runs USD 40,000 to 300,000 and takes 6 to 18 months. Configuring a white-label product takes weeks, and building an owned platform costs USD 5,500 to 7,000 all in over two to three months on Specode.
The comparison narrows in two situations: when your requirements are unusual enough that you customize the white-label product so heavily you have paid for both, and over a three-to-five-year horizon, where a custom build carries 15% to 20% of its original cost annually in maintenance while a subscription platform doesn't compound.



