
AI Agents in Healthcare: Use Cases, Integration and How to Build One

Updated October 2026
AI agents in healthcare use models and approved tools to complete tasks such as scheduling or preparing documentation, with staff responsible for consequential decisions. Appointment requests, intake and documentation are useful starting points because you can measure completed work and the review it takes.
If you're evaluating AI agents for healthcare, start with one queue and specify what the software can change. Compare efficiency with your current process, including exceptions that come back to staff. These assistants need a defined job and a person who owns its results.
What should you know before building a healthcare AI agent?
A healthcare AI agent interprets requests and acts through permitted tools, with staff responsible for consequential decisions. Five practical starting use cases: scheduling, refill requests, patient Q&A, documentation drafts and intake or prior-authorization preparation. HIPAA compliance means covered services and the required agreements for production PHI, limits on what the agent reads, changes and records, and human review at consequential steps. Typical build time: Specode's quick start documents a 3-to-5-screen prototype in about 10 minutes; production EHR access, security checks and clinical validation need separate planning.
Key Takeaways:
- Start with a measurable task: An AI agent for healthcare needs a clear completion rule and an escalation route.
- Approve record changes deliberately: Confirm the exact API operation and permissions before allowing write-back.
- Check the service chain: Model and telephony agreements apply to specific services and configurations.
- Budget for operation: Include staff review and recurring service costs when evaluating a pilot.
What are AI agents in healthcare?
AI agents in healthcare are software systems that use artificial intelligence, often large language models (LLMs), to interpret requests and choose permitted actions through tools. Their behavior depends on the context and permissions you supply. Clinical decisions and consequential record changes need explicit limits and appropriate human review. Unlike a chatbot that only answers messages, an agent acts through permitted tools to complete a defined task. The main types are patient-facing, clinician-facing, administrative and voice agents.
Anthropic's 2024 architecture guide distinguishes predefined workflows from agents that choose their next steps. Agentic AI in healthcare can use either approach.
AI agents vs. chatbots vs. agentic AI
Compare these reference patterns. Memory and tool access depend on implementation.
| Pattern | Basic Q&A chatbot | Tool-using agent | Agentic workflow |
|---|---|---|---|
| Memory/context | Configured conversation context | Context and tool results | State shared across steps |
| Tool use | Optional | Permitted application functions | Coordinated tools or agents |
| Autonomy | Bounded answers | Chooses actions within limits | Defined by the workflow |
| Example | Office-hours questions | Submit a validated booking | Prepare authorization evidence for review |
Agentic AI healthcare deployments need defined stopping conditions. With function calling, the model proposes a call and your application validates and runs it. This technology needs permission checks around the action, including whether the user can make that particular change.
Types of healthcare AI agents
A useful grouping for healthcare app development is:
- Patient-facing: appointment requests and intake.
- Clinician-facing: draft documentation and record retrieval.
- Administrative: eligibility or revenue-cycle work.
- Voice: a phone channel spanning the other roles.
For a mental health app development project, check whether the therapy-specific restrictions below apply.
How a healthcare AI agent works
A reference workflow is: trigger → interpret the request → check permissions → read through approved tools → propose a change → obtain required review → write and audit.
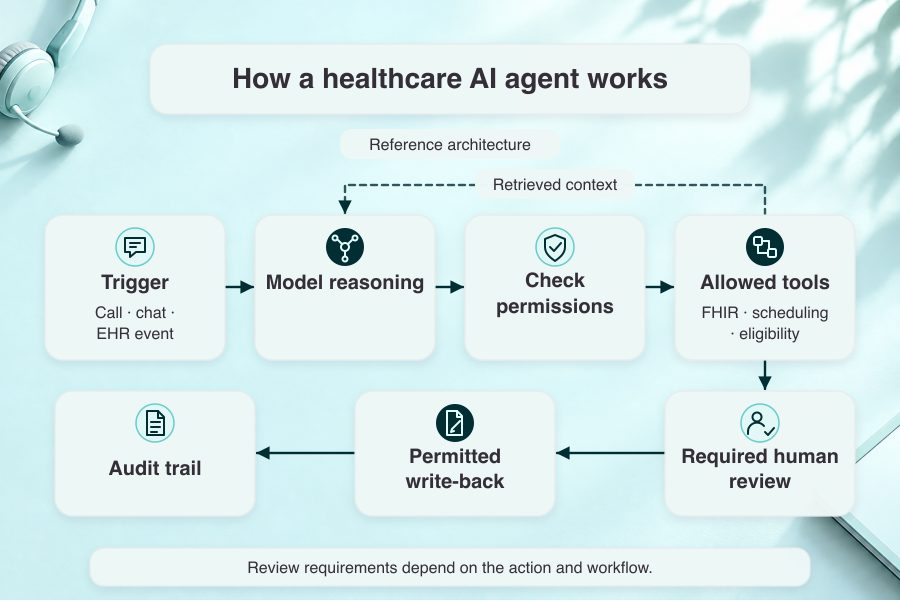
Retrieval-augmented generation (RAG) supplies reference material when generating an answer. Preserve the reference alongside the output so a reviewer can check what supports it.
Optional memory supplies context; it doesn't mean a model retrains itself from each interaction. Autonomous agents need action limits; multi-agent systems divide work, with orchestration coordinating the steps.
Why healthcare organizations are deploying AI agents in 2026
The practical business case is a task you can automate and evaluate against the work staff already do. Adoption is already broad: in the 2025 CAQH Index, nearly 60 percent of medical plans and 25 percent of providers reported using AI.
Burnout and administrative burden
Documentation is one testable source of administrative burden. A 2025 JAMA Network Open study across 6 health systems associated ambient-scribe use with lower self-reported burnout after 30 days. The voluntary pre/post study used self-reported outcomes and had no control group.
Physician burnout is trending down but remains widespread. In the AMA's 2025 national survey, 41.9 percent of physicians reported at least one symptom of burnout, down from 43.2 percent in 2024 and 48.2 percent in 2023.
Patients expect timely answers
Identify after-hours requests that can finish safely, such as collecting appointment preferences. Give clinical concerns a defined escalation path and tell the patient what happens next.
Operational costs need a task-level baseline
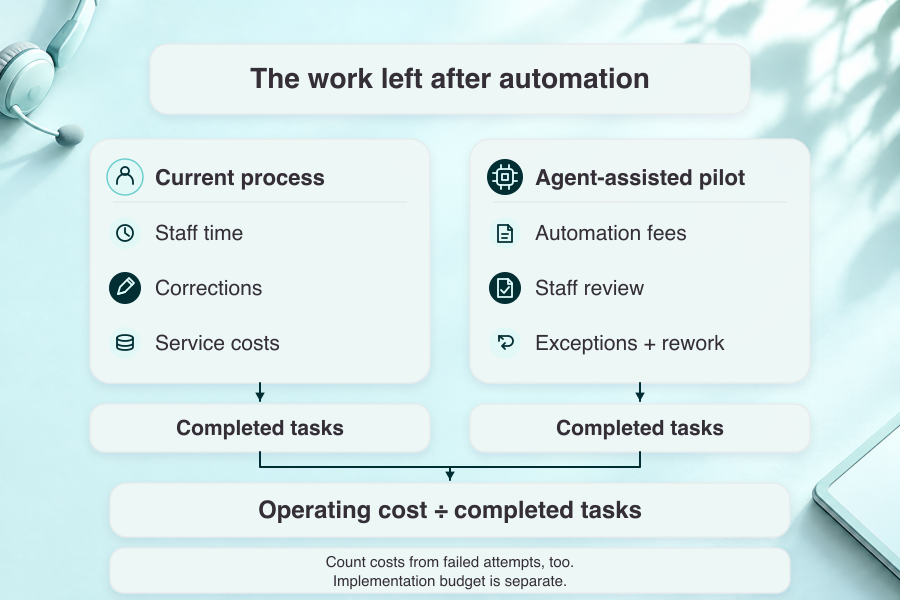
Count staff handling time, corrections and service charges for each completed task. Include the work generated by exceptions. A pilot earns expansion when its results justify the operating cost. Manual administrative work is expensive at the industry level too: the 2025 CAQH Index identifies a $21 billion automation gap in administrative transactions.
Healthcare AI agent use cases and ROI metrics
Healthcare AI agents can be scoped around these workflows. Choose the healthcare AI agent whose permitted actions fit the job, then measure it against your baseline.
The risk labels below are our implementation judgments for the proposed scope. Metrics are pilot measures, with targets set by your team.
| Use case | User | Integration needed | Implementation risk | Metric to track |
|---|---|---|---|---|
| Scheduling & reminders | Patient and front desk | Booking system | Controlled for bounded booking; check identity | Booking completion and no-show rate |
| Refill requests | Patient and prescriber | Medication/request workflow | Clinical decision needs prescriber review | Routing completion and escalations |
| Patient Q&A | Patient and staff | Approved content and handoff queue | Rises with clinical advice | Corrections and clinical escalations |
| Documentation | Clinician | Encounter data and note workflow | Draft content needs review | Review time and documentation errors |
| Intake/eligibility | Patient and billing staff | Forms plus authorized eligibility service | Patient matching and eligibility exceptions | Complete intake and unresolved responses |
| Prior authorization | Clinical/billing staff | Clinical evidence and payer interface | Submission errors and payer-specific rules | Rework and response turnaround |
Appointment scheduling and reminders
Keep permitted visit types and approval rules in application code. Validate patient matching before changing a booking.
Start your health app development scope with the booking operations you can test. Compare HIPAA-compliant scheduling software if an existing product already covers them.
Appointment reminders are a well studied lever. In a 2024 randomized trial, a patient portal reminder sent within one business day of a missed appointment raised 30-day reattendance to 22.2 percent, against 11.6 percent for a mailed letter alone.
Inspect automated changes for:
- Duplicate bookings.
- Incorrectly changed or cancelled appointments.
Medication refills and adherence tracking
Use medication refills as a request-and-routing workflow. Collect the patient's request and send approved reminders; direct renewal decisions to the authorized prescriber.
Track:
- Requests routed correctly.
- Requests that need staff intervention.
Evaluate the actual intervention before making an adherence claim.
Patient Q&A agents
Separate administrative content from patient-specific clinical questions. Generative AI can help retrieve approved instructions; a medication-safety question needs a clinical escalation route.
For covered California clinical communications, AB 3030 requires AI notice and human-contact instructions. Scheduling/billing communications are excluded; messages read and reviewed by a licensed or certified human healthcare provider have an exception.
Ambient documentation and chart summary agents
Treat ambient clinical documentation as a draft for the clinician to verify. Include source context where staff need to check a summary against the record.
An AI scribe pilot should measure review time and correction burden. Our AI medical scribe guide covers that build path; the study above doesn't establish a financial return for every documentation workflow.
Patient intake and insurance eligibility agents
Patient intake collects information; insurance eligibility verification needs a separate authorized connection. CMS's eligibility service illustrates the distinction: authorized transactions return eligibility information.
Route conflicting or unresolved responses to staff. If you're deciding how to improve patient intake efficiency, measure incomplete fields and the follow-up work they generate.
Prior authorization and revenue cycle agents
Scope AI agents for healthcare revenue cycle management around evidence collection, request preparation and status tracking. Revenue cycle management (RCM) still needs payer-specific rules and a person responsible for exceptions. Prior authorization is where plan and provider AI is concentrated today: in the 2025 CAQH Index, 44 percent of medical plans and 53 percent of medical providers reported using AI for prior authorization workflows.
An AI prior authorization assistant can prepare documentation for submission. Verify the payer's actual interface and permitted actions, including whether the workflow concerns drugs. The CMS rule has distinct scope and API deadlines.
AI voice agents for healthcare
What are AI voice agents for healthcare? They're phone-based workflows that interpret spoken requests and use permitted tools to answer or act, with a route to staff.
An AI voice agent for healthcare needs booking rules and a handoff that preserves the caller's context. Before deploying an AI voice agent in healthcare, decide which requests can finish during the call and which need review.
Voice workflows need a controlled tool connection
Voice AI agents for healthcare can collect scheduling preferences, route refill requests or assist with payer calls. A reference scheduling pattern combines telephony, a real-time speech model and server-side tools: verify identity, check availability, propose a booking, then run the permitted change.
Use synthetic data while testing that architecture. The application validates tool calls before acting.
Twilio lists Programmable Voice and Media Streams as HIPAA-eligible, subject to its BAA and architecture conditions. Its HIPAA Account setup also requires Security or Enterprise Edition. Each model service needs its own eligible configuration and agreement.
Measure resolution and safe handoffs
In AI agent first-call resolution healthcare, count issues resolved during the first call, including successful staff handoffs. Containment measures calls handled without a live agent.
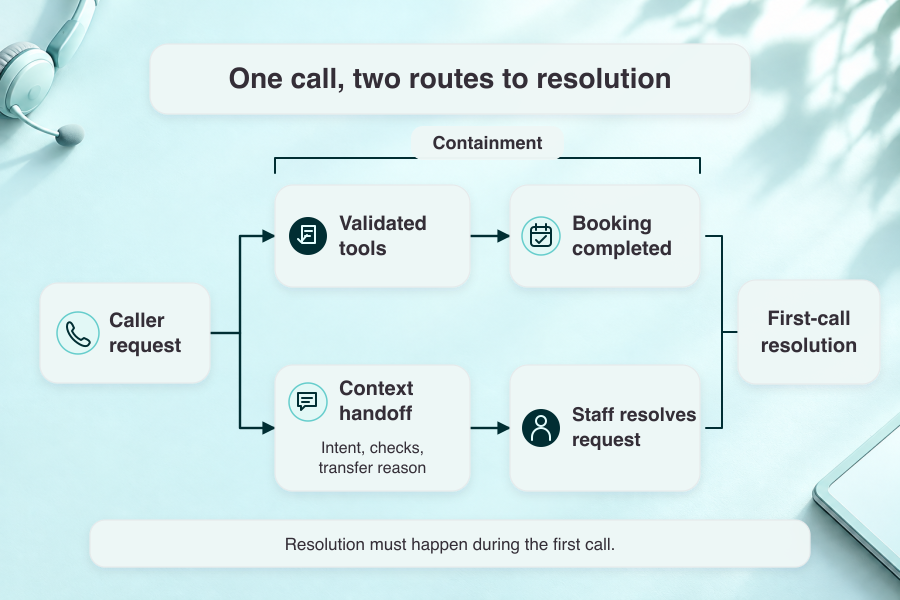
Track transfer rate and the caller's wait between turns. Review errors alongside call deflection, so a completed automated call still has to meet your acceptance criteria. Set targets from the pilot's baseline.
How to integrate AI agents with your EHR
AI-powered healthcare agents need explicit access to the operations their workflow uses. Inventory appointment booking and other workflow management actions before connecting production medical records.
FHIR, HL7 v2 and read vs. write-back
Treat EHR integration as a set of operations with separate access requirements:
- Confirm supported interfaces, including FHIR R4 resource interactions and existing HL7 v2 messaging.
- Inspect the granted SMART on FHIR scopes for each action.
- Test event handling and update behavior against the connected system.
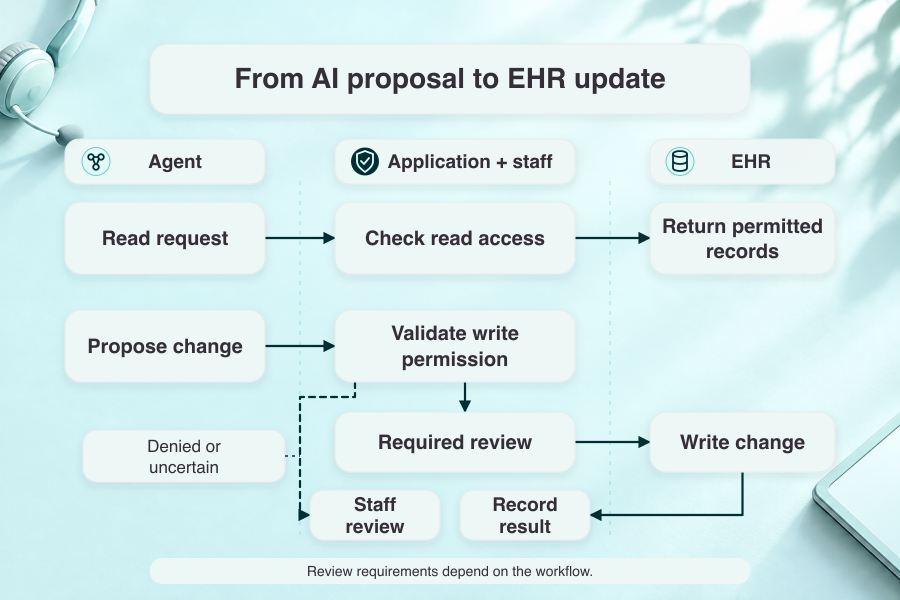
FHIR APIs describe interactions; the vendor's supported resources and your authorization determine the available actions. Read/search access needs a separate check from create/update access.
| Platform | Check before enabling writes |
|---|---|
| Epic | Create/update support is available for selected APIs; confirm the specific operation. |
| Oracle Health | Patient, user and system contexts have explicit resource scopes. |
| athenahealth | athenaOne's patient-facing certified FHIR access is read-only; check the appropriate API arrangement for writes. |
| Canvas | FHIR creates/updates commit data directly. Provider-reviewed staged data uses its Plugin SDK workflow. |
Our Canvas Medical build guide covers that implementation context. Decide where a change waits for approval before calling the write operation. A visible draft in your interface must correspond to the storage behavior you actually configured.
Keep a workflow inventory pairing each proposed action with its required operation and granted permission. Make the application reject calls outside that inventory, and give staff a way to inspect a failed request. Test the permission boundary using the roles that will actually use the agent.
Why AI projects stall after the POC
Test the entire transaction before expanding beyond the demo, including missing records and rejected permissions. Repeated tool calls also need tests so a retry follows the booking rules.
Assign ownership for failed updates and clinical escalations. Record which action the agent proposed, who approved it and what the connected system returned. Then compare completion and rework against the existing process before expanding the scope.
HIPAA, safety and regulation for healthcare AI agents
HIPAA compliant AI agents for healthcare require safeguards across the deployed workflow. Evaluate a HIPAA compliant AI agent for healthcare against its actual data access and permitted actions, with the required agreements in place.
HIPAA and BAAs with LLM providers
Check each service that handles protected health information (PHI) and the business associate agreement (BAA) covering that use. HHS cloud guidance makes the provider's role and data handling relevant even when the provider can't decrypt the data.
OpenAI documents PHI processing under an executed Business Associate and Healthcare Addendum, with eligible endpoints and provisioned organizations. Check the actual service, feature and retention configuration. Confirm coverage for the particular audio endpoint before sending patient data.
Keep unnecessary patient content out of general debugging logs. Protect audit logs with restricted access and record the actions needed for accountability. Apply HIPAA's minimum-necessary rule where it applies, including its treatment-related exceptions.
Human-in-the-loop and guardrails
Put guardrails and escalation around consequential actions. A human-in-the-loop review needs an approval point before the change is made, with access to the evidence being reviewed.
Use action limits for appointment changes and route uncertain medical questions to clinical staff. Review patient matching and authorization failures in the pilot.
The HIPAA Security Rule imposes the applicable legal safeguards. SOC 2 attestations and HITRUST certifications are separate, voluntary assurance programs that buyers may require by contract.
FDA clinical decision support requirements
The FDA clinical decision support (CDS) guidance, issued January 29, 2026, describes the Non-Device CDS criteria. A function must meet all 4, including restrictions on medical-image/signal inputs, use of medical information, recommendations to healthcare professionals and their ability to independently review the basis.
Assess the intended user and whether the function proposes diagnoses or treatment. Patient-facing diagnostic recommendations need a separate device assessment. An approval button alone doesn't establish that a clinician can independently review the recommendation's basis.
State AI requirements
As of October 2026, these selected requirements apply to different workflows:
| Law | What it requires | Applies to |
|---|---|---|
| California AB 3030 | AI notice and human-contact instructions for covered unreviewed clinical communications. Administrative scheduling/billing excluded; messages read and reviewed by a licensed or certified human healthcare provider excepted. | Specified facilities, clinics and physician practices. |
| California AB 489 | Protects professional identity: AI functionality/advertising must avoid implying care comes from a properly licensed natural person. | Health advice/care representations covered by the statute. |
| Texas TRAIGA | Written, plain-language AI notice by first service/treatment date; emergencies permit disclosure as soon as reasonably possible. | Providers using AI in relation to healthcare service/treatment. |
| Illinois therapy law | Restricts independent decisions/direct AI therapeutic communication; specified recorded/transcribed-session support needs written notice of AI use and purpose, plus consent. | Therapy/psychotherapy professionals; responsibility remains with the professional. |
| Maine chatbot transparency | Clear AI notice where a chatbot could mislead a reasonable consumer about interacting with a human. | Chatbots used in trade or commerce. |
| Maine therapy law | Restricts independent/direct therapeutic functions; permitted supplementary recorded/transcribed-session support needs written notice covering AI use, purpose and session-data handling, plus consent. | Specified licensed professionals; administrative support has a distinct scope. |
Maine includes a limited exception for qualifying IRB-approved research. Illinois and Maine consent requirements don't authorize otherwise prohibited therapeutic functions. For no-code HIPAA compliance, keep these workflow-specific rules in your implementation review alongside code checks from the HIPAA Compliance Agent.
AI agents in healthcare: examples and adaptation patterns
AI agents in healthcare examples identify the input, allowed action and human checkpoint. These are illustrative designs, with the voice-scheduling pattern covered above.
Conversational retrieval needs authorized sources
A clinician requests a chart summary. The proposed workflow checks access, retrieves permitted records and gives the clinician source references to review.
Keep retrieval within the user's permissions. If the data is missing or conflicting, route the request for review. A conversational interface provides a way to request information; the connected system still determines what that user can access.
Intake discovery needs an exception queue
An intake assistant collects structured information and checks required fields. A separately authorized eligibility service returns the insurance response, with staff reviewing mismatches.
Keep the original patient input available for review. Measure incomplete submissions and unresolved exceptions before expanding the flow to more patients or visit types.

Build vs. buy: choosing a healthcare AI agent
The best AI agents for healthcare fit a defined job and your access requirements. AI agent healthcare succeeds when staff can supervise it; confirm ownership and support terms your team can accept.
Use the medical app builder comparison to assess platform choices. For the agent itself, ask each supplier the same procurement questions:
| Purchasing path | Point solution | EHR-native capability | Builder/platform | Fully custom |
|---|---|---|---|---|
| Rough cost range | A September 2026 comparison of 13 ambient AI scribes found published per-clinician prices from $0 (Doximity, Heidi) to $149 per month (Sunoh.ai); enterprise-first vendors publish no price and sell through quotes. Confirm the BAA and integration fees. | Included with the EHR or billed as an add-on; the terms sit in your EHR contract. | $1,000/month (Specode Pro) to $5,000+/month (Custom, with managed coding and custom agent work); budget EHR access and service usage separately. | From $5,000/month subscription plus scoped engineering, integration and operating costs. |
| Rough time to launch | Days to weeks for configuration, required agreements and connections. | Weeks, depending on enablement, approvals and the EHR release cycle. | Prototype in about 10 minutes; production-ready basic workflow in 1 to 2 weeks (Specode data); EHR access and validation add time. | Weeks to months, set by scope, security review and EHR credentials. |
| Code ownership | Vendor keeps the code; you own your configuration and data rights. | Vendor keeps the code; marketplace add-on terms apply. | You own the application code and can export it (Specode); confirm export terms with other builders. | You own the code; secure assignment and escrow in the contract. |
| Fit to check | Does its existing workflow cover your task? | Does it support the operation in your EHR environment? | Can your team configure and maintain the workflow? | What work remains after the first build, and who owns it? |
How much does it cost to build a healthcare AI agent?
Specode's documented subscriptions are Pro at $1,000/month and Custom from $5,000/month. Custom includes managed coding and custom AI-agent work. Those prices cover ongoing subscriptions.
Request an implementation estimate against the chosen workflow. Budget separately for:
- EHR access and integration work.
- Model, telephony and other service usage.
- Security and clinical-output review.
- Ongoing support and exception handling.
Compare cost per successfully completed task with the existing process, including human review and rework. The amount of application code generated tells you little about those operating costs.
Ask the supplier to walk through a failed task as well as a completed one. Identify which exceptions your staff will handle and which the supplier will support. Put that division of responsibility in the scope, with acceptance criteria you can check during the pilot.
For code ownership, inspect the export and licensing terms before signing. Your maintenance plan needs an owner for changes to the workflow and its service connections after launch. Include that work in the recurring budget.
How to build a healthcare AI agent: 6 steps
Use this checklist to implement the first pilot:
- Choose one workflow and define a completed task.
- Map the data the workflow touches, including where PHI may be handled.
- Select eligible model/services and establish the required agreements.
- Connect only permitted EHR and operational tools.
- Add action limits, human review and exception handling.
- Pilot against a baseline that includes errors, staff rework and ongoing cost.
Approve expansion against the measured results. Keep clinical decisions with the responsible professional and revisit the controls whenever permitted actions change.
Building healthcare AI agents with Specode
Specode can help you build an AI agent in healthcare on a HIPAA-ready foundation, with a guided planning, design and implementation workflow. You approve the roadmap and design before code is built, then refine the application through conversation.
Its healthcare skills support patterns such as intake and scheduling. EHR connections still need the project's credentials and permitted API operations. For custom healthcare software development, include those external dependencies in the scope.
The HIPAA Compliance Agent reviews application code for potential issues. Fix its must-fix findings and rescan; validate clinical output separately with a curated dataset and a qualified reviewer. You own the application code and can export it.
Specode's pre-launch security/HIPAA review is a defined checkpoint. Scope ongoing hands-on engineering under Custom, with responsibilities for testing and maintaining the agent agreed before deployment.
Use synthetic data throughout the builder and previews. Production needs your own Convex account, the required BAAs and security review. Pro customers can use the guided publish flow to connect their repository and production deployment.
For telemedicine app development or another patient workflow, specify what the agent can change before estimating the build. Talk with the Specode team once you've defined the task and its review requirements.
Frequently asked questions
They use models and permitted tools to complete assigned tasks. Their behavior depends on the workflow, data access and action limits configured around them, including escalation to staff.
Use them for defined support work, with clinical decisions assigned to responsible professionals. Human review and escalation remain design requirements for consequential outputs.
They can organize evidence for clinical review. A function stays outside FDA device regulation only when it meets all 4 Non-Device CDS criteria in the FDA guidance (January 2026): no medical-image or signal analysis, display or analysis of medical information, recommendations to healthcare professionals, and a clinician's ability to independently review each recommendation's basis. In Texas, TRAIGA requires the provider to give written, plain-language AI notice no later than the first service or treatment, with later disclosure when an emergency prevents it.
A practical grouping is patient-facing, clinician-facing, administrative and voice workflows. Voice overlaps the other roles; choose categories that help define the job.
Choose by workflow, permitted system actions, review controls and contractual terms. A scheduling tool and a documentation assistant solve different jobs, with different integration requirements.
Evaluate conversational tools by intended use, clinical evidence and data agreements. A familiar chat interface alone doesn't establish suitability for patient-specific care or PHI processing.
It describes systems coordinating model decisions and tools. Some use predefined workflows; others choose next steps within configured limits and stopping conditions that your team defines.
Compliance depends on the deployed workflow, safeguards and agreements covering the services handling PHI. Assess the full application and its operations before using patient data.
Specode Pro is $1,000/month; Custom starts at $5,000/month. Implementation scope and third-party usage add costs that need separate estimates. If you're also curious whether AI agents help reduce healthcare costs for patients and providers, measure completed-task costs against the existing workflow, including review and rework. A pilot's savings depend on actual performance and operating costs, and patient-price reductions require separate evidence.



